SHARE Knowledge Hub
Human Failures, Human Factors and Human Reliability
Human failure analysis distinguishes unintentional slips, lapses and mistakes from deliberate rule deviations, then examines the job, person and organisation around the event. For the conveyor isolation and jam-clearing example, make identification and physical safeguards robust before relying on memory or retraining. Human reliability estimates need task-specific assumptions and data; a number alone cannot prove a barrier will work.
Understanding Human Failures, Human Factors and Human Reliability
Human factors is the interaction of the task, equipment, environment, person and organisation that shapes health and safety performance.
Why this matters at work
Human reliability analysis (HRA) may be qualitative or quantitative. Qualitative analysis identifies tasks, error modes, PIFs and barriers. A quantitative estimate can support a high-consequence risk study, but its value depends on task definition, quality of evidence, assumptions and applicability of the selected method and data. HSE calls for a proportionate approach; a generic probability copied from another task or industry is not a site-specific fact. State whether the number represents an action failure, a whole task, or a failure to recover, and under which conditions.
When an unsafe deviation creates a near miss, analyse the hazardous mechanism and barrier failures. In a garage, bypassing a lift lock can cause crush injury; in manufacturing, defeating an interlock can lead to amputation; in a chemical plant, bypassing a trip can allow runaway or release. Preventive barriers include design and accessible safe methods; recovery includes detection of bypass status, supervisor challenge, stop-work authority and emergency response. Observation cards alone will not correct an impossible production schedule.
How organisations manage this in practice
Break the task into meaningful steps and ask what could be omitted, done late, done to the wrong object, done in the wrong direction or performed on the basis of a mistaken diagnosis. Record the cause-relevant PIFs, immediate outcome and hazard mechanism. The HSE inspectors’ toolkit provides a proforma covering step, likely failure, recovery potential, consequence, preventive measures and measures to reduce consequences. Use it as a guide, not a requirement to catalogue every minor motion. Focus effort where the failure can defeat a critical control.
A violation is a deliberate departure from a rule, but it does not automatically imply malicious intent. HSE distinguishes routine, situational and exceptional patterns. A shortcut may have become normal because supervision accepts it, a worker may improvise because tools or time are missing, or an unusual situation may prompt a well-intentioned but unsafe departure. A rule that conflicts with the physical task or with competing management instructions cannot be made reliable through punishment alone. Intent, context and actual feasibility must be established fairly.
Compare work as imagined with work as done. Observe whether the required tool, access, isolation, PPE and time are available. Ask workers what makes the procedure difficult, what they do instead and how supervisors respond. Separate a genuine workable rule deliberately ignored from a document that has not kept pace with plant change. Incentives matter: a zero-delay target may quietly reward bypassing a check. Reform the work system, make rules concise and relevant, and maintain proportionate accountability for serious intentional misconduct.
What are the key facts about human failures and reliability?
The key fact is that error is usually predictable when the task, equipment or organisation makes failure likely.
Best-practice guide: Human Failures, Human Factors and Human Reliability

What are the key facts about human failures and reliability?
The key fact is that error is usually predictable when the task, equipment or organisation makes failure likely. Human failure analysis distinguishes unintentional slips, lapses and mistakes from deliberate rule deviations, then examines the job, person and organisation around the event.
Turn human failures, human factors and human reliability knowledge into a decision
Human failure analysis distinguishes unintentional slips, lapses and mistakes from deliberate rule deviations, then examines the job, person and organisation around the event. For the conveyor isolation and jam-clearing example, make identification and physical safeguards robust before relying on memory or retraining. Was the worker competent, fatigued, interrupted or under pressure?
Human failure investigation example
Person: Was the worker competent, fatigued, interrupted or under pressure? Task: Was the procedure usable and was isolation practical for blockage clearing?
Human reliability warning signs
Same error repeats: The task contains an uncorrected error trap. Rules regularly bypassed: Controls may be impractical or poorly supervised. Procedures do not match work: People improvise and critical steps are missed.
Choose controls for human failures, human factors and human reliability
Eliminate: Remove the wrong-valve choice by plant or route redesign. Reduce: Use physically distinct valve design as an engineering error-reduction measure where suitable. Simplify the lineup sequence as an administrative task-design control; neither measure is hazard substitution. Isolate: Physically segregate or lock out the incompatible valve. Control: Use clear labels, position feedback and independent process protection where justified. Control: Use concise task steps, independent checks and manageable workload. Read the full control table for qualifications, ownership and verification. Use the actual task and applicable jurisdiction; existing technical approval remains unchanged.
Use the full human failures, human factors and human reliability lesson
Use the full topic for the decision points, practical examples, detailed control tables and source scope. HSE guidance applies to Great Britain; use HSENI for the Northern Ireland route and the source’s stated jurisdiction. A simplified guide does not change the page’s technical-review or approval status.

Read all six steps as text
1. What are the key facts about human failures and reliability?
The key fact is that error is usually predictable when the task, equipment or organisation makes failure likely.
- Avoid / redesign: Remove the wrong-valve choice by plant or route redesign.
- Control the task: Physically segregate or lock out the incompatible valve.
- Verify before release: Error path remains: add controls.
The key fact is that error is usually predictable when the task, equipment or organisation makes failure likely. Human failure analysis distinguishes unintentional slips, lapses and mistakes from deliberate rule deviations, then examines the job, person and organisation around the event.
Apply it: Which part of this plan would you check at the workface before authorising the task?
2. Turn human failures, human factors and human reliability knowledge into a decision
Use the evidence to improve the actual work arrangement.
- Change at source: Remove the wrong-valve choice by plant or route redesign.
- Make it observable: Error path remains: add controls.
- Keep useful evidence: Was the worker competent, fatigued, interrupted or under pressure?
Human failure analysis distinguishes unintentional slips, lapses and mistakes from deliberate rule deviations, then examines the job, person and organisation around the event. For the conveyor isolation and jam-clearing example, make identification and physical safeguards robust before relying on memory or retraining. Was the worker competent, fatigued, interrupted or under pressure?
Apply it: What evidence would show that the change improves this task, rather than only completing a record?
3. Human failure investigation example
Example: a practical application of the existing topic lesson.
- Person: Was the worker competent, fatigued, interrupted or under pressure?
- Task: Was the procedure usable and was isolation practical for blockage clearing?
- Equipment: Could the blockage be cleared without removing the guard?
Person: Was the worker competent, fatigued, interrupted or under pressure? Task: Was the procedure usable and was isolation practical for blockage clearing?
Apply it: At which point would you hold this example, and what evidence would allow it to proceed?
4. Human reliability warning signs
Connect the task, the route to the person and the control that can fail.
- Same error repeats: The task contains an uncorrected error trap.
- Rules regularly bypassed: Controls may be impractical or poorly supervised.
- Procedures do not match work: People improvise and critical steps are missed.
Same error repeats: The task contains an uncorrected error trap. Rules regularly bypassed: Controls may be impractical or poorly supervised. Procedures do not match work: People improvise and critical steps are missed.
Apply it: Who could be exposed, including other trades, cleaners, maintainers and people nearby?
5. Choose controls for human failures, human factors and human reliability
Start with the stronger practicable options and verify their effect.
- Eliminate: Remove the wrong-valve choice by plant or route redesign.
- Reduce: Use physically distinct valve design as an engineering error-reduction measure where suitable. Simplify the lineup sequence as an administrative task-design control; neither measure is hazard substitution.
- Isolate: Physically segregate or lock out the incompatible valve.
- Control: Use clear labels, position feedback and independent process protection where justified.
- Control: Use concise task steps, independent checks and manageable workload.
Eliminate: Remove the wrong-valve choice by plant or route redesign. Reduce: Use physically distinct valve design as an engineering error-reduction measure where suitable. Simplify the lineup sequence as an administrative task-design control; neither measure is hazard substitution. Isolate: Physically segregate or lock out the incompatible valve. Control: Use clear labels, position feedback and independent process protection where justified. Control: Use concise task steps, independent checks and manageable workload. Read the full control table for qualifications, ownership and verification. Use the actual task and applicable jurisdiction; existing technical approval remains unchanged.
Apply it: Which stronger option can be used here, and who will verify it before accepting the remaining risk?
6. Use the full human failures, human factors and human reliability lesson
Follow the official sources below and retain the task-specific evidence.
- Official guidance: HSE HSG48 full guide
- Official guidance: HSE managing human failures
- Task decision: Was the worker competent, fatigued, interrupted or under pressure?
Use the full topic for the decision points, practical examples, detailed control tables and source scope. HSE guidance applies to Great Britain; use HSENI for the Northern Ireland route and the source’s stated jurisdiction. A simplified guide does not change the page’s technical-review or approval status.
Apply it: Which official source and full-topic section will you use to resolve the next decision?
Human error is not a root cause
It is usually a starting point for deeper analysis of work design, competence, supervision, culture and controls.
Different failures need different controls
A slip, lapse, mistake and violation are not fixed by the same action.
Reliability depends on context
A person may perform reliably in normal conditions but fail during fatigue, overload, unclear displays or abnormal work.
Task analysis makes error visible
Breaking work into steps helps identify where error is credible and which controls are needed.
Good design beats repeated reminders
Engineering, layout, prompts, interlocks and simpler tasks are usually stronger than telling people to take care.
What do human failures, human factors and human reliability mean?
Human failure and fair investigation
Human failure is failure of required safe performance. An unintentional error and a deliberate departure from a rule differ: a shortcut may achieve the person’s immediate production aim while breaching the safe system. HSG48’s routine, situational and exceptional violation categories do not determine blame or a disciplinary outcome. Establish context, intent, system conditions and evidence separately.
The topic explains how people interact with work systems and how organisations can reduce predictable failure.
Human failures are not all the same. Some are unintended errors, such as selecting the wrong control, forgetting a step or misunderstanding a situation. Others are violations, where a person deliberately departs from a rule. Even violations need careful analysis because the rule may be impractical, conflicting, poorly supervised or routinely undermined by work pressure. HSE introduction to human factors
Human factors is the wider discipline that studies the job, the person and the organisation. Human reliability is the practical question: if this person is a barrier in the risk assessment, can we rely on that action under the real conditions?
| Concept | Plain-English meaning | Workplace example |
|---|---|---|
| Human failure | An action or decision that fails to achieve what was intended. | Forgetting to replace a guard after maintenance. HSE introduction to human factors |
| Human factors | Work design factors that influence behaviour and safety. | Poor display design makes a wrong reading more likely. HSE introduction to human factors |
| Human reliability | Likelihood of correct performance when needed. | Operator responds to alarm in time. HSE introduction to human factors |
| Work as imagined | How procedures or managers think the work is done. | Checklist says two-person check is always used. HSE introduction to human factors |
| Work as done | How the work is actually performed in real conditions. | Second checker is unavailable during peak workload. HSE introduction to human factors |
What are slips, lapses, mistakes and violations?
Classifying the failure helps choose a useful control rather than defaulting to retraining.


A slip concerns execution, a lapse memory, a mistake the chosen plan, and a violation a deliberate departure. The response should address the relevant system conditions.
Why is a single 'retrain everyone' action often insufficient?
Different failure types can need different changes, such as control redesign, interruption recovery or workable procedures and supervision.
Classification needs evidence of intention and task context; the four scenes are example.
Source guidance: HSE HSG48
A slip is an action error, such as turning the wrong switch when the intention was correct. A lapse is a memory failure, such as forgetting a step. A mistake is a wrong plan or judgement, such as using the wrong method because the situation was misunderstood. A violation is a deliberate departure from a rule. HSE HSG48 full guide
Each needs a different response. Slips may need better layout, labels or interlocks. Lapses may need checklists and prompts. Mistakes may need better competence, information and decision aids. Violations may need rule review, supervision, resources, culture change or accountability, depending on why the violation occurred.
| Failure type | What it means | Better control |
|---|---|---|
| Slip | Right intention, wrong action. | Distinct controls, guarding, labels, physical separation and confirmation prompts. HSE HSG48 full guide |
| Lapse | Memory or attention failure. | Checklists, reminders, independent checks and reduced interruption. HSE HSG48 full guide |
| Rule-based mistake | Wrong rule applied or rule misunderstood. | Better procedures, examples, supervision and competence checks. HSE HSG48 full guide |
| Knowledge-based mistake | Person has to solve a novel problem and chooses wrongly. | Training, decision aids, escalation and expert support. HSE HSG48 full guide |
| Violation | Deliberate departure from a rule. | Understand motive, remove pressure, fix poor rules and apply fair accountability. HSE HSG48 full guide |
How does human performance affect this work?
Explore the distinction between an unintended error and a deliberate deviation, then check the conditions surrounding both. Use the examples to develop questions; the overview does not establish why a real event happened.
Select any box to open its explanation below. You can also use the grouped text headings. Several explanations can stay open for comparison.
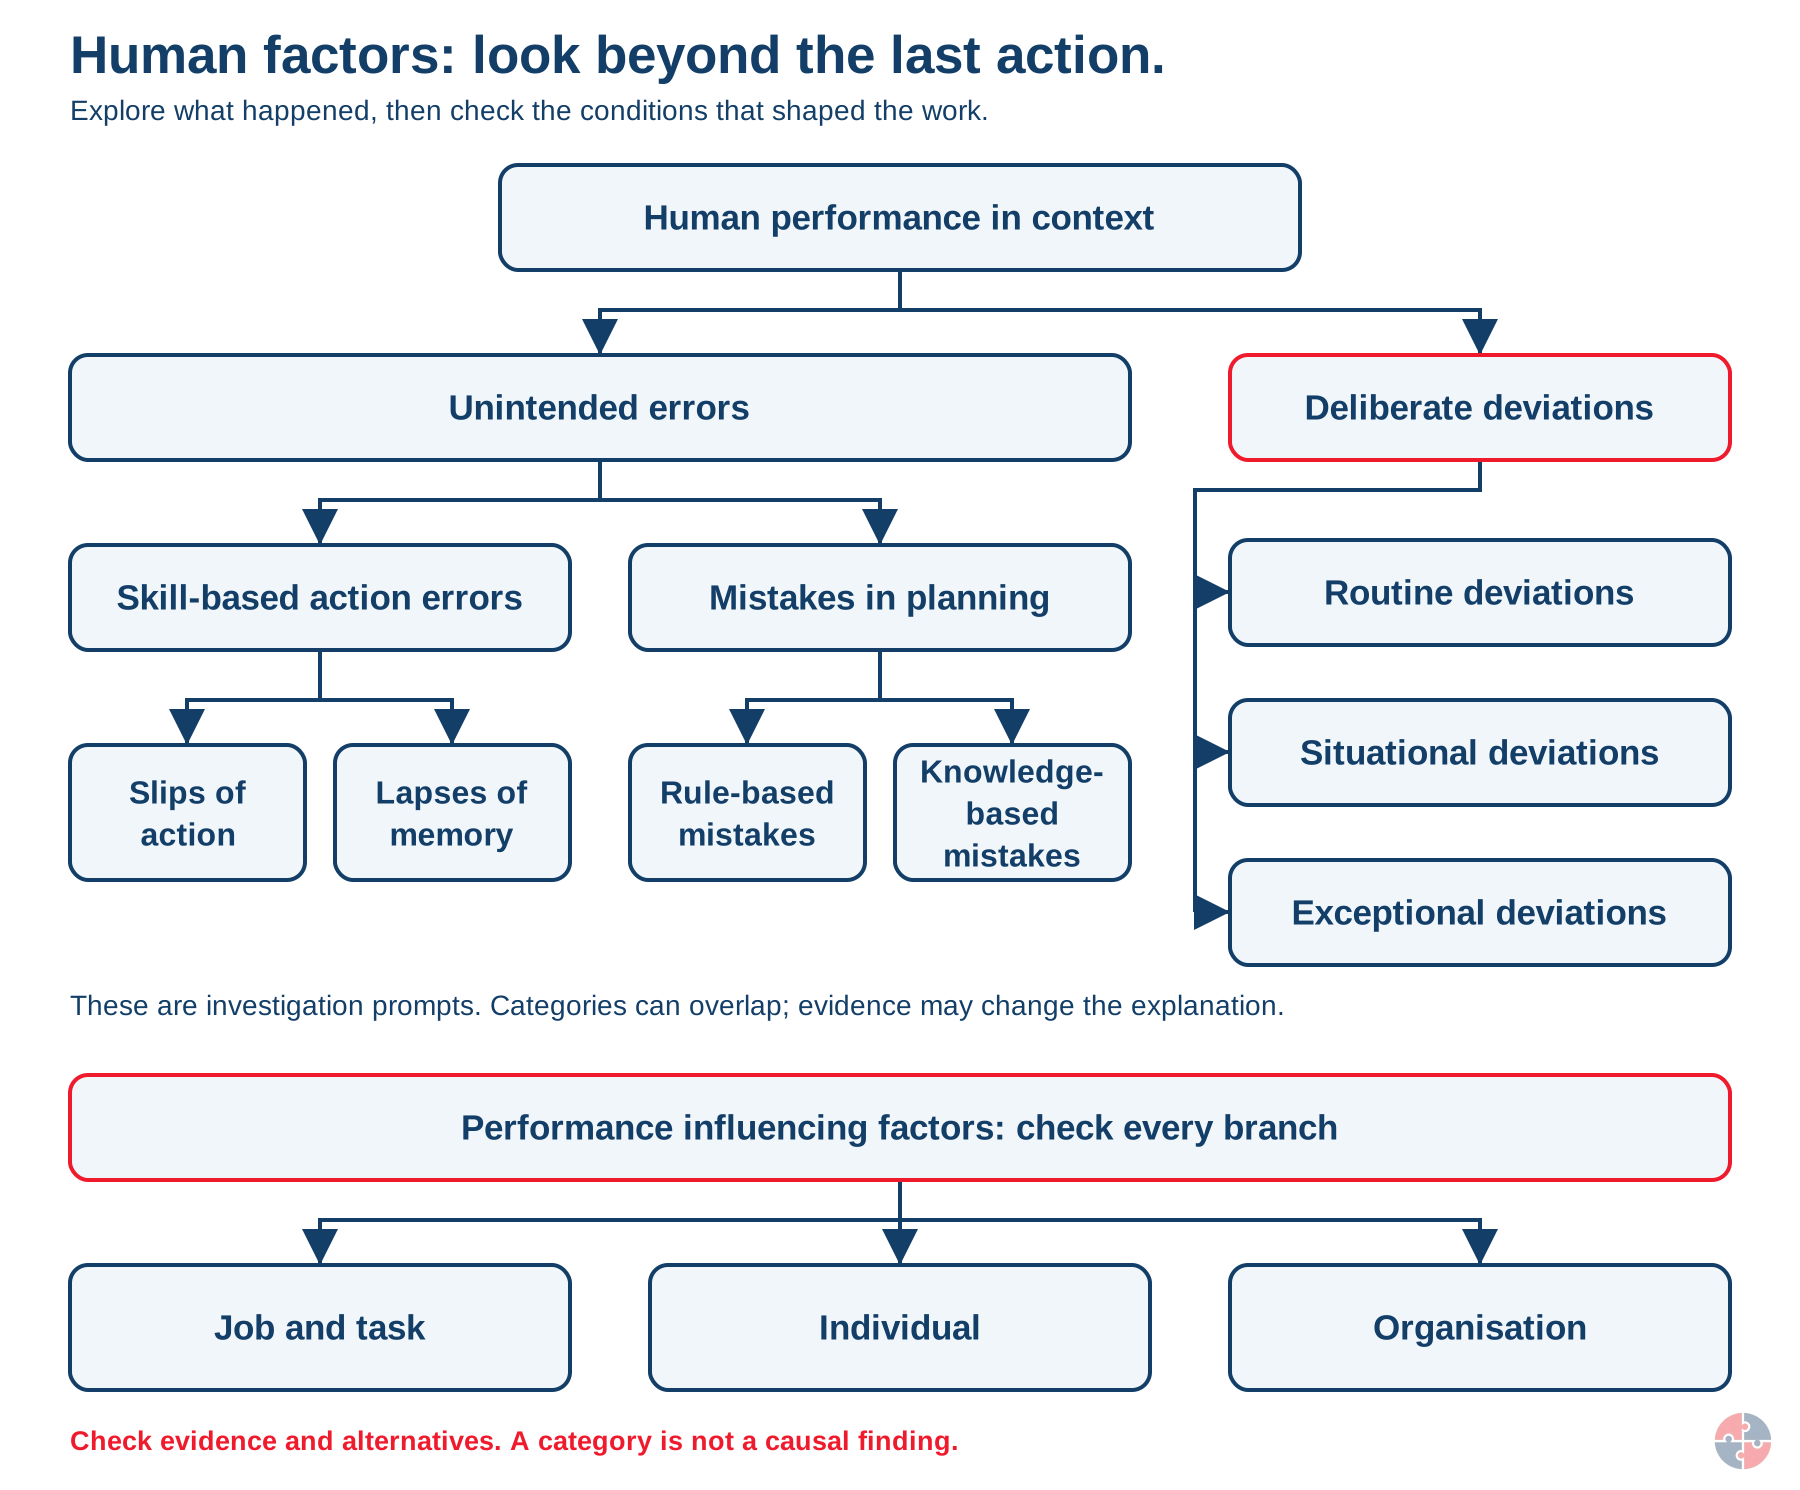
Original SHARElearn teaching overview. Arrows show groupings, not a causal sequence. Examples are fictional; no box establishes an actual cause, diagnosis or responsibility.
Inspect the full-size overview (new tab)
Start with the work context
Human performance in context
Human factors considers how the job, the individual and the organisation interact. A human action is a starting point for inquiry, not a complete explanation.
Fictional example: A pump control is operated incorrectly. The team examines what the operator could see, the control layout and the work arrangements.
Investigate and improve: Reconstruct the information and options available at the time. Ask what made the action understandable and what would prevent or tolerate it.
Unintended errors
An action or decision goes wrong without an intended departure from the expected method. Distinguish doing the wrong action from choosing an unsuitable plan.
Fictional example: A person intends to stop pump A but presses the adjacent control for pump B.
Investigate and improve: An outcome alone does not establish intent. Compare the person’s account, task sequence, equipment and available records; retain uncertainty.
Unintended errors: actions and decisions
Skill-based action errors
A familiar task is intended correctly but its execution goes wrong through a slip or lapse. Experienced people can be affected.
Fictional example: A routine restart is interrupted and the person resumes at the wrong point.
Investigate and improve: Examine distractions, task design and place-keeping aids. Repeating training alone does not remove the conditions that permit these errors.
Slips of action
The intended action is clear, but a different action is performed.
Fictional example: While reaching to stop a pump, a person operates a similar-looking neighbouring switch.
Investigate and improve: Check control spacing, identification, feedback, visibility and interruption. Consider clearer separation or error-tolerant design, with competent review and testing.
Lapses of memory
A needed step is forgotten or the person loses their place.
Fictional example: After an interruption, a person omits a required check while believing the sequence is complete.
Investigate and improve: Check the interruption and restart arrangements. Consider point-of-use prompts, reliable step records and proportionate independent checks for critical steps.
Mistakes in planning or judgement
The chosen action is carried out as intended, but the plan or judgement is unsuitable.
Fictional example: A person selects a familiar response to a warning, believing it fits the present conditions.
Investigate and improve: Check what was known, what the rule covered and how the situation was understood. Consider information, decision support and task-specific competence.
Rule-based mistakes
A remembered rule is misapplied, or an unsuitable rule is used. An apparently missing good rule also needs inquiry: was it known, understood and applicable?
Fictional example: A response suitable for pump A is applied to pump B even though their isolation requirements differ.
Investigate and improve: Inspect the actual procedure and its scope, access and revision. Explore interpretation. Missing a step does not by itself prove a deliberate deviation.
Knowledge-based mistakes
An unfamiliar situation is approached through reasoning without a suitable established solution; the resulting judgement is wrong.
Fictional example: An unusual pump condition is interpreted using incomplete information, leading to an inappropriate response.
Investigate and improve: Examine information gaps and available support. Improve escalation, diagnostic aids and arrangements for obtaining competent advice before uncertain work proceeds.
Deliberate deviations: understand why
Deliberate deviations / violations
A rule or procedure is knowingly departed from. The departure is intentional; harm need not be intended. Establish this distinction through evidence.
Fictional example: A required verification is knowingly bypassed to continue a task.
Investigate and improve: Ask why the rule was bypassed, whether it was workable and what the organisation encouraged or tolerated. Fair accountability and system improvements can both be needed.
Routine deviations
Departures become the usual way work is carried out.
Fictional example: A team commonly skips a required handover check and supervisors accept the practice.
Investigate and improve: Compare written arrangements with everyday work, including management knowledge and response. Make the safe method workable and verify that practice changes.
Situational deviations
A departure is associated with conditions such as time pressure, insufficient resources or unsuitable equipment. These conditions do not authorise unsafe work.
Fictional example: The correct equipment is unavailable and a deadline encourages an improvised shortcut.
Investigate and improve: Check resources, conflicting targets and whether people can stop and escalate. Remove the pressure or constraint rather than treating the shortcut as the solution.
Exceptional deviations
A departure occurs in unusual circumstances outside normal practice. This label is not an automatic justification.
Fictional example: During an unfamiliar equipment upset, a person knowingly bypasses a rule while trying to restore operation.
Investigate and improve: Reconstruct the situation and information available. Review abnormal-event preparation, support, escalation and protection; do not infer malicious intent from the outcome.
Check factors across every branch
Performance influencing factors
Conditions affecting performance can sit within the job, the individual or the organisation. Consider them across errors and deviations.
Fictional example: A difficult control layout combines with an interrupted shift and a production target.
Investigate and improve: Identify specific conditions, their evidence and how they interacted. Do not turn a list of factors into unsupported causal conclusions.
Job and task factors
Consider the work itself: equipment, interface design, instructions, workload, environment, timing and communication.
Fictional example: Two similar controls are poorly lit while alarms and interruptions compete for attention.
Investigate and improve: Observe representative work safely, compare intended and actual demands, and test feasible design changes with the people doing the task.
Individual factors
Consider relevant knowledge, experience, abilities and current needs fairly. Observed behaviour does not establish a health diagnosis or intent.
Fictional example: A newly assigned worker does not understand an unfamiliar alarm; a colleague also reports yawning after a long shift.
Investigate and improve: Check induction, understanding, shift and welfare information through appropriate private routes. Yawning alone proves neither fatigue nor the cause of an event; seek competent support when needed.
Organisational factors
Consider staffing, resources, supervision, targets, planning, culture, change management and learning from earlier events.
Fictional example: A known leak remains open because repair responsibility is unclear and closure is recorded without checking the work.
Investigate and improve: Trace decisions, ownership and earlier warnings. Improve the underlying arrangements and verify effectiveness, rather than closing the investigation at “operator error”.
Try the evidence questions
Choose one fictional pump or travel example. What is observed, what remains a hypothesis, which job or organisational factor needs checking, and what improvement would you test? Explain what evidence would change your view.
Explore at your own pace. These are optional thinking prompts: this page does not save answers, assess performance or create a learning record.
Sources and scope
Original SHARElearn overview informed by HSE guidance. The diagram groups concepts for learning; it does not model a causal sequence. Guidance checked 1 November 2026.
Continue with the incident and accident investigation course. The course outline explains its learning, optional reflections and completion requirements.
How does Rasmussen skill-rule-knowledge behaviour help learning?
The skill-rule-knowledge model helps explain why different tasks create different error risks.
Skill-, rule- and knowledge-based behaviour is a learning model, not a way to assign fault to a person. HSG48 explains slips and lapses in familiar skill-based work and rule- versus knowledge-based mistakes; match the control to the task and information available. HSE HSG48 full guide
Skill-based behaviour is fast and automatic. It helps experienced people work efficiently, but it can create slips when controls are similar or attention is interrupted. Rule-based behaviour uses known rules and procedures; it can fail when the wrong rule is selected or the rule is vague. Knowledge-based behaviour happens in unfamiliar situations and is more demanding because the person must reason from first principles.
This matters in emergencies and abnormal operations. A task that is normally skill-based can suddenly become knowledge-based when alarms, plant state and time pressure change. Training and procedures should therefore include abnormal scenarios, not only normal routines.
| Behaviour level | Typical situation | Control implication |
|---|---|---|
| Skill-based | Experienced worker performs routine action. | Design controls to prevent slips and interruptions. HSE HSG48 full guide |
| Rule-based | Worker follows a known procedure or rule. | Make rules clear, usable and tested. HSE HSG48 full guide |
| Knowledge-based | Worker faces an unfamiliar or complex problem. | Provide decision aids, escalation routes and scenario training. HSE HSG48 full guide |
| Transition point | Routine task becomes abnormal. | Use triggers that tell people when to stop and escalate. HSE HSG48 full guide |
| Learning design | Training includes realistic conditions. | Assess competence through scenarios, not just quizzes. HSE HSG48 full guide |
How do job, individual and organisational factors shape performance?
Human reliability improves when the job, the person and the organisation are all considered together.


Human performance is influenced by the task, the person and organisational conditions together. A maintenance investigation should test evidence across all three.
What would be missed by recording only 'operator error'?
It can leave unclear controls, poor access, workload, competence and organisational conditions unexplored.
The diagram is an enquiry framework, not a causal finding about a real person.
Source guidance: HSE HSG48
Job factors include workload, equipment, procedures, lighting, noise, workspace and task complexity. Individual factors include competence, fatigue, health, experience and risk perception. Organisational factors include staffing, leadership, culture, incentives, supervision, resources and change management. HSE introduction to human factors
A weak analysis blames the person. A stronger analysis asks what job and organisational conditions made failure more likely, and what would make success easier next time.
| Factor | Examples | Reliability improvement |
|---|---|---|
| Job | Complex steps, awkward access, poor labels, high noise, similar controls. | Simplify task, improve layout and add prompts. HSE introduction to human factors |
| Individual | New starter, fatigue, stress, unfamiliar equipment. | Competence assessment, supervision and recovery time. HSE introduction to human factors |
| Organisation | Production pressure, understaffing, unclear priorities, poor change control. | Leadership review, resources and clear decision rights. HSE introduction to human factors |
| Interface | Poor display, alarm flood or confusing controls. | Human-centred design and field testing. HSE introduction to human factors |
| Culture | People hide errors or normalise shortcuts. | Just culture, reporting and learning action. HSE introduction to human factors |
How should violations be understood without excusing unsafe behaviour?
Violations need fair analysis because the same visible behaviour can have very different causes.
HSG48 separates routine, situational and exceptional violations. These are categories for understanding how a deviation arose, not automatic findings of blame; test resources, rule usability and supervision before any employment response. HSE HSG48 full guide
Routine, situational and exceptional deviations need different investigations. If evidence suggests deliberate disregard of a serious risk, investigate fairly under the appropriate employment process after testing system causes.
Good managers ask whether the rule is realistic, whether resources are adequate, whether supervisors tolerate the shortcut, whether production targets reward it, and whether workers understand why the rule matters.
| Type | What it looks like | Management response |
|---|---|---|
| Routine violation | Everyone skips the same step. | Investigate normal practice and redesign the task or rule. HSE HSG48 full guide |
| Situational violation | People bypass rule to get work done under pressure. | Review resources, timing, tools and supervision. HSE HSG48 full guide |
| Exceptional violation | Rule broken during unusual event. | Check emergency guidance and escalation routes. HSE HSG48 full guide |
How should just culture and accountability be balanced?
Human factors is not about excusing poor behaviour, but it is also not about lazily blaming operator error.
A just culture asks fair questions before deciding how to respond. Did the person have the right training, tools, time, information and supervision? Was the rule usable? Was the unsafe shortcut normal practice? Were targets, staffing or leadership messages pushing people toward the behaviour? These questions protect learning because they stop the organisation from closing an investigation too early. HSE managing human failures
Accountability still matters. Deliberate reckless behaviour, knowingly bypassing a critical control without reason, falsifying records or ignoring a clear life-critical rule may need formal action. The mature position is to separate human error, at-risk behaviour, system-induced violation and reckless conduct so that learning, fairness and standards can all exist together.
| Situation | Likely interpretation | Better management response | Evidence to consider |
|---|---|---|---|
| Slip or lapse during a well-designed task | Unintended human error. | Improve prompts, layout, checks, interruption control or task design. | Observation, procedure usability, labels, workload and recent interruptions. HSE managing human failures |
| Rule broken because the task cannot realistically be completed otherwise | Situational violation or poor rule design. | Fix resources, access, timing, equipment or procedure before blaming the person. | Worker interviews, supervisor knowledge, production pressure and previous workarounds. HSE managing human failures |
| Shortcut used because it has become normal across the team | Routine drift and weak supervision. | Reset expectations, explain risk, redesign controls and verify follow-up. | Audit findings, toolbox talks, supervisor checks and trend evidence. HSE managing human failures |
| Person knowingly bypasses a critical control for convenience | Deliberate deviation requiring evidence-led investigation; convenience alone does not establish recklessness. | Use fair investigation and accountability while checking system contributors. | Training record, rule clarity, supervision, intent, consequence awareness and past behaviour. HSE managing human failures |
| Record falsified or hazard concealed | Trust and governance failure. | Escalate formally and protect evidence, while checking cultural reasons people hide bad news. | Records, interviews, reporting culture, leadership messages and audit trail. HSE managing human failures |
How does task analysis improve human reliability?
Task analysis breaks work into steps so credible errors and controls can be identified.
A task analysis should be done with the people who perform the work. It should include normal conditions, non-routine conditions, time pressure, tools, communication, environmental constraints, decision points and what happens if the work does not go as planned. HSE HSG48 full guide
The output should improve the job, not just produce a document. It may lead to better layout, fewer steps, clearer labelling, redesigned controls, better supervision, added checklists or removal of unnecessary decisions.
| Output | What it tells you | Action example |
|---|---|---|
| Task steps | Where critical actions occur. | Highlight hold points in procedure. HSE HSG48 full guide |
| Error modes | How a person could slip, forget, misunderstand or violate. | Add prompts, interlocks or independent checks. HSE HSG48 full guide |
| Performance influencing factors | What makes success harder or easier. | Improve lighting, access, staffing or time. HSE HSG48 full guide |
| Controls | How the task is supported. | Add engineering control before relying on memory. HSE HSG48 full guide |
| Verification | How success is checked. | Supervisor observation or second-person check. HSE HSG48 full guide |
How do ergonomics and workplace design affect reliability?
Ergonomics makes work fit people rather than expecting people to overcome poor design.
Physical ergonomics includes reach, posture, force, visibility, manual handling and access. Cognitive ergonomics includes displays, alarms, mental workload, decision support and information design. Organisational ergonomics includes staffing, work patterns, communication and culture. HSE control rooms
In practical terms, reliability improves when controls are distinguishable, information is easy to interpret, labels are visible, tools fit the job, and the person can perform the task without awkward movement or unnecessary memory load.
| Design issue | Error risk | Better design |
|---|---|---|
| Similar buttons | Wrong control selected. | Different shape, colour, spacing and confirmation. HSE control rooms |
| Poor access | Worker takes unsafe shortcut. | Redesign platform, access or task sequence. HSE control rooms |
| Hard-to-read display | Wrong value used for decision. | Improve display, units, contrast and alarm limits. HSE control rooms |
| Heavy or awkward tool | Fatigue and rushed work. | Tool redesign, mechanical aid or task rotation. HSE control rooms |
| Noisy environment | Instruction misunderstood. | Radio protocol, visual confirmation and quieter briefing area. HSE control rooms |
What matters in control-room design and monitoring roles?
Control rooms rely heavily on human reliability because operators must maintain situation awareness and respond correctly.
A good control room supports attention, diagnosis and action. It should not overload people with low-value alarms, scattered information, poor displays or ambiguous plant status. It should also consider staffing, fatigue, handover, abnormal scenarios, lighting, seating, noise and emergency communications. HSE control rooms
Control-room design is not only for major hazard sites. Traffic rooms, security rooms, building management systems, CCTV suites, logistics hubs and energy control points all depend on people recognising changes and responding in time.
| Area | Good practice | Evidence |
|---|---|---|
| Alarm management | Alarms are prioritised, actionable and reviewed. | Alarm dashboard and rationalisation record. HSE control rooms |
| Display design | Information supports diagnosis and trend recognition. | Operator feedback and interface review. HSE control rooms |
| Handover | Structured handover covers abnormalities, isolations and inhibited systems. | Handover log and readback check. HSE control rooms |
| Fatigue | Shift design manages alertness and recovery. | Fatigue assessment and rota review. HSE control rooms |
| Emergency communication | Messages are clear, tested and role-specific. | Drill records and emergency plan review. HSE control rooms |
How does fatigue affect human reliability?
Fatigue reduces attention, memory, reaction time, judgement and willingness to challenge unsafe conditions.
Fatigue is not just sleepiness. It can come from long hours, shift work, early starts, night work, commuting, overtime, workload, stress, illness, caring responsibilities and insufficient recovery. It can interact with other human factors such as underload, alarm monitoring, heat and safety-critical driving. HSE fatigue and shiftwork
A serious organisation designs fatigue controls into work planning. It does not wait for workers to self-declare fatigue after the job has already become unsafe.
| Situation | Risk | Control |
|---|---|---|
| Night shift monitoring | Reduced vigilance and slower alarm response. | Task rotation, breaks and alarm support. HSE fatigue and shiftwork |
| Overtime after shutdown | Errors during isolation or reinstatement. | Shift limits and high-risk task scheduling. HSE fatigue and shiftwork |
| Long commute before shift | Reduced alertness before work begins. | Rota planning and fatigue conversation. HSE fatigue and shiftwork |
| High workload and low rest | Skipped checks and poor decisions. | Workload review and supervisor escalation. HSE fatigue and shiftwork |
| Safety-critical driving | Microsleeps and slower reactions. | Journey planning and no-drive triggers. HSE fatigue and shiftwork |
How can organisations improve human reliability?
Human reliability improves when controls support people before, during and after the task.
A human reliability estimate depends on the defined task, baseline data, time pressure, display design and other performance-shaping assumptions. HSG48 warns that quantified methods are better suited to well-learned routine tasks and require care in unfamiliar conditions. Record uncertainty and never substitute a generic probability for field barrier evidence. HSE HSG48 full guide HSE managing human failures
The strongest interventions remove the error opportunity, reduce complexity, make hazards visible, support correct action and detect failure early. Training is important, but it is only one layer. Reliability also needs good design, tested procedures, competent supervision, workload control, feedback and learning.
Where human action is claimed as a barrier in a risk assessment, the organisation should be able to show why that action is dependable. What is the cue? How much time is available? What could distract the person? What if the person is new, tired or interrupted? How is the response verified?
| Approach | Example | Why it helps |
|---|---|---|
| Remove choice | Use keyed connections or interlocks. | Prevents wrong selection. HSE HSG48 full guide |
| Make cues clear | Use visible alarms, labels and limits. | Improves recognition and response. HSE HSG48 full guide |
| Reduce memory dependence | Use checklists and prompts. | Prevents lapses. HSE HSG48 full guide |
| Practice abnormal scenarios | Use tabletop or simulator exercises. | Improves knowledge-based performance. HSE HSG48 full guide |
| Verify critical action | Use second-person check or independent instrument. | Detects failure before consequence. HSE HSG48 full guide |
| Learn from weak signals | Review near misses and workarounds. | Fixes drift before incident. HSE HSG48 full guide |
What does a worked human-reliability task example look like?
A task-step example shows how the theory becomes a practical control plan.
For the conveyor isolation and jam-clearing example, compare the written sequence with the real controls and line labels, then test whether a slip can be detected or physically prevented. A sign-off or refresher alone leaves the same error path open. HSE HSG48 full guide HSE procedures
Consider a maintenance task where a worker must isolate a conveyor, clear a jam, check the area and return the machine to service. The risk is not only the jam itself. The human-reliability question is whether the task gives the person clear cues, enough time, usable equipment, competent supervision and a recovery route if something is missed.
This type of analysis is useful for learners because it connects slips, lapses, mistakes, violations and performance influencing factors to real safeguards. It is also useful for supervisors because it shows what evidence should be checked before the task is treated as controlled.
| Task step | Possible failure | Performance influencing factors | Safeguards | Recovery controls and evidence |
|---|---|---|---|---|
| Identify the blockage | Worker reaches into the nip point before understanding stored energy. | Noise, poor visibility, production pressure and routine jam clearing. | Stop-work rule, viewing point, guarded access and supervisor briefing. | Near-miss reporting and supervisor observation of jam-clearing tasks. HSE HSG48 full guide |
| Isolate and lock off | Wrong isolator selected or lock not applied. | Poor labels, similar panels, time pressure and interruptions. | Unique labels, isolation procedure, lock-off kit and try-start test. | Isolation certificate, lock register and spot checks. HSE HSG48 full guide |
| Remove guard or access panel | Guard removed before isolation is proven. | Awkward access, weak procedure and past shortcuts. | Interlocked guard, permit or task checklist, and hold point. | Workface verification and photo or supervisor sign-off where proportionate. HSE HSG48 full guide |
| Clear the blockage | Tool slips, body enters danger zone or unexpected restart occurs. | Manual force, fatigue, poor tool choice and limited space. | Correct tools, zero-energy confirmation and controlled restart rules. | Post-task debrief and defect action if jams are frequent. HSE HSG48 full guide |
| Reinstate and restart | Guard not replaced or people remain inside the danger area. | Distraction, shift change and poor communication. | Final area check, two-person confirmation for high-risk tasks and restart warning. | Restart checklist, guarding inspection and action close-out evidence. HSE HSG48 full guide |
How does a human error finding become a better investigation?
A good investigation treats error as evidence of a system problem to understand, not the end of the analysis.
Imagine a maintenance worker removes a guard to clear a blockage and the machine is restarted before the guard is replaced. A weak report says the worker failed to follow the rule. A stronger report asks why the blockage was frequent, why isolation was not applied, why the guard design made cleaning difficult, whether supervisors knew the workaround, whether production pressure existed and whether the procedure could be followed in real conditions. HSE managing human failures
This style of analysis produces stronger actions because it changes the conditions that made the failure credible.
| Layer | Weak finding | Stronger review |
|---|---|---|
| Person | Worker made a mistake. | Was the worker competent, fatigued, interrupted or under pressure? HSE managing human failures |
| Task | Procedure not followed. | Was the procedure usable and was isolation practical for blockage clearing? HSE managing human failures |
| Equipment | Guard was removed. | Could the blockage be cleared without removing the guard? HSE managing human failures |
| Supervision | Supervisor did not see it. | Was this shortcut known, tolerated or hidden by workload? HSE managing human failures |
| Organisation | More training required. | Fix blockage cause, guarding, isolation method, supervision and production pressure. HSE managing human failures |
What evidence shows human reliability is being managed?
Evidence should show that error traps have been identified, tasks improved and controls checked in practice.
Good evidence includes task analysis, procedure review, observations, competence assessments, design reviews, error reports, audit findings, training scenarios, workload assessments and action verification. The best evidence proves the organisation has improved the system, not merely reminded the worker. HSE managing human failures
For high-risk work, managers should be able to trace a control from risk assessment to procedure, training, supervision, monitoring and review.
| Evidence | What it shows | Quality check |
|---|---|---|
| Task analysis | Critical steps and error modes are known. | Was it done with workers? HSE managing human failures |
| Procedure review | Procedure is current and usable. | Was it tested at the workface? HSE managing human failures |
| Observed assessment | Competence is demonstrated in realistic conditions. | Does it include abnormal conditions? HSE managing human failures |
| Incident learning | Human factors are analysed beyond blame. | Are actions systemic? HSE managing human failures |
| Audit findings | Controls are checked and improved. | Are actions verified? HSE managing human failures |
| Worker feedback | Workarounds and weak signals are visible. | Is feedback acted on? HSE managing human failures |
Which duties apply in Great Britain and Northern Ireland?
Choose the law for the actual site and task. A clinical pattern, management guide or voluntary standard does not replace the nation-specific duty.
Safe work, equipment and equality duties may apply, but investigate the real system and personal circumstances before drawing a legal conclusion. Management of Health and Safety at Work Regulations 1999 Management of Health and Safety at Work Regulations (NI) 2000
| Decision | Great Britain law | Northern Ireland law | Applicability |
|---|---|---|---|
| General safe systems | Health and Safety at Work etc. Act 1974 GB law | Health and Safety at Work (NI) Order 1978 NI law | Check site, task and specified trigger. |
| Assessment and work planning | Management of Health and Safety at Work Regulations 1999 GB law | Management of Health and Safety at Work Regulations (NI) 2000 NI law | Check site, task and specified trigger. |
| Equipment and interfaces | Provision and Use of Work Equipment Regulations 1998 GB law | Provision and Use of Work Equipment Regulations (NI) 1999 NI law | Check site, task and specified trigger. |
| Workplace conditions | Workplace (Health, Safety and Welfare) Regulations 1992 GB law | Workplace (Health, Safety and Welfare) Regulations (NI) 1993 NI law | Check site, task and specified trigger. |
| Disability adjustments where triggered | Equality Act 2010 GB law | Disability Discrimination Act 1995 as amended for NI NI law | Check site, task and specified trigger. |
How can the hierarchy of controls reduce error-likely conditions and the consequences of human failure?
ERICPD is used here as a planning mnemonic. The linked HSE five-level hierarchy is the official source for the order and relative reliability of controls; the two labels are not identical.
Start with the exposure or failure path and prefer removal or physical redesign before procedures or PPE.
ERICPD is a planning mnemonic: Isolate generally maps to engineering, Discipline sustains controls, and the five-level hierarchy names substitution separately. Each candidate requires competent task assessment. HSE five-level hierarchy HSE five-level hierarchy
How can the ERICPD hierarchy of controls reduce error-likely conditions and the consequences of human failure?

| ERICPD stage | Five-level mapping | Task intervention | Owner and check | Failure / stop |
|---|---|---|---|---|
| Eliminate | Elimination | Remove the wrong-valve choice by plant or route redesign. | Engineer tests change. | Error path remains: add controls. HSE managing human failures |
| Reduce | Substitution | Use physically distinct valve design as an engineering error-reduction measure where suitable. Simplify the lineup sequence as an administrative task-design control; neither measure is hazard substitution. | Operators test usability. | Confusion persists: revise. HSE managing human failures |
| Isolate | Engineering | Physically segregate or lock out the incompatible valve. | Field lead checks state. | Isolation unproved: hold. HSE managing human failures |
| Control: physical | Engineering | Use clear labels, position feedback and independent process protection where justified. | Engineer verifies design. | Safeguard fails: stop. HSE control systems guidance |
| Control: method | Administrative | Use concise task steps, independent checks and manageable workload. | Supervisor observes task. | Ambiguity: pause. HSE procedures |
| PPE | PPE | Protect residual splash exposure; PPE cannot prevent a wrong lineup. | Assessor checks fit. | Required PPE absent: hold. HSE managing human failures |
| Discipline | Sustains controls | Investigate failures fairly and verify corrective actions. | Manager checks effectiveness. | Repeat failure: redesign. HSE managing human failures |
How can the ISO 45001 hierarchy of controls reduce error-likely conditions and the consequences of human failure?

| ESEAP control level | Five-level mapping | Task intervention | Owner and check | Failure / stop |
|---|---|---|---|---|
| Elimination | Elimination | Remove the wrong-valve choice by plant or route redesign. | Engineer tests change. | Error path remains: add controls. HSE managing human failures |
| Engineering controls / Administrative controls | Substitution | Use physically distinct valve design as an engineering error-reduction measure where suitable. Simplify the lineup sequence as an administrative task-design control; neither measure is hazard substitution. | Operators test usability. | Confusion persists: revise. HSE managing human failures |
| Engineering controls | Engineering | Physically segregate or lock out the incompatible valve. | Field lead checks state. | Isolation unproved: hold. HSE managing human failures |
| Engineering controls | Engineering | Use clear labels, position feedback and independent process protection where justified. | Engineer verifies design. | Safeguard fails: stop. HSE control systems guidance |
| Administrative controls | Administrative | Use concise task steps, independent checks and manageable workload. | Supervisor observes task. | Ambiguity: pause. HSE procedures |
| PPE | PPE | Protect residual splash exposure; PPE cannot prevent a wrong lineup. | Assessor checks fit. | Required PPE absent: hold. HSE managing human failures |
| Administrative controls | Sustains controls | Investigate failures fairly and verify corrective actions. | Manager checks effectiveness. | Repeat failure: redesign. HSE managing human failures |
How should management verify controls for this task?
For wrong-valve maintenance step, error classification and system redesign, the management check should start with a real control decision: Remove the wrong-valve choice by plant or route redesign. Name the person who will test it, keep evidence from the actual work, and reopen the assessment when the failure condition in the hierarchy table occurs. HSE management-system guidance.
A review should compare the planned control with what workers and supervisors can use in practice. Record the defect, owner, interim protection, verification and next review trigger so that a policy statement or certificate does not stand in for a working control.
How could BuildOut Ltd manage this in practice?

BuildOut Ltd would examine why an error is likely and improve the task or equipment before relying on another reminder to be careful.
BuildOut Ltd · practical example
Make similar plant controls harder to confuse
The key lesson Human error is foreseeable. Design, workload, information and supervision influence its likelihood and consequences.
The situation: A worker selects the wrong control on unfamiliar hired equipment but notices before movement occurs. Two controls look similar, lighting is poor and the team is under time pressure.
Why this matters: Blaming the individual can leave the confusing controls and rushed setup ready to trap the next person.
How BuildOut Ltd would manage it
- Understand the task — Site Manager. Secure the immediate situation and hear the worker’s account. Identify the intended action, selected control and conditions present without assuming a deliberate shortcut.
- Examine influencing factors — Health and Safety Manager. Review visibility, control identification, equipment familiarity, interruptions, fatigue, workload and supervision. Look for similar confusion in other foreseeable tasks.
- Improve the arrangement — Plant and Procurement Coordinator. Ask the supplier and competent equipment specialists about a suitable safer option or approved improvement. Do not modify safety-related controls through an improvised site fix.
- Prepare the user — Trade Supervisor. Confirm task-specific familiarisation and usable information, remove avoidable time pressure and set appropriate supervision while competence is established.
- Check error tolerance — Project Manager. Review whether the revised arrangement prevents or detects the likely mistake before harm. Use controlled observation and feedback, and carry the specification into future hire decisions.
When the conditions change
- Recognise the trigger
- A user cannot reliably distinguish the hired equipment controls needed for the task.
- Make the immediate decision
- The Site Manager holds that equipment use; a warning to concentrate is not the release decision.
- Verify the next step
- The Site Manager confirms the competent equipment decision, clear control information, familiarised user and appropriate supervision through controlled assessment.
What good looks like
The company can explain what made the error likely and what changed in the task. The improvement protects more than the person involved.
Evidence to look for: Task account, influencing-factor review, equipment decision, familiarisation and observed improvement.
Common mistake to avoid: Closing the event as “operator error” with no examination of design or work pressure.
Apply this to your work: What makes a foreseeable mistake easy to make in your workplace?
Guidance behind the management approach: HSE: managing human failures. Use the topic's legal and technical guidance for the applicable work and location.
BuildOut Ltd is a construction and refurbishment contractor. Human reliability matters when workers isolate temporary electrics, operate mobile plant, fit guards, use access equipment, follow lifting plans, work at height, control dust and coordinate contractors on changing sites. HSE introduction to human factors
| Management element | How the business would manage it | Evidence to review |
|---|---|---|
| Assessing | BuildOut identifies tasks where one wrong action could cause serious harm, such as isolation, lifting, plant movement, edge protection changes and confined-space entry. | Safety-critical task list and risk register. HSE introduction to human factors |
| Analysing | The HSE adviser reviews slips, lapses, mistakes and violations using worker walk-throughs and incident data. | Task analysis and error prediction sheets. HSE introduction to human factors |
| Implementing | Controls include physical segregation, lockable isolations, simple checklists, labelled plant, supervisor hold points and workface briefings. | Method statements, inspection records and permit checks. HSE introduction to human factors |
| Training | Supervisors receive training on human factors, just culture and how to avoid shallow blame after incidents. | Training matrix and scenario assessment. HSE introduction to human factors |
| Checking | First-line supervisors observe high-risk tasks; second-line audits sample procedure usability; third-line specialists review plant interface and temporary works controls. | Assurance plan and audit findings. HSE introduction to human factors |
| Learning | Near misses are coded for failure type and reviewed for system actions, not just worker reminders. | Learning log and action verification. HSE introduction to human factors |
What must each role demonstrate?
Record an observed task decision or simulation, the assessor and evidence, and a trigger for reassessment.
Briefing attendance alone cannot prove that a person recognises the hold or referral point. HSE HSG48 full guide
| Role | Demonstration | Assessor and record | Reassess when |
|---|---|---|---|
| Worker | Describe actual task, interruption and wrong-valve traps. | Assessor observes walkthrough. | Task changes. HSE HSG48 full guide |
| Supervisor | Classify error/violation only after factual investigation. | HF adviser reviews case. | New evidence. HSE managing human failures |
| Designer | Remove confusing interfaces and enable verification. | User trial and peer review. | Modification. HSE introduction to human factors |
| Risk analyst | Document task and assumptions before estimating failure probability. | Technical peer reviews model. | Inputs or context change. HSE HSG48 full guide |
| Manager | Verify corrective controls rather than default retraining. | Senior reviewer samples effectiveness. | Repeat event. HSE managing human failures |
How should this be used for NEBOSH Diploma study?
Diploma answers should apply the theory to realistic workplace decisions and evidence.
A strong answer explains slips, lapses, mistakes and violations, then links them to job, individual and organisational factors. It should show how task analysis and ergonomic design can reduce the likelihood of failure. It should avoid phrases such as 'carelessness' unless there is evidence. HSE introduction to human factors
In scenario questions, use the visible facts: time pressure, fatigue, poor lighting, missing supervision, difficult access, confusing alarms, unclear procedure, production pressure, weak training or repeated previous near misses.
| Question | Good answer | Weak answer |
|---|---|---|
| Why did a worker bypass a guard? | Discuss violation type, task design, blockage, access, supervision and culture. | Worker was negligent. HSE introduction to human factors |
| How can slips be reduced? | Use design, labelling, spacing, interlocks and prompts. | Tell workers to concentrate. HSE introduction to human factors |
| What is SRK behaviour? | Explain skill, rule and knowledge modes with examples. | List the words only. HSE introduction to human factors |
| How does task analysis help? | Breaks work into steps and identifies credible failures. | It is a checklist. HSE introduction to human factors |
| How is reliability improved? | Design for success, verify controls and learn from weak signals. | More training. HSE introduction to human factors |
What warning signs show human reliability is weak?
Warning signs often appear before harm: repeated workarounds, unreliable procedures, blame-heavy reports and controls that depend on memory.
Warning signs are included because failure usually appears before a serious event. Treat these points as prompts for inspection, audit, supervision and management review rather than as simple compliance statements. HSE managing human failures
| Warning sign | How it can cause harm | Action |
|---|---|---|
| Same error repeats | The task contains an uncorrected error trap. | Run task analysis and redesign. HSE managing human failures |
| Rules regularly bypassed | Controls may be impractical or poorly supervised. | Investigate violation type and fix conditions. HSE managing human failures |
| Procedures do not match work | People improvise and critical steps are missed. | Rewrite with workers and test in the field. HSE managing human failures |
| Actions say retrain only | System causes are left unchanged. | Set engineering, supervision or work-design actions. HSE managing human failures |
| No worker involvement | Managers miss work-as-done reality. | Use observation and consultation. HSE managing human failures |
What do the acronyms and key terms mean?
Acronyms should be understood before they are used in assessments, briefings, audits or learning answers.
Acronyms can exclude newer readers if they are not explained. This section keeps the main terms available at the end of the page so the article stays readable while still supporting learners and audit users.
| Acronym | Meaning | Plain-English use |
|---|---|---|
| HF | Human factors | Job, individual and organisational factors affecting performance. |
| SRK | Skill-rule-knowledge | Rasmussen model of behaviour modes. |
| SCTA | Safety critical task analysis | Task analysis for work where human performance is critical. |
| PIF | Performance influencing factor | A condition that makes good or poor performance more likely. |
| DSE | Display screen equipment | Screens and related workstations; relevant to ergonomic and control-room contexts. |
Unlock another resource
You have used this month’s two free downloads. Publish a post in your own words to unlock one more resource, or choose SHARE Individual for 10 downloads per month.
You decide whether to share. If you do, use the relevant platform disclosure tools and do not make claims you do not genuinely hold.