
SHARE Knowledge Hub
What is occupational cardiovascular disease?
Work can expose people to acute hazards such as carbon monoxide and heat. Long hours, poor recovery and work-related stress also need control because they can affect health and safe performance. A symptom or roster alone cannot establish the cause of cardiovascular disease. Act urgently on heart attack or stroke signs, and use confidential clinical and occupational-health advice for individual capability decisions.
Understanding What is occupational cardiovascular disease?
Cardiovascular disease, or CVD, is a group of conditions affecting the heart or blood vessels. It includes coronary heart disease, stroke and transient ischaemic attack, peripheral arterial disease and aortic disease. Hypertension, arrhythmias and heart failure are closely relevant conditions. Work may contribute to risk, aggravate an existing condition, trigger symptoms or determine whether a medical event becomes fatal; work presence alone does not establish that work caused an individual's disease.
Why this matters at work
Association means two variables occur together more often than expected; it does not automatically mean one caused the other. Confounding occurs when another factor influences both exposure and disease. Selection can arise when healthier people remain in demanding jobs. Exposure misclassification is common when a job title or one survey stands in for actual hours, dose, peaks, shift history or control conditions.
Carbon monoxide is colourless and odourless. It binds to haemoglobin and prevents blood from carrying oxygen effectively to cells and organs. This direct mechanism can cause headache, dizziness, nausea, confusion, chest pain, collapse, brain injury, cardiac injury and death. People with cardiovascular disease may be particularly vulnerable to oxygen-delivery impairment.
How organisations manage this in practice
Choose controls within management's reach, such as better staffing and recovery, reduced process exposure, suitable welfare and safer work demands. Identify responsibilities, resources and verification. Check implementation through actual hours, break attainment, exposure evidence, defect closure and worker experience. Clinical risk factors and restrictions need appropriate confidential advice, not line-manager diagnosis. Avoid ranking teams by health measures or interpreting a small number of events as proof of safety. Review after significant change or a credible concern. Apply the appropriate national general and hazard-specific duties rather than treating a voluntary wellbeing activity as the whole assessment.
Work-design engineering can also reduce sustained static work: adjustable stations, automated handling, local controls, task variety and accessible welfare. Automation should be assessed for alarm load, monitoring monotony and reduced staffing. Human factors determine whether the engineered system is actually usable under pressure.
Review at agreed milestones and after symptoms, treatment change or work change. A setback is information, not misconduct. Keep clinical detail confidential and record only necessary restriction, consent, action and review. Emergency colleagues need only the information necessary for a voluntary personal plan.
Chest pain, severe breathlessness, collapse, suspected stroke symptoms, loss of consciousness or suspected carbon monoxide exposure require the organisation's emergency response and medical assessment route. Workplace managers should not diagnose cardiovascular disease; they should control workplace contributors, support safe work and use occupational health advice where work capability or safety-critical duties are affected.
Who needs to understand occupational cardiovascular disease?
Occupational cardiovascular disease should be understood by anyone who designs work, manages shifts, controls exposure or makes safe-work decisions.
Workers
Need to recognise symptoms, report exposure concerns and understand how work patterns can affect health.
Line managers
Need to manage workload, fatigue, stress, return to work and safety-critical restrictions.
H&S advisers
Need to assess CO, diesel exhaust, heat, noise, fatigue, stress and work-design controls.
Occupational health
Need to advise on work impact, vulnerability, surveillance and fitness for safety-critical roles.
HR and wellbeing leads
Need to link wellbeing campaigns with work design and confidentiality.
Senior leaders
Need to set limits on unsafe work patterns, resourcing gaps and unmanaged exposure.
Remove the hazardous source before relying on a health or monitoring check
An indoor petrol-powered-equipment example begins with source removal or a safer suitable method, not a routine plan to operate beside a monitor. Assessment and competent control of any remaining combustion risk come before use. Monitoring can support verification for its defined purpose; it does not make an unsuitable indoor source acceptable.

Review the work without diagnosing the driver

Full written explanation
Delivery example: review combustion sources, workload and recovery; the photograph establishes no illness or measured exposure.
- Review combustion exposure. Identify engines, location, ventilation and who could be exposed. No visible smoke does not establish clean air.
- Review demands and recovery. Examine actual hours, workload, breaks and recovery. A route sheet or legal-hours check alone cannot prove control.
- Use appropriate health advice. Agree relevant support privately. A job title, tired appearance or possible work contribution cannot establish a diagnosis.
Change the pathway
- Control the actual source. Resolve the task-specific exposure question without waiting for health-test results.
- Change the work design. Review staffing, demands and shifts rather than asking people simply to cope.
- Keep urgent help immediate. Suspected heart attack, stroke or severe breathing emergency follows the existing emergency route.
Evidence check: Use the full topic’s existing emergency and legal routes. No heart model, scene or work history predicts an individual diagnosis, cause or fitness.
Existing urgent symptoms and emergency-help route
Primary references: NHS: suspected heart attack and immediate help · HSE: work design and fatigue (GB) · HSE: heat-stress factors and control (GB)
Open the complete HD image (new tab)Download image

Existing urgent symptoms and emergency-help route
Primary references: NHS: suspected heart attack and immediate help · HSE: work design and fatigue (GB) · HSE: heat-stress factors and control (GB)
Keep acute exposure, general work design and an individual safe-work review as separate questions. If people become unwell, use the existing emergency and exposure route before a wellbeing discussion. Later, review the real task and relevant functional advice without deciding from symptoms that an individual’s condition was caused by work. Preserve confidential health information and the correct location-specific duties.
Crownway: a portable petrol machine is proposed indoors
Illustrative example. A contractor brings petrol-powered equipment into an enclosed maintenance area and offers a portable monitor as assurance.
Decision. The host owner holds the proposed method and requires a suitable safer source or method and competent assessment of residual risk.
Evidence to check. Actual location, equipment and exhaust route, safer alternatives, control function and authorised task conditions.
Hold or escalation point. Do not release work because a monitor is present, one reading appears normal or the doors are briefly open.
Follow-up. Verify the approved method in use and update contractor procurement and site briefing to prevent recurrence.
Connect work factors with prevention, not a diagnosis
Work factors may contribute to cardiovascular risk. A qualified mechanism explanation and a workplace history cannot establish why an individual has cardiovascular disease.
Urgent help and work-factor control are parallel

Full written explanation
An illustrative normal production setting supplies context for the WORK AND EXPOSURE track only. Ordinary uninjured colleagues review inert papers outside a production area behind glass; an unoccupied room is visible separately. Picture key: 1 identifies the production area; 2 identifies inert work facts; 3 identifies the unoccupied room. The scene establishes no actual heat source, temperature, carbon monoxide, exhaust, exposure, work rate, fatigue, recovery, work cover, cooling, welfare adequacy, health record, clinical event, care or fitness result. No person is depicted as having symptoms, needing emergency treatment or receiving clinical advice. The complete explanation keeps two independent tracks. PERSON NEEDING HELP retains the exact existing emergency-recognition and emergency-advice checks. WORK AND EXPOSURE retains the separate assessment of actual heat, workload, clothing, recovery and relevant combustion exposure, followed by control of work factors and appropriate private clinical or occupational-health support. Arrows remain within each track; urgent help never passes through paperwork, proof of work causation, a manager, work cover or an occupational-health appointment. The band reads URGENT HELP MUST NOT WAIT FOR WORK-CAUSATION OR MANAGEMENT REVIEW. All four full original checks, the full hold, responsible roles, evidence limits and both delivery-work and hot-production cases accompany the explanation. Independent check and lane headings are unnumbered, separate from the literal picture key. A photograph, exposure history or health check is not a diagnosis or control certificate. The unoccupied room proves no recovery or cooling arrangement and supplies no treatment or rest instruction. Use the complete topic for existing urgent and country-specific clinical routes, the normal-only cardiovascular illustration, distinct exposure and work-design pathways, individual support, consent and confidentiality, GB and NI workplace requirements, current source limits and task-specific controls. No symptom demonstration, new triage, heart or carbon-monoxide mechanism, hydration, cooling, protective-equipment method, exposure threshold, fitness rule or permission is supplied.
Hot-production comparison: a person develops symptoms during demanding work; response and prevention have distinct roles.
- Recognise an emergency. Call 999 for suspected heart attack or stroke, severe breathing difficulty or collapse with abnormal response.
- Follow emergency advice. Use emergency arrangements and call-handler advice. Do not ask the person to drive themselves.
- Review actual work factors. Assess heat source, workload, clothing, recovery and relevant combustion exposure with competent support.
- Agree and check changes. Control the work factors and use appropriate private clinical/OH advice for individual support.
When the evidence does not fit: Do not delay urgent help to prove a work cause or obtain a manager’s permission. Do not use a photograph, exposure history or health check as a diagnosis or control certificate.
Who acts: Emergency responders for an actual emergency; responsible work owners and qualified clinical/OH advisers for their respective decisions.
Changed workplace
Delivery work: Review exhaust sources and demands while respecting private health advice.
Hot production: Obtain appropriate help and address the actual heat/workload conditions.
Evidence check: Use the full topic’s existing emergency and legal routes. No heart model, scene or work history predicts an individual diagnosis, cause or fitness.
Existing urgent symptoms and emergency-help route
Primary references: NHS: suspected heart attack and immediate help · HSE: work design and fatigue (GB) · HSE: heat-stress factors and control (GB)
Open the complete HD image (new tab)Download image

Existing urgent symptoms and emergency-help route
Primary references: NHS: suspected heart attack and immediate help · HSE: work design and fatigue (GB) · HSE: heat-stress factors and control (GB)

Work factors
Identify relevant exposure and workload conditions, such as combustion sources, long hours and recovery opportunities.
Mechanism and uncertainty
Keep oxygen transport, heart pumping and coronary supply distinct. A possible contribution is not an inevitable cause-to-disease chain.
Action
Control the work factors, agree appropriate support and follow the existing clinical or emergency route for the concern presented.
Do not delay urgent help while trying to prove a work cause. No illustration predicts an individual’s diagnosis or fitness.
What are the key facts about occupational cardiovascular disease?
The key facts are that acute exposures, work design and an individual’s cardiovascular condition call for different controls and decisions.
Work is one part of total risk
Personal and medical factors matter, but work can still create or worsen risk.
Carbon monoxide is an acute hazard
It reduces oxygen delivery and can rapidly affect the heart and brain.
Long hours and fatigue matter
Poor recovery and excessive working time can contribute to ill health and unsafe performance.
Shift work is a design issue
Night work and rotating shifts can disrupt sleep, eating, recovery and alertness.
Stress risk assessment is a control
The HSE Management Standards are a practical route for controlling work-related stressors.
Privacy still applies
Health conditions should be handled confidentially and work impact should be recorded proportionately.
What is occupational cardiovascular disease?
This topic covers acute workplace exposures that can strain the heart or circulation, and safe-work decisions when a person has a cardiovascular condition. Work design also matters for general health and performance.
Heart and circulatory conditions include ischaemic heart disease, angina, heart attack, arrhythmia, hypertension and stroke. A workplace exposure or demanding task may require urgent control or a safe-work review, but a manager cannot infer the cause of an individual condition from a job title or symptom.
This page separates carbon monoxide and heat as immediate exposure hazards from hours, shifts, fatigue and stress as work-design risks that HSE asks employers to assess. These factors warrant control even when the cause of an individual cardiovascular event is uncertain. Diesel exhaust and noise need their own hazard assessments.
The practical focus is prevention and safe support: reduce the work factors that can be controlled, use occupational health advice where individual vulnerability affects work, and avoid treating cardiovascular health as only a personal lifestyle issue.
| Aspect | Details | Workplace relevance |
|---|---|---|
| Condition group | Heart and circulatory conditions that may affect safe work. | Requires both wellbeing and risk-control thinking. |
| Acute work hazard | Carbon monoxide exposure or heat strain. | Emergency and exposure controls may be needed. |
| Work-design hazard | Long hours, shift work and stress need separate health and safety controls. | Work design and monitoring matter. |
| Common outcomes | Angina, heart attack, arrhythmia, hypertension or stroke. | Safe-work and OH advice may be required. |
| Boundary | Managers do not diagnose. | Focus on work risk, symptoms at work and functional impact. |
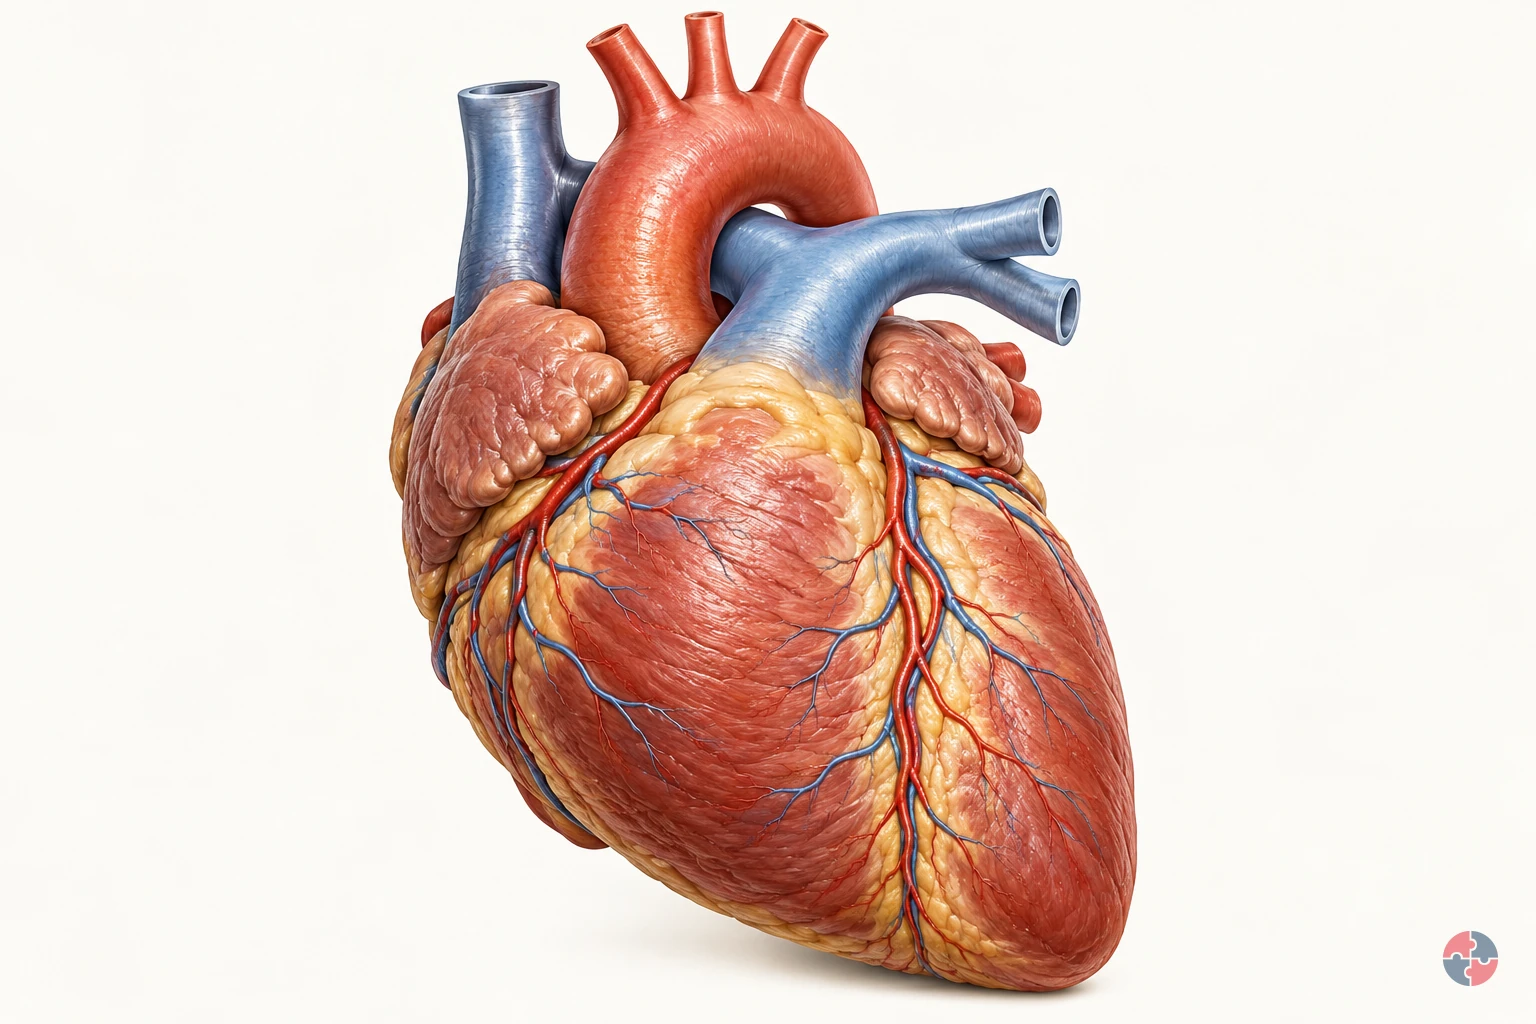

How does the heart circulate blood, and how do coronary disease, heart attack and cardiac arrest differ?
Interactive anatomy · Heart function, coronary supply and emergencies · Updated 2026-10-23
Read all anatomy and process explanations without the viewer
Adult anatomy and emergency recognition, not diagnosis, risk calculation or practical CPR certification. Child resuscitation or congenital-heart treatment Medication selection, dosing or treatment recommendations ECG interpretation, live vital signs or AED shock decisions Personal risk, damage countdown or return-to-work clearance The action panel is available before any model, login or quiz. Cardiovascular disease has many causes and forms; this coronary example covers only its stated mechanism.
Right atrium
Receives blood returning from the body. This upper chamber belongs to the anatomical right side, shown on the viewer’s left. East London NHS Foundation Trust: Physical Health Training — cardiovascular system · University Hospitals Bristol NHS-hosted resource: Understanding the circulatory system — patient/family information
Right ventricle
Pumps blood towards the lungs. Blood moves from this lower chamber into the pulmonary artery. East London NHS Foundation Trust: Physical Health Training — cardiovascular system
Pulmonary artery
Carries blood away from the heart to the lungs. It carries relatively oxygen-poor blood. An artery is defined by direction away from the heart, not by oxygen content. East London NHS Foundation Trust: Physical Health Training — cardiovascular system
Lung exchange
Blood gains oxygen and releases carbon dioxide at the lungs. The lungs bring air close to blood in small vessels while keeping them in separate spaces. Oxygen and carbon dioxide cross thin tissue boundaries in opposite directions. The exchange label connects the respiratory and circulation lessons; it does not show air entering an open vessel or provide a measurement of gas exchange in a person. Frimley Health NHS Foundation Trust: How your lungs work
Pulmonary veins
Return oxygen-rich blood from lungs to the heart. These veins enter the left atrium. Veins return blood towards the heart even when that blood is oxygen-rich. East London NHS Foundation Trust: Physical Health Training — cardiovascular system
Left atrium
Receives blood arriving from the lungs. It passes blood towards the left ventricle through the intervening valve. East London NHS Foundation Trust: Physical Health Training — cardiovascular system · University Hospitals Bristol NHS-hosted resource: Understanding the circulatory system — patient/family information
Left ventricle
Pumps blood into the body’s circulation. Its contraction sends blood through the aortic valve into the aorta. East London NHS Foundation Trust: Physical Health Training — cardiovascular system · University Hospitals Bristol NHS-hosted resource: Understanding the circulatory system — patient/family information
Aorta
The main artery leaving the left ventricle. It leads into the systemic arteries that distribute blood around the body. East London NHS Foundation Trust: Physical Health Training — cardiovascular system
Valves
Help keep blood moving in the intended direction. This overview label represents the heart valves. Separate valve labels require anatomically correct selectable structures. University Hospitals Bristol NHS-hosted resource: Understanding the circulatory system — patient/family information
Body capillaries
Small vessels allow exchange with body tissues. Oxygen and nutrients reach tissues and wastes return to the blood before the venous return journey. University Hospitals Bristol NHS-hosted resource: Understanding the circulatory system — patient/family information
Coronary arteries
Supply the heart muscle itself. Coronary arteries supply the heart muscle itself. Compare this route with blood passing through the chambers: chamber filling is not the same as supplying the myocardium. Keeping these routes distinct helps explain the location of coronary disease. The model identifies the normal supply and does not measure flow, diagnose narrowing or predict an individual’s symptoms. NHS: Coronary heart disease
Myocardium and rhythm
Heart muscle contracts in a coordinated rhythm to pump blood. Myocardium means heart muscle. The short activation cue is biological teaching content, not a live pulse or ECG. St George’s University Hospitals NHS Foundation Trust: Catheter Ablation for SVT — normal heart electrical system
Open the complete process transcript
The process, step by step
Return from the body
Begin at the right atrium, the upper chamber on the heart’s anatomical right side. In this front-facing view it appears on the viewer’s left. Veins return blood from the body towards this chamber, completing the body-circulation route before the journey to the lungs. Follow the direction indicated rather than identifying a vessel by its display colour. The selected label marks the chamber receiving that return; it does not represent a separate store of blood. Trace the connection slowly, then keep the chamber in mind for the next pumping step. East London NHS Foundation Trust: Physical Health Training — cardiovascular system · University Hospitals Bristol NHS-hosted resource: Understanding the circulatory system — patient/family information
What to watch: Find the right-atrium label on the viewer’s left, then identify the return route approaching the upper chamber.
Why it matters: Returning blood must remain connected to the next part of the circulation. Recognising this receiving chamber helps the learner follow one continuous loop rather than treating the lungs and body as disconnected routes.
Explore this step: Trace the return direction and name the receiving chamber before moving to the right-ventricle step.
Pump towards the lungs
Follow the route from the right atrium into the right ventricle, then towards the pulmonary artery. The ventricle is the lower pumping chamber on this side. The pulmonary artery takes blood away from the heart towards the lungs, where gas exchange takes place. Its name follows the direction of travel, even though this blood is relatively low in oxygen. Compare the chamber label with the outgoing vessel label and trace their connection. The route and colours explain the anatomy; they do not show a measured flow or pressure. East London NHS Foundation Trust: Physical Health Training — cardiovascular system
What to watch: Locate the right ventricle below the right atrium and trace the outgoing connection labelled pulmonary artery towards the lungs.
Why it matters: The lung circuit receives blood from the right ventricle. Understanding this connection also shows why “artery” means a vessel leading away from the heart, rather than simply a vessel containing oxygen-rich blood.
Explore this step: Follow the right-ventricle outlet and explain why its outgoing vessel is called an artery.
Exchange gases
At the lungs, air and blood are close together but remain in different spaces. Oxygen passes across thin boundaries from the air sacs into nearby blood, while carbon dioxide passes in the opposite direction towards the air that will be breathed out. Follow the lung-exchange label as the link between the incoming and returning parts of the lung circuit. Air does not travel directly along an open blood vessel. Use the model to explain the direction of exchange; the simplified view does not measure gas levels or a person’s breathing. Frimley Health NHS Foundation Trust: How your lungs work
What to watch: Locate the lung-exchange label between the route arriving from the right heart and the route returning towards the left heart.
Why it matters: Gas exchange connects breathing with the transport work of the circulation. The blood can then carry oxygen onwards; the picture identifies that connection without measuring oxygen delivery or diagnosing a breathing problem.
Explore this step: Explain which gas moves towards the blood and which moves towards the air, keeping the two spaces distinct.
Return from the lungs
Trace the pulmonary veins from the lungs to the left atrium. The blood returning along this route is now relatively rich in oxygen after lung gas exchange. The left atrium is the upper receiving chamber on the heart’s anatomical left side, shown on the viewer’s right in this view. Notice that these oxygen-rich vessels are still called veins: their direction is towards the heart. Compare this return with the body veins in the first step, using direction and connection rather than display colour to identify each route. East London NHS Foundation Trust: Physical Health Training — cardiovascular system
What to watch: Follow the pulmonary-vein labels from the lung return towards the left atrium on the viewer’s right side of the heart.
Why it matters: This connection brings blood back after gas exchange, ready for the next pumping step. Comparing both venous returns reinforces that a vein is defined by movement towards the heart, not by oxygen content.
Explore this step: Compare the pulmonary veins with the body’s returning veins and state the directional feature they share.
Pump towards the body
From the left atrium, follow the connection into the left ventricle and then through its outlet towards the aorta. The left ventricle is the lower chamber that pumps blood into the body circuit. The aorta leads into branching arteries that distribute blood to the body’s tissues. Locate the chamber, outlet and large vessel in that order rather than jumping directly to the whole-body view. These labels describe connected structures and the direction of pumping; the model is not measuring the strength of contraction or the amount of blood delivered. East London NHS Foundation Trust: Physical Health Training — cardiovascular system
What to watch: Locate the left ventricle, its outlet and the aorta, then follow the route towards the body circulation.
Why it matters: The body circuit carries blood onwards from the heart to the tissues. Seeing the chamber and its outlet together connects the pumping action with distribution rather than treating the aorta as an isolated structure.
Explore this step: Trace from the left ventricle to the aorta, then identify where the body-circulation view continues the route.
Exchange and return
In the body’s capillary networks, blood and tissues exchange substances across thin vessel walls. Oxygen and nutrients move towards the tissues, while waste products, including carbon dioxide, move towards the blood for transport away. The vessels then join the returning venous route and bring blood back towards the right atrium. Follow the capillary label and then return to the first chamber label to complete the loop. The enlarged network is a teaching view, not a to-scale picture of every vessel or a measurement of exchange in an individual. University Hospitals Bristol NHS-hosted resource: Understanding the circulatory system — patient/family information
What to watch: Find the body-capillary network and follow its connection towards the returning vein route and the right-atrium label.
Why it matters: Exchange allows transported substances to reach or leave tissues. The return journey is equally necessary to the explanation: blood remains in a connected circulation rather than being used up at the end of an artery.
Explore this step: Trace a complete route from the body capillaries back to the first step, naming the return direction.
Supply the pump itself
Switch to the coronary-supply view and locate the vessels supplying the heart muscle itself. The myocardium is muscle that needs its own blood supply; blood filling a heart chamber is not simply soaking through the wall to feed it. Compare the coronary route with the large chamber-and-vessel loop you have just followed. This distinction helps explain why a problem in a coronary artery concerns supply to the pump’s own tissue. The separate activation cue introduces coordinated function; it is not an ECG, a live pulse or a diagnostic heart-rhythm display. NHS: Coronary heart disease · St George’s University Hospitals NHS Foundation Trust: Catheter Ablation for SVT — normal heart electrical system
What to watch: Locate the coronary-artery labels alongside the myocardium label, comparing this supply with the route through the heart’s chambers.
Why it matters: The heart muscle also depends on a blood supply. Distinguishing coronary supply from chamber filling makes it possible to discuss coronary disease without suggesting that every cardiovascular problem has the same mechanism.
Explore this step: Compare the coronary and chamber views and explain the different function of the route highlighted in each.
Read the practice situations and all answer explanations
Sources and how the model is made
The opening images are AI-generated anatomical illustrations. The interactive 3D models and labelled SVG diagrams use original procedural artwork. These teaching images are not medical scans or diagnostic tools. Source references support the learner explanations and do not grant artwork rights.
- East London NHS Foundation Trust: Physical Health Training — cardiovascular system — Page 44: chamber connections, pulmonary artery/veins and aorta. Replaces non-NHS anatomy links. No training slides or artwork copied.
- NHS: Coronary heart disease — Separate coronary supply, wall deposits, narrowed supply, variable or absent symptoms. No diagnosis or copied video.
- University Hospitals Bristol NHS-hosted resource: Understanding the circulatory system — patient/family information — Printed pages 36–38: artery/vein direction, capillary exchange, chambers and valves. Resource produced by Heart Research UK; normal anatomy only, no congenital-heart exercise advice or artwork reused.
- NHS: Heart attack — Reviewed 31 March 2026: emergency symptoms, 999, rest/monitoring, clot mechanism and distinction from arrest. No medicine branch.
- NHS 111 Wales: Cardiac Arrest — Unresponsive/abnormal breathing, gasping, immediate 999/CPR/call-handler/AED recognition. Replaces non-NHS emergency link, not a complete practical course.
- Frimley Health NHS Foundation Trust: How your lungs work — Alveolar/capillary gas exchange, oxygen and carbon dioxide. Previously verified for respiratory module; no artwork copied.
- St George’s University Hospitals NHS Foundation Trust: Catheter Ablation for SVT — normal heart electrical system — Page 2 normal coordinated cardiac activation and pumping. Printed review October 2026 requires recheck. No ECG/treatment instruction or credited artwork reused.
- Leeds Teaching Hospitals NHS Trust: Understanding coronary angiography and coronary intervention — One common plaque-disruption and clot mechanism affecting coronary supply. No procedures, treatment regimens or symptom-duration waiting rule transferred.
- NHS: Coronary heart disease — prevention — General activity, diet and smoking-support context, alongside prescribed care; no personal target or guarantee.
- NHS: Cardiovascular disease — CVD is a broad group; the coronary example is not presented as every CVD mechanism.
Which work factors should be assessed alongside cardiovascular health?
Carbon monoxide and heat can create immediate physiological hazards. Poor recovery, shift patterns, fatigue and work-related stress are separate health and safety risks that also need control.
Some contributors act quickly. Carbon monoxide from combustion equipment in enclosed or poorly ventilated spaces can bind to haemoglobin and reduce oxygen delivery. A worker with existing coronary disease may be especially vulnerable because the heart already has reduced reserve.
Other contributors act over time. Long hours and shift patterns can reduce sleep, disrupt circadian rhythm, alter eating patterns and reduce recovery. High demands, low control, poor support, bullying or poorly managed change can create sustained stress responses.
Exposure does not automatically mean disease. Dose, duration, frequency, worker vulnerability, task intensity, recovery time, control quality and early action all influence whether harm develops.
| Contributor | How it may affect health or safe work | Common workplace examples |
|---|---|---|
| Carbon monoxide | Reduces oxygen delivery and can trigger heart and brain effects. | Petrol generators, cut-off saws, LPG heaters, engines in enclosed areas. |
| Long working hours | Reduces recovery and can cause fatigue and ill health; assess the actual pattern rather than assuming a safe number of hours. | Persistent overtime, understaffing, on-call and project crunch. |
| Shift and night work | Disrupts sleep, circadian rhythm, meals and recovery. | Transport, healthcare, utilities, security, manufacturing and process work. |
| Work-related stress | Sustained stress may affect health and behaviour; individual cardiovascular causation needs clinical assessment. | High demands, low control, poor support and conflict. |
| Fatigue | Reduces performance and may encourage unhealthy coping patterns. | Long shifts, quick returns and insufficient rest. |
| Heat strain | Increases cardiovascular load and can worsen existing vulnerability. | Hot process work, outdoor heat, PPE-heavy work and confined spaces. |
How can work affect the heart and circulation?
Different work exposures act through different pathways; identifying the pathway determines the control.
Carbon monoxide from a petrol engine or faulty combustion appliance binds to haemoglobin and reduces oxygen delivery. An enclosed loading bay or basement can become dangerous quickly. Headache, dizziness, weakness or confusion in several people at once is an exposure warning; a worker with chest pain, severe breathlessness or collapse needs emergency help. Stop the source, move people to fresh air if safe, and call 999 for severe symptoms.
Repeated long hours, insufficient recovery and demanding shifts can cause fatigue and ill health and can undermine safe decisions. Work-related stress can also affect health and performance. These effects do not diagnose an individual or prove that a particular roster caused a particular event; they do justify assessing work design, staffing and breaks. Heat and strenuous tasks can add an acute load, particularly where a worker has an existing condition.
On a small screen, scroll this table sideways to read all columns.
| Work situation and route | Potential effect | Control and decision |
|---|---|---|
| Petrol generator in a closed service room; CO is inhaled. | Oxygen delivery falls; acute poisoning, cardiac strain and collapse are possible. | Stop engine, evacuate, use trained response and prevent indoor combustion. |
| Repeated long shifts and inadequate rest. | Fatigue and ill health can develop, and reduced alertness can impair safe work. | Redesign staffing and recovery; review actual hours, including overtime. |
| High demands with little control or support. | Sustained stress response can affect health and performance. | Use HSE/HSENI stress risk assessment, consultation and action on the work factors. |
| Hot, physically demanding work with limited breaks. | Circulatory demand rises; an individual may need a safe-work review. | Change work, cooling and recovery; seek clinical/OH advice for individual restrictions. |
Which warning signs need urgent action?
Call 999 for suspected heart attack or stroke; do not wait for a manager or occupational-health appointment.
Heart attack may cause central chest pressure or pain that spreads to the arm, jaw, neck or back, often with breathlessness, sweating or nausea. Stroke signs include a drooping face, arm weakness and speech difficulty; the FAST reminder means Face, Arms, Speech, Time to call 999. Symptoms can vary. Collapse, severe breathing difficulty or sudden confusion also needs urgent assessment. Do not ask the person to drive themselves.
If several people in a combustion area develop headache, dizziness, weakness or confusion, suspect carbon monoxide as well as a medical problem. Move out to fresh air if safe, stop the source only within the emergency plan, call for help, and keep others from entering. Record the environment and work task after care is under way. An ordinary symptom discussion cannot establish a cardiovascular diagnosis or work causation.
Which work situations need closer cardiovascular and safety assessment?
Prioritise toxic exposure, heat, fatigue and safety-critical tasks, especially where an existing cardiovascular condition may affect safe work.
Several work hazards can occur together: a long shift, hot environment, heavy PPE, poor hydration, overtime, night work and safety-critical decisions. Assess each hazard and the worker’s functional needs; do not infer a cardiovascular diagnosis from the work pattern.
Carbon monoxide risk is highest with petrol or LPG equipment in enclosed or partly enclosed areas. Construction, refurbishment, tunnels, basements, plant rooms, garages, workshops and welfare units can all become dangerous if combustion gases build up.
Safety-critical roles need careful assessment because sudden incapacity or impaired concentration can affect others. This includes driving, plant operation, lone work, confined spaces, working at height, process control and emergency response.
| Situation | Why assessment matters | Control focus |
|---|---|---|
| Combustion equipment indoors | Carbon monoxide can build up quickly. | Eliminate, ventilate, detect and train. |
| Long or repeated overtime | Recovery is reduced over weeks or months. | Set working-time limits and staffing controls. |
| Night and rotating shifts | Sleep and circadian rhythm are disrupted. | Design shifts and rest periods. |
| Hot work environments | Cardiovascular load increases. | Heat risk assessment and rest cycles. |
| High-demand low-control work | Psychosocial strain increases. | Redesign work using Management Standards. |
| Safety-critical work | Sudden symptoms may harm the worker and others. | OH advice and fitness controls. |
How can the hierarchy of controls reduce workplace exposures linked to cardiovascular harm?
Prevent toxic exposures and redesign excessive demands and poor recovery before relying on personal wellbeing advice.
For carbon monoxide, eliminate petrol-powered equipment in enclosed spaces where practicable, prevent vehicle exhaust accumulation, maintain combustion plant and verify ventilation and detection as applicable. For hours and shifts, inspect actual rosters, overtime, breaks and recovery rather than a written policy. For stress, consult workers about demands, control, support, relationships, role and change, then correct the work factors found. Personal health advice may help a worker, but it cannot make an uncontrolled atmosphere or unsafe roster acceptable.
The eliminate, reduce, isolate, control, personal protective equipment and discipline (ERICPD) prompt can organise exposure controls, but it is not a statute or a complete solution to work design. For CO, source removal and engineering control dominate; PPE is not a routine answer to an unknown atmosphere. For fatigue and stress, redesign and staffing are often stronger than training in resilience. Stop the affected task when an exposure control fails, multiple people become unwell, or fatigue makes safety-critical work unsafe.
On a small screen, scroll this table sideways to read all columns.
| Factor and owner | Control and evidence | Hold or review point |
|---|---|---|
| CO — process/plant manager | Remove indoor combustion, maintain plant and ventilation; inspect actual task and monitoring. | Stop and evacuate on suspected release or symptoms. |
| Hours and shifts — operations manager | Set a roster with adequate recovery; compare planned with actual overtime and worker feedback. | Hold safety-critical assignment if fatigue cannot be controlled. |
| Stress — manager and workers | Use a work-related stress assessment and agreed changes to demand, control or support. | Review persistent complaints, absence patterns or failed actions. |
| Individual support — manager/OH | Use functional restrictions and reviewable adjustments, with minimum health information. | Seek competent advice if fitness or emergency response is uncertain. |
How can the ERICPD hierarchy of controls reduce workplace exposures linked to cardiovascular harm?

| ERICPD control level | Topic-specific example | Source and full task context |
|---|---|---|
| Eliminate | Remove indoor petrol-powered equipment where practicable. | Read the full task example, checks and stop points on this page. |
| Reduce | Redesign excessive hours and demands to reduce work exposure. | Read the full task example, checks and stop points on this page. |
| Isolate | Use suitable ventilation and source separation for toxic exposure. | Read the full task example, checks and stop points on this page. |
| Control | Verify rosters, recovery, exposure controls and support routes. | Read the full task example, checks and stop points on this page. |
| PPE | PPE is not a routine answer to an unknown CO atmosphere. | Read the full task example, checks and stop points on this page. |
| Discipline | Maintain plant, check actual work and stop on failed controls. | Read the full task example, checks and stop points on this page. |
How can the ISO 45001 hierarchy of controls reduce workplace exposures linked to cardiovascular harm?

| ISO 45001 / ESEAP control level | Topic-specific example | Source and full task context |
|---|---|---|
| Eliminate | Remove indoor petrol-powered equipment where practicable. | Read the full task example, checks and stop points on this page. |
| Reduce | Redesign excessive hours and demands to reduce work exposure. | Read the full task example, checks and stop points on this page. |
| Isolate | Use suitable ventilation and source separation for toxic exposure. | Read the full task example, checks and stop points on this page. |
| Control | Verify rosters, recovery, exposure controls and support routes. | Read the full task example, checks and stop points on this page. |
| PPE | PPE is not a routine answer to an unknown CO atmosphere. | Read the full task example, checks and stop points on this page. |
| Discipline | Maintain plant, check actual work and stop on failed controls. | Read the full task example, checks and stop points on this page. |
What should be monitored for occupational cardiovascular risk?
Monitoring should cover exposure, work design, fatigue, stress indicators, safe-work decisions and action close-out.
Monitoring should combine leading and lagging indicators. Leading indicators include CO detector checks, shift pattern review, overtime, rest breaks, workload, stress risk assessments, maintenance records and worker feedback. Lagging indicators include incidents, symptoms, sickness absence, fatigue reports and occupational health referrals.
For carbon monoxide, monitoring may include exposure assessment, ventilation inspection, detector checks and equipment maintenance. Diesel exhaust needs its own separate hazardous-substance assessment and controls. For fatigue and shift work, the organisation should examine roster design, commute risk, quick returns, overtime and whether staffing levels create routine overload.
Monitoring is only useful if someone acts on it. Findings should have ranked actions, owners, deadlines and verification that the change worked.
| Indicator | What it shows | Action if poor |
|---|---|---|
| CO detector checks | Whether detection safeguards are available and maintained. | Repair, recalibrate or stop affected work. |
| Working hours | Whether long hours or overtime are routine. | Resource, redesign or cap hours. |
| Shift pattern review | Whether recovery and night-work controls are adequate. | Redesign rota and review commute risk. |
| Stress risk assessment | Whether demands, control, support, role, relationships and change are managed. | Action plan and worker consultation. |
| Worker symptoms | Potential exposure or overload pattern. | Investigate and refer if needed. |
| OH referrals | Work impact and fitness themes. | Use anonymised trends for improvement. |
What occupational health and health surveillance arrangements may be needed?
Occupational health input may be needed where cardiovascular health interacts with exposure, safety-critical work, shift work, fatigue or return to work.
Health surveillance is not a universal requirement for all cardiovascular risk. It depends on the risk assessment, exposure type, legal requirements and competent occupational health advice. For some exposures, such as carbon monoxide or hazardous substances, the main control is preventing exposure; health review may support early detection or safe-work decisions.
Occupational health is particularly useful when a worker has a known heart condition, returns after a heart event, reports symptoms linked to work, struggles with night work, or performs safety-critical duties. The referral should ask functional questions: what work can the person do, what restrictions are advised, what adjustments are needed and when should review happen.
Confidentiality matters. Managers need enough information to manage work safely, but they do not need unnecessary clinical detail.
| Situation | Possible OH question | Management output |
|---|---|---|
| Return after cardiac event | What duties, hours or exertion limits are advised? | Return-to-work plan. |
| Safety-critical work | Is the worker fit for driving, plant or lone work? | Fitness decision and review date. |
| CO exposure symptoms | Could symptoms relate to workplace exposure? | Exposure review and medical assessment route. |
| Night-work difficulty | Are shift adjustments needed? | Rota or role adjustment. |
| Heat strain vulnerability | What controls or restrictions are needed? | Heat work plan. |
| Stress-related health impact | What workplace adjustments may reduce harm? | Stress action plan. |
How should an individual safe-work decision be made?
Assess the task and functional demands with the worker, seek clinical or occupational-health advice when needed, and agree a reviewable plan.
A diagnosis alone does not tell a manager whether someone can drive, work at height, enter a hot area or cover a lone shift. Start with the actual task, exposure, emergency access and what the person says they can do. Occupational health can translate clinical information into functional advice within consent and confidentiality boundaries; the manager then controls the work and records only necessary restrictions or adjustments.
For example, after a cardiovascular event, a technician may return to a day-shift desk role while strenuous or lone call-outs remain on hold pending competent advice. The manager arranges cover, agrees a review date and checks that the worker is not exposed to uncontrolled CO, heat or fatigue. If symptoms recur or the task changes, pause the affected duty and revisit the decision rather than treating a past fit note as permanent clearance.
Which duties apply in Great Britain and Northern Ireland?
Use the statutory instrument and regulator for the work location, and separate law from guidance.
General risk assessment, hazardous-substance control and working-time requirements depend on the location and the factor being controlled. The GB Health and Safety at Work etc. Act 1974, Management Regulations 1999, COSHH 2002 and Working Time Regulations 1998 are distinct from the Northern Ireland 1978 Order, Management Regulations 2000, COSHH Regulations 2003 and Working Time Regulations (Northern Ireland) 2016. Do not treat a cardiovascular diagnosis as automatic evidence of an occupational cause or a reportable disease.
On a small screen, scroll this table sideways to read all columns.
| Decision | Great Britain | Northern Ireland |
|---|---|---|
| Assess and control work risk | GB health and safety Act and Management Regulations; use HSE stress/fatigue guidance. | NI 1978 Order and Management Regulations 2000; use HSENI stress guidance. |
| Control a toxic exposure | GB COSHH 2002 and task-specific controls for CO. | NI COSHH Regulations 2003 and HSENI route. |
| Plan hours and night work | GB Working Time Regulations 1998; assess fatigue beyond minimum compliance. | Working Time Regulations (Northern Ireland) 2016; HSENI describes its enforcement remit. |
| Support a worker privately | GB equality route with Acas guidance; UK data-protection principles. | NI disability/employment route requires local advice; UK data-protection principles still apply. |
How should occupational cardiovascular risk be recorded?
Occupational cardiovascular risk should be recorded as controllable work factors, not as a list of workers' private medical conditions.
The risk register should describe the work source: carbon monoxide from equipment, fatigue from shift design, stress from demands and control, heat from process work or overtime from resourcing gaps. Record diesel exhaust separately under its own hazardous-substance controls. Individual diagnoses belong in confidential HR/OH records.
A strong register links each hazard to controls, evidence and review triggers. It should also show how concerns are escalated when symptoms, incidents, sickness trends or exposure monitoring suggest controls are failing.
| Risk area | What to record | Example evidence |
|---|---|---|
| Carbon monoxide | Source, location, tasks, detector and ventilation controls. | COSHH assessment and detector checks. |
| Shift work | Night work, rotation, rest breaks and quick returns. | Rota review and fatigue assessment. |
| Long hours | Overtime, on-call, workload and recovery. | Working-time report. |
| Stress | Demands, control, support, relationships, role and change. | HSE Management Standards action plan. |
| Heat | Hot tasks, PPE, workload and vulnerable workers. | Heat stress assessment. |
| Safety-critical roles | Fitness process and temporary restrictions. | OH referral and review records. |
How could Crownway Fuels Ltd manage occupational cardiovascular risk?

Crownway Fuels Ltd would manage occupational cardiovascular risk through exposure control, fatigue management, stress risk assessment, occupational health advice and safe-work review.
Crownway Fuels Ltd
a fuel storage, blending and distribution business with tank farms, drivers, loading operators, maintenance staff, control-room workers and 24-hour operations
Crownway treats cardiovascular risk as a work-design and exposure issue, not just a wellbeing campaign. Its cardiovascular work-factor review includes carbon monoxide from combustion equipment, shift work in the control room, long driving days, heat exposure during summer loading, emergency response demands and psychosocial risks during high-throughput periods. A separate hazardous-substance assessment covers diesel exhaust in loading areas.
The operations manager reviews rosters so night shifts, overtime and quick returns are visible. Tanker drivers have planned breaks and fatigue reporting. Portable generators are not used in enclosed areas, vehicle exhaust is controlled around workshops and loading bays, and CO detection is maintained where combustion risk remains.
Crownway uses three assurance levels. Frontline checks are simple: detectors working, ventilation on, breaks taken, symptoms reported, no engines idling indoors. Second-line checks by supervisors and H&S review rosters, maintenance records, stress actions and exposure controls. Third-line audits test whether the system works through sampling, interviews, record review and observations.
Where a worker has a cardiovascular condition or returns after a cardiac event, HR and occupational health focus on function: driving restrictions, shift tolerance, exertion, heat, lone work and review dates. The worker's medical information is restricted, while managers receive only the work controls needed to keep the person and others safe.
| Activity | How Crownway manages it | Evidence |
|---|---|---|
| Assess | Identifies CO, exhaust, shift, fatigue, heat, stress and safety-critical work risks. | Risk register and role-risk mapping. |
| Analyse | Reviews exposure data, rosters, overtime, absence, symptoms and worker feedback. | Monthly health-risk dashboard. |
| Train | Trains drivers, operators, supervisors and managers on symptoms, fatigue, CO and escalation. | Training matrix and briefings. |
| Implement | Uses ventilation, CO detectors, working-time controls, fatigue reporting and stress action plans. | Inspection records and rota controls. |
| Check | Uses frontline checks, supervisor audits and independent review of high-risk arrangements. | Assurance records and actions. |
| Learn | Investigates symptoms, fatigue events, high overtime and detector alarms. | Incident learning and action tracker. |
| Improve | Updates rosters, equipment standards, OH referral prompts and contractor rules. | Management review and revised standards. |
What should each role learn and demonstrate?
Learning must match the decisions people make, from recognising danger to checking that controls work.
Briefings should tell people how to act, but attendance alone does not show competence. Assess the real decision or task, record who assessed it and revisit after a material change, failed control or incident. A local authorisation is task-specific; no universal external certificate is implied.
On a small screen, scroll this table sideways to read all columns.
| Role and learning | Demonstration and assessor | Record and reassessment trigger |
|---|---|---|
| All staff: emergency signs, CO warning pattern and fatigue report. | Supervisor tests a scenario: call 999 for FAST or heart attack, leave suspected CO area, report fatigue. | Scenario outcome; update after local response or source change. |
| Exposed operator/maintainer: combustion controls and safe stop. | Technical assessor observes plant setup, ventilation/monitoring checks, defect isolation and no unsafe rescue. | Task authorisation; reassess after equipment or work-location change. |
| Supervisor: rosters, stressors, cover and immediate hold. | Operations assessor reviews real overtime and a distressed or unwell worker case; records a safe staffing decision. | Roster review and action; repeat after a failed control or changed demand. |
| Manager/HR: confidential support and work redesign. | HR/OH assessor reviews a functional adjustment plan with restricted data and a review date. | Private support action; revisit after capacity or task change. |
| Safety/OH specialist or auditor: evidence and boundaries. | Competent peer challenges CO exposure, fatigue data, stress assessment, GB/NI law and clinical inference. | Traceable judgement and corrective action; review on new evidence. |
How does occupational cardiovascular disease support qualification study and professional development?
Occupational cardiovascular disease helps learners connect hazardous substances, fatigue, stress, work design, occupational health and safe-work decisions.
For NEBOSH National General Certificate study, this topic can appear through occupational health, stress, fatigue, hazardous substances, emergency arrangements and worker consultation. A strong answer identifies the work factor and then explains the control route.
For Diploma study, the topic supports deeper analysis of epidemiology, psychosocial risk, long-latency and chronic disease, exposure assessment, fitness for work, surveillance and management-system assurance.
A scenario-based answer should avoid saying 'tell workers to be healthier' as the main control. The better answer looks at work hours, shift design, CO sources, ventilation, stressors, heat, safety-critical tasks and occupational health input.
How can a management system sustain effective decisions?
Give each hazard or support route an owner, a control, a check and a response to failure.
Operations should bring together actual hours, worker consultation, stress assessment, exposure checks, incident data and functional support without putting a person’s diagnosis in the general risk register. An owner should sample actual work and corrective actions, not accept a policy or certificate as evidence that the controls work.
The free GB regulator guide HSE Managing for health and safety (HSG65) explains a plan–do–check–act approach: assign controls and owners, involve workers, check work as done, and correct failures. For Northern Ireland, use HSENI risk assessment guidance for the local duty. A certificate alone does not demonstrate that a control works.
What are the warning signs that occupational cardiovascular risk is not managed?
Warning signs include routine long hours, unmanaged stress, weak shift design, CO symptoms, poor exposure control and unsafe return-to-work decisions.
Poor management often shows as normalised overload: excessive overtime, cancelled breaks, night shifts with poor recovery, workers driving home exhausted, or managers treating fatigue as commitment. Over time that can contribute to ill health and immediate safety risk.
Exposure-related warning signs are more acute. Headaches around combustion equipment, symptoms affecting several workers, CO alarms, exhaust fumes indoors or diesel smoke in enclosed areas require immediate review.
Individual support warning signs include managers asking for unnecessary medical details, ignoring fit-note advice, allowing unsafe duties without review, or leaving restrictions open-ended without occupational health input.
Occupational cardiovascular disease FAQs: what do people ask?
People usually ask whether work can affect heart health, how to manage carbon monoxide, fatigue, shift work, stress and safe return to work.
What is occupational cardiovascular disease?
It covers acute work exposures that may strain the heart or circulation and safe-work decisions for workers with cardiovascular conditions; wider work-design hazards need their own controls.
Can carbon monoxide affect the heart?
Yes. Carbon monoxide reduces oxygen delivery and can cause serious cardiovascular and neurological harm.
Why assess long working hours?
Long hours without enough rest can cause fatigue and ill health. Review the shift pattern, overtime and recovery time; seek clinical advice for an individual cardiovascular concern.
How can shift work affect health and safe work?
Shift work can disrupt sleep and body clock rhythms and contribute to fatigue. Assess shift design and recovery without inferring an individual cardiovascular diagnosis.
How should work stress be managed when heart health is a concern?
Assess and control work-related stressors. A person’s cardiovascular symptoms or diagnosis need clinical assessment; the stress assessment does not establish their cause.
What symptoms should managers not ignore?
Chest pain, severe breathlessness, collapse, confusion, suspected stroke symptoms or symptoms linked to carbon monoxide exposure need immediate escalation.
Should managers ask workers about heart diagnoses?
Managers should focus on work impact and safe support, not unnecessary medical details.
When should occupational health be involved?
Occupational health is useful where cardiovascular health may affect safety-critical work, shift work, driving, return to work or exposure vulnerability.
What controls reduce occupational cardiovascular risk?
Controls include eliminating carbon monoxide sources, managing fatigue, designing shifts well, controlling workload, reducing exhaust exposure and supporting healthier work.
Is health surveillance always required?
No. Health surveillance depends on the risk assessment, exposure type and occupational health advice.
How should risk registers record this topic?
Record work factors such as CO, shift work, long hours, stress, heat and exhaust exposure, not private diagnoses.
What is the difference between cardiovascular health and occupational cardiovascular disease?
Cardiovascular health covers general risk and care; this page focuses on acute work hazards, safe-work decisions and work-design risks that employers can control.
Which acronyms are useful for occupational cardiovascular disease?
Acronyms help readers follow heart-health, occupational health, exposure and work-design language.
| Acronym or term | Meaning | Why it matters |
|---|---|---|
| CVD | Cardiovascular Disease | General term for heart and circulatory disease. |
| CHD | Coronary Heart Disease | Disease affecting blood supply to the heart. |
| CO | Carbon Monoxide | Acute workplace toxic gas affecting oxygen delivery. |
| OH | Occupational Health | Work-focused health advice and fitness guidance. |
| COSHH | Control of Substances Hazardous to Health Regulations | Framework for CO, exhaust and hazardous substances. |
| DEEEs | Diesel Engine Exhaust Emissions | Vehicle or plant emissions requiring control. |
| WTR | Working Time Regulations | Framework relevant to hours, rest and night work. |
| EAP | Employee Assistance Programme | Confidential support route offered by some employers. |
| KPI | Key Performance Indicator | Used to monitor fatigue, stress and health-risk controls. |