SHARE Knowledge Hub
Mental ill-health and work-related stress
Work-related stress and mental ill-health can overlap, but the causes and support routes are not identical. Employers should identify harmful work demands and conditions, act on them and offer appropriate support without treating a worker's diagnosis as the whole risk assessment.
Owner: SHARE Knowledge Hub editorial team.
Change the demand rather than add another coping task
Conflicting priorities, interruption and insufficient capacity can create harmful work demands. Removing duplicate work and restoring support are measurable management actions.

Understand the work
Discuss actual demands, resources, control and support with affected workers and distinguish immediate safety needs.
Act on causes
Assign priorities, remove or defer work where appropriate and restore usable support rather than only offer individual coping advice.
Review outcomes
Check workload and function after the change while keeping individual clinical support in its confidential lane.
An action list or wellbeing survey does not itself demonstrate that stress risks are controlled.
How can I practise this topic in 3D?


An aggressive customer at the counter

An angry driver pressures the gate marshal

Fatigue, glare and poor welfare undermine a critical task
All related inspection points 7 across 4 locations
Garage workshop 3 inspection points
Construction site 2 inspection points
Crown Fuels terminal 1 inspection point
Warehouse walkabout 1 inspection point
Practice in the SHAREhub environment. Browser practice is separate from workplace competence and formal learning records.
How do mental ill-health and work-related stress connect?
Work-related stress and mental ill-health can overlap, but they are not the same thing; the cause, control route and support route must be understood separately.
Best-practice guide: Mental ill-health and work-related stress

How do mental ill-health and work-related stress connect?
Work-related stress and mental ill-health can overlap, but they are not the same thing; the cause, control route and support route must be understood separately. Work-related stress and mental ill-health can overlap, but the causes and support routes are not identical.
Turn mental ill-health and work-related stress knowledge into a decision
Work-related stress and mental ill-health can overlap, but the causes and support routes are not identical. Employers should identify harmful work demands and conditions, act on them and offer appropriate support without treating a worker's diagnosis as the whole risk assessment. Workload data, staffing review and prioritisation decision.
Team stress risk assessment example
Rising absence: Workload data, staffing review and prioritisation decision. More errors: Procedure fix, coaching and quiet processing time.
Where does management of mental ill-health and stress fail?
It fails when the organisation treats stress as an individual weakness, ignores work causes, breaches privacy or confuses support with prevention.
Choose controls for mental ill-health and work-related stress
Eliminate: Remove avoidable conflicting demands or unnecessary work steps through a supported redesign. Reduce: Compare a more manageable process, work allocation or suitable system replacing the identified stressful arrangement. Isolate: Improve suitable tools and work environment where they contribute to the assessed demand or difficulty. Control: Agree realistic workload, priorities, role clarity, staffing, consultation and support, with named owners. PPE: Maintain any task-specific residual protection where relevant. Read the full control table for qualifications, ownership and verification. Use the actual task and applicable jurisdiction; existing technical approval remains unchanged.
Use the full mental ill-health and work-related stress lesson
Use the full topic for the decision points, practical examples, detailed control tables and source scope. HSE guidance applies to Great Britain; use HSENI for the Northern Ireland route and the source’s stated jurisdiction. A simplified guide does not change the page’s technical-review or approval status.

Read all six steps as text
1. How do mental ill-health and work-related stress connect?
Work-related stress and mental ill-health can overlap, but they are not the same thing; the cause, control route and support route must be understood separately.
- Avoid / redesign: Remove avoidable conflicting demands or unnecessary work steps through a supported redesign.
- Control the task: Improve suitable tools and work environment where they contribute to the assessed demand or difficulty.
- Verify before release: Check the complete workflow and users affected.
Work-related stress and mental ill-health can overlap, but they are not the same thing; the cause, control route and support route must be understood separately. Work-related stress and mental ill-health can overlap, but the causes and support routes are not identical.
Apply it: Which part of this plan would you check at the workface before authorising the task?
2. Turn mental ill-health and work-related stress knowledge into a decision
Use the evidence to improve the actual work arrangement.
- Change at source: Remove avoidable conflicting demands or unnecessary work steps through a supported redesign.
- Make it observable: Check the complete workflow and users affected.
- Keep useful evidence: Workload data, staffing review and prioritisation decision.
Work-related stress and mental ill-health can overlap, but the causes and support routes are not identical. Employers should identify harmful work demands and conditions, act on them and offer appropriate support without treating a worker's diagnosis as the whole risk assessment. Workload data, staffing review and prioritisation decision.
Apply it: What evidence would show that the change improves this task, rather than only completing a record?
3. Team stress risk assessment example
Example: a practical application of the existing topic lesson.
- Rising absence: Workload data, staffing review and prioritisation decision.
- More errors: Procedure fix, coaching and quiet processing time.
- Conflict in meetings: Facilitated team discussion and manager follow-up.
Rising absence: Workload data, staffing review and prioritisation decision. More errors: Procedure fix, coaching and quiet processing time.
Apply it: At which point would you hold this example, and what evidence would allow it to proceed?
4. Where does management of mental ill-health and stress fail?
Connect the task, the route to the person and the control that can fail.
- Source / exposure: It fails when the organisation treats stress as an individual weakness, ignores work causes, breaches privacy or confuses support with prevention.
- Possible consequence: The common failure pattern is visible: workload rises, workers report pressure, managers offer awareness materials, absence increases, and the root causes remain.
- Control failure: Awareness and support are useful, but they do not control excessive demands, unclear roles, poor change or conflict.
It fails when the organisation treats stress as an individual weakness, ignores work causes, breaches privacy or confuses support with prevention.
Apply it: Who could be exposed, including other trades, cleaners, maintainers and people nearby?
5. Choose controls for mental ill-health and work-related stress
Start with the stronger practicable options and verify their effect.
- Eliminate: Remove avoidable conflicting demands or unnecessary work steps through a supported redesign.
- Reduce: Compare a more manageable process, work allocation or suitable system replacing the identified stressful arrangement.
- Isolate: Improve suitable tools and work environment where they contribute to the assessed demand or difficulty.
- Control: Agree realistic workload, priorities, role clarity, staffing, consultation and support, with named owners.
- PPE: Maintain any task-specific residual protection where relevant.
Eliminate: Remove avoidable conflicting demands or unnecessary work steps through a supported redesign. Reduce: Compare a more manageable process, work allocation or suitable system replacing the identified stressful arrangement. Isolate: Improve suitable tools and work environment where they contribute to the assessed demand or difficulty. Control: Agree realistic workload, priorities, role clarity, staffing, consultation and support, with named owners. PPE: Maintain any task-specific residual protection where relevant. Read the full control table for qualifications, ownership and verification. Use the actual task and applicable jurisdiction; existing technical approval remains unchanged.
Apply it: Which stronger option can be used here, and who will verify it before accepting the remaining risk?
6. Use the full mental ill-health and work-related stress lesson
Follow the official sources below and retain the task-specific evidence.
- Official guidance: HSE work-related stress and mental health
- Official guidance: HSE Management Standards overview
- Task decision: Workload data, staffing review and prioritisation decision.
Use the full topic for the decision points, practical examples, detailed control tables and source scope. HSE guidance applies to Great Britain; use HSENI for the Northern Ireland route and the source’s stated jurisdiction. A simplified guide does not change the page’s technical-review or approval status.
Apply it: Which official source and full-topic section will you use to resolve the next decision?
Work-related stress is the adverse reaction people have to excessive pressure or other types of demand placed on them at work. It is not itself a clinical diagnosis, but prolonged stress can contribute to physical and mental ill health, and can aggravate pre-existing conditions such as anxiety or depression. Sources: HSE work-related stress and mental health; HSE Management Standards overview
Mental ill-health can also arise from non-work causes such as bereavement, trauma, relationship breakdown, medical conditions, family history or a combination of factors. Work may still affect whether the person can stay well, recover, return safely or access support. Employers therefore have two related responsibilities: prevent and reduce work-related stressors, and support people whose mental health affects work. Sources: HSE work-related stress and mental health; HSE Management Standards overview
The practical mistake is to treat every mental health concern as a personal health matter, or every stress concern as a counselling issue. If workload, conflict, poor support, unclear roles or badly managed change are causing harm, the control is work design. If the person has a health condition, the response may also involve reasonable adjustments, occupational health, general practitioner (GP) support, employee assistance programme (EAP) and confidential employment-process support. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Issue | What it means | Workplace response |
|---|---|---|
| Work-related stress | Pressure, demand or work design has exceeded the person's ability to cope. | Assess and control work factors using a structured stress risk assessment.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Common mental health condition | A person may have anxiety, depression or another condition with work or non-work causes. | Discuss work impact, adjustments, support and privacy.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Stress aggravating a condition | Work stressors make an existing condition harder to manage. | Reduce stressors and consider occupational health (OH) or medical signposting.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Personal crisis affecting work | A non-work event affects attendance, concentration or safety. | Use compassionate support, privacy and task-risk review where needed.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Immediate risk or crisis | There may be risk of serious harm, self-harm or inability to stay safe. | Use emergency, crisis, first-aid or safeguarding route.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Safety-critical work concern | Fatigue, distress or medication may affect driving, plant, isolation or supervision. | Review task allocation and use competent advice where needed.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
How should the HSE Management Standards be used?
The Management Standards provide a practical structure for identifying and controlling the main work-design factors associated with work-related stress.
Health and Safety Executive (HSE)'s Management Standards cover six areas of work design: demands, control, support, relationships, role and change. They are not a questionnaire exercise on their own. They are a way to gather evidence, consult workers, identify underlying causes and agree practical improvements. Sources: HSE work-related stress and mental health; HSE Management Standards overview
A suitable stress risk assessment should use what the organisation already knows, such as absence data, workload pressure, overtime, turnover, grievances, violence reports, exit interviews, complaints, project delays and supervisor feedback. It should also involve workers and representatives because stressors are often hidden in work as done, not in the organisation chart. Sources: HSE work-related stress and mental health; HSE Management Standards overview
The standard of control is not met by telling workers to be resilient while leaving excessive workload, conflict, role ambiguity or poor change management untouched. Prevention comes from better work design, better management and proper resourcing. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Standard | What poor control looks like | Evidence of good control |
|---|---|---|
| Demands | Unmanageable workload, conflicting deadlines, sustained overtime or emotional overload. | Workload review, staffing decision, prioritisation and realistic deadlines.Sources: HSE Management Standards overview; HSENI work-related stress Management Standards. |
| Control | People have no say over pace, sequencing, breaks or how work is done. | Worker input, task planning, discretion where safe and escalation route.Sources: HSE Management Standards overview; HSENI work-related stress Management Standards. |
| Support | Supervisors are unavailable, resources are missing or people feel isolated. | One-to-ones, supervision, training, peer support and prompt issue resolution.Sources: HSE Management Standards overview; HSENI work-related stress Management Standards. |
| Relationships | Conflict, bullying, harassment, aggression or unmanaged friction. | Behaviour standards, early intervention, fair investigation and worker voice.Sources: HSE Management Standards overview; HSENI work-related stress Management Standards. |
| Role | People do not know what is expected or have conflicting responsibilities. | Clear roles, priorities, decision rights and handover.Sources: HSE Management Standards overview; HSENI work-related stress Management Standards. |
| Change | Change is announced late, poorly explained or unsupported. | Consultation, impact assessment, communication, training and review.Sources: HSE Management Standards overview; HSENI work-related stress Management Standards. |
How are stress prevention, individual support and emergency care separated?
Separate ongoing work prevention, individual support and immediate danger; an ordinary support conversation must not delay emergency assistance.
For workplace illness or injury, use the actual first-aid and emergency arrangements and obtain appropriate professional help. The NI government crisis page provides the NI route; verify current local clinical-service contacts for other nations through the competent service before putting them into an operational plan.
Following immediate help, management still needs to address work factors. A clinician handles clinical assessment and treatment; a manager assesses workload, role conflict or other work conditions. This lesson does not provide a nation-wide clinical triage algorithm.
Emergency, urgent care and routine support
If life is at risk or you cannot keep yourself or someone else safe, call 999 or go to A&E now. Do not wait for a manager, volunteer, HR, EAP or an AI answer. Stay with the person if safe.
Urgent help without immediate danger: England: NHS urgent mental health help — call 111 and select the mental health option or ask for an urgent GP appointment. Scotland: NHS inform urgent mental health help — contact your usual care team/GP or NHS 24 on 111 when urgent help cannot wait. Wales: NHS 111 Wales — call 111 and select option 2. Northern Ireland: crisis and urgent mental health support — use the care-plan contact, urgent GP/GP out-of-hours or Lifeline 0808 808 8000.
For a remote or lone worker, establish the current location, a callback method and how local responders gain access. The duty supervisor arranges safe work cover and a backup contact. Share only necessary information with appropriate responders; routine support follows once immediate safety is addressed. Service links checked 19 October 2026; confirm local arrangements and accessible contact methods.
How can the hierarchy of controls reduce harmful work demands and work-related stress?
Prevent the harmful work conditions first and verify the controls with workers. Support and clinical care have their own roles; neither replaces control of the work.


Six work-design factors organise a practical discussion with the team. The actions focus on workload, influence, resources, relationships, clear roles and managed change. Review the actual causes and whether changes improve the work.
Which change addresses the cause rather than relying only on resilience?
For example, reconcile demand with staffing capacity or resolve conflicting duties, then review the effect with the team.
Management review prompts, not a diagnostic test or a substitute for individual support.
Source guidance: HSE guidance
Illustrative decision: a service team reports excessive queue targets, conflicting priorities and repeated missed breaks. The manager assesses the work design with employees and representatives; a support volunteer cannot authorise the staffing solution.
ERICPD means Eliminate, Reduce (including substitution), Isolate, Control, PPE and Discipline. The five-level hierarchy groups measures as elimination, substitution, engineering controls, administrative controls and PPE. They overlap: isolation is usually an engineering measure; control can include engineered and administrative measures. Discipline means maintaining and checking the controls, supervising the method and learning from defects, rather than blaming someone or accepting weaker protection.
How can the ERICPD hierarchy of controls reduce harmful work demands and work-related stress?

| ERICPD and five-level position | Intervention and owner | Verification, failure and stop point |
|---|---|---|
| Eliminate / elimination | Remove avoidable conflicting demands or unnecessary work steps through a supported redesign. | Check the complete workflow and users affected. The person or their health is not the hazard to eliminate. |
| Reduce / substitution when replacing a hazard; otherwise engineering or administrative risk reduction | Compare a more manageable process, work allocation or suitable system replacing the identified stressful arrangement. | Confirm demand is reduced rather than shifted to another team; workers help test the actual workload. |
| Isolate / engineering | Improve suitable tools and work environment where they contribute to the assessed demand or difficulty. | Verify real usability and capacity. An improved system alone cannot resolve conflicting management priorities. |
| Control / administrative | Agree realistic workload, priorities, role clarity, staffing, consultation and support, with named owners. | Check work as done at peak demand. A resilience course or support referral is not closure of unresolved work-design risk. |
| PPE / PPE | Maintain any task-specific residual protection where relevant. | PPE is not a treatment for stress or a control for conflicting work priorities; this level may have no relevant intervention in the example. |
| Discipline / sustained engineering and administrative controls | Managers maintain actions, consult workers and review demand, control, support, relationships, role and change. | Retain implementation and outcome evidence. A favourable survey average or fewer referrals does not prove the barrier has been removed. |
How can the ISO 45001 hierarchy of controls reduce harmful work demands and work-related stress?

| ERICPD and five-level position | Intervention and owner | Verification, failure and stop point |
|---|---|---|
| Eliminate / elimination | Remove avoidable conflicting demands or unnecessary work steps through a supported redesign. | Check the complete workflow and users affected. The person or their health is not the hazard to eliminate. |
| Reduce / substitution when replacing a hazard; otherwise engineering or administrative risk reduction | Compare a more manageable process, work allocation or suitable system replacing the identified stressful arrangement. | Confirm demand is reduced rather than shifted to another team; workers help test the actual workload. |
| Isolate / engineering | Improve suitable tools and work environment where they contribute to the assessed demand or difficulty. | Verify real usability and capacity. An improved system alone cannot resolve conflicting management priorities. |
| Control / administrative | Agree realistic workload, priorities, role clarity, staffing, consultation and support, with named owners. | Check work as done at peak demand. A resilience course or support referral is not closure of unresolved work-design risk. |
| PPE / PPE | Maintain any task-specific residual protection where relevant. | PPE is not a treatment for stress or a control for conflicting work priorities; this level may have no relevant intervention in the example. |
| Discipline / sustained engineering and administrative controls | Managers maintain actions, consult workers and review demand, control, support, relationships, role and change. | Retain implementation and outcome evidence. A favourable survey average or fewer referrals does not prove the barrier has been removed. |
The comparison is an original illustrative application of the general HSE hierarchy, not a machine-specific method, permit or design approval. The employer must choose measures for the actual work and jurisdiction. Apply the separate Northern Ireland legal route where relevant; the local assessment and competent technical decision govern release.
What does a team stress risk assessment look like?
A good team stress risk assessment moves from symptoms and complaints to work causes, practical actions, ownership and review.
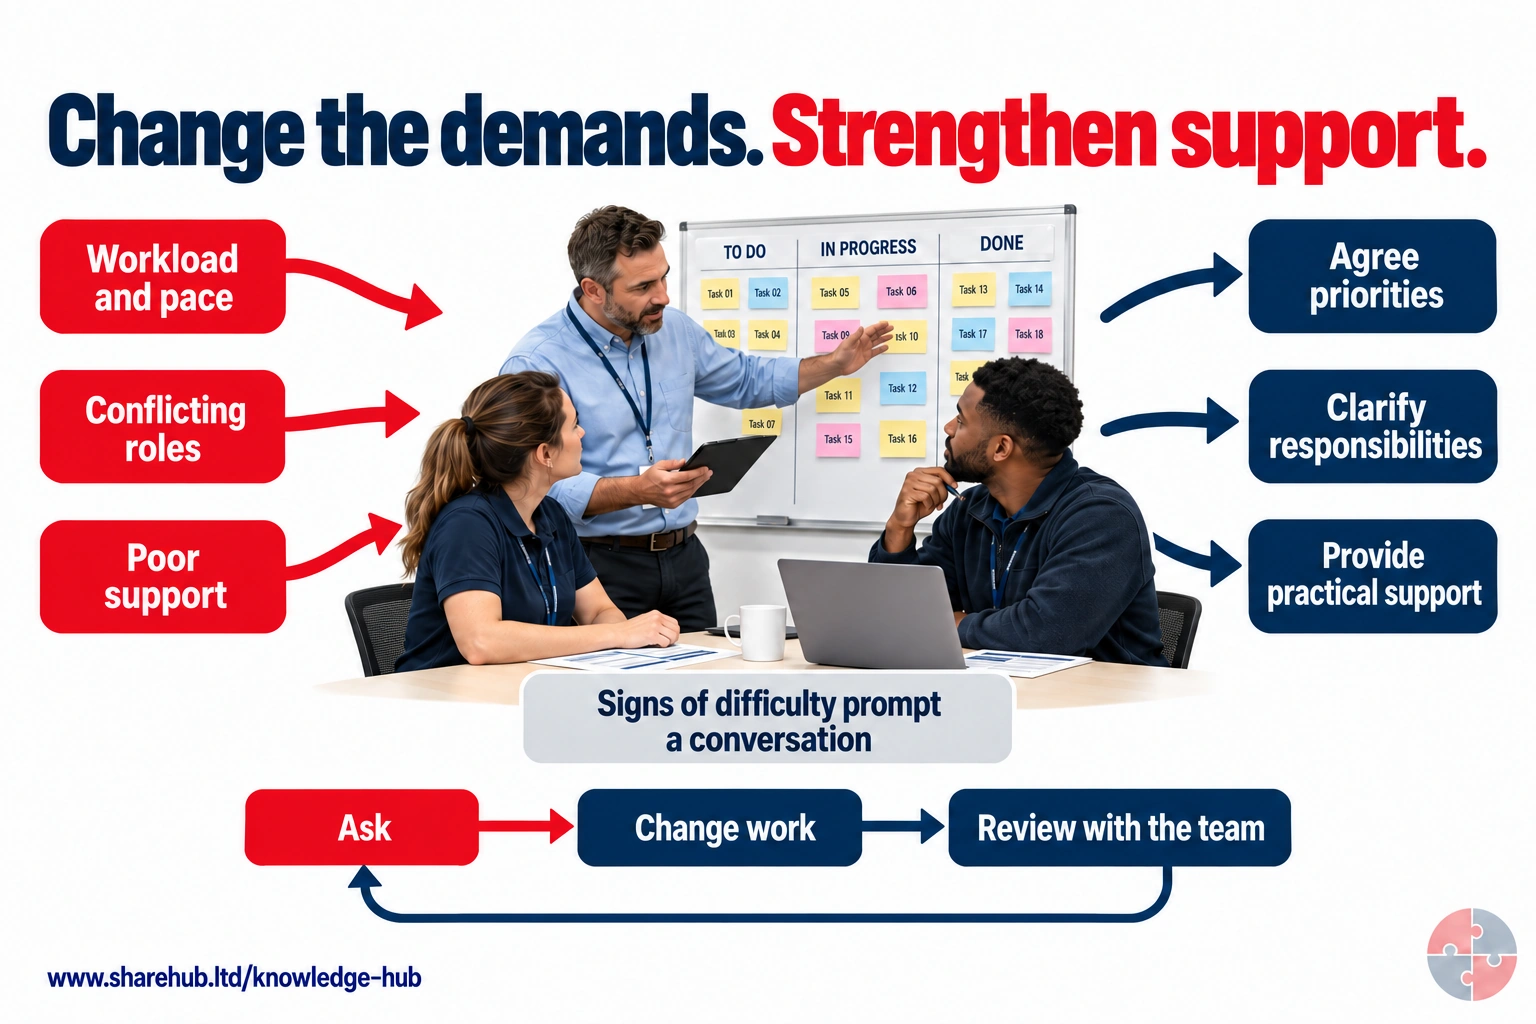
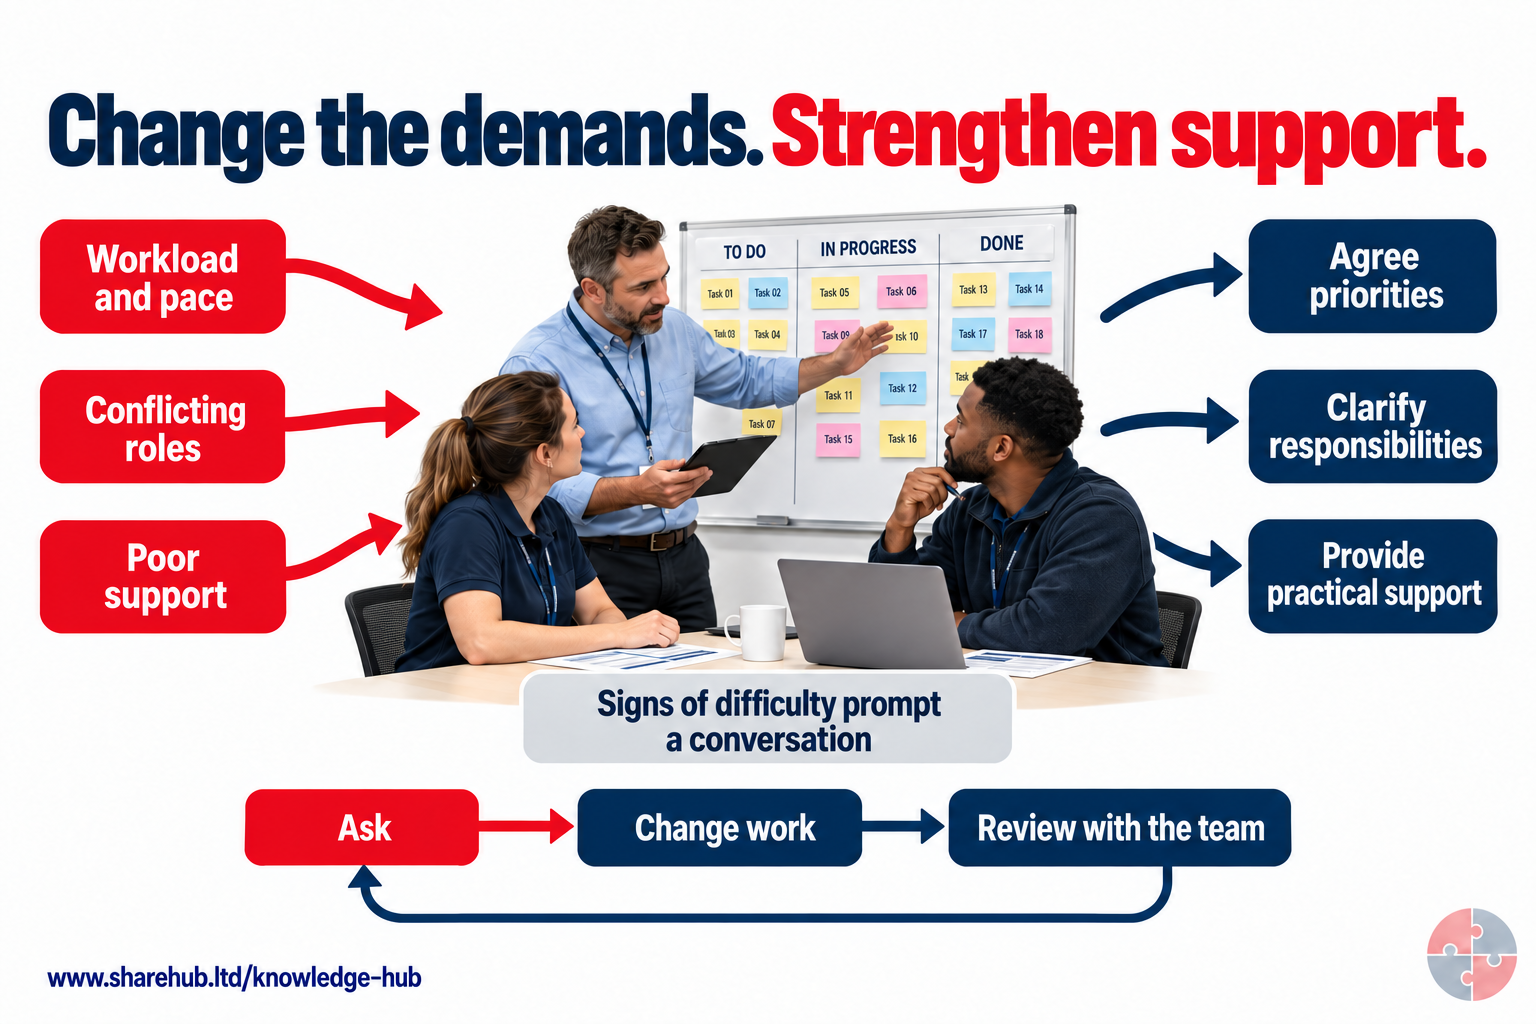
Workload, conflicting roles and poor support are illustrated as work factors to explore with the team. Agree workable priorities, clarify responsibilities and review practical support. Signs of difficulty prompt a conversation and assessment; they do not establish a diagnosis.
Which action changes the work rather than asking the individual to cope alone?
Agreeing achievable priorities, clarifying roles and providing resources or practical support can address the source of pressure.
This is a discussion example, not the complete HSE Management Standards assessment. Consider demands, control, support, relationships, role and change, alongside individual circumstances.
Source guidance: HSE HSG48 · HSE guidance
A customer-service team has rising absence, tense team meetings, more errors and two people asking to move department. The immediate workload has increased after a system change, but staffing has not changed. Supervisors are also handling more complaints from customers and have less time for coaching. Sources: HSE work-related stress and mental health; HSE Management Standards overview
A weak response is to offer a wellbeing webinar and ask individuals to manage their resilience. A stronger response is to examine demands, control, support, relationships, role and change: workload volumes, call complexity, staffing, system issues, break patterns, escalation rules, supervisor availability and conflict. Actions might include temporary triage, clearer escalation, extra supervision, workload caps, system fixes and review dates. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Finding | Underlying work issue | Action and evidence |
|---|---|---|
| Rising absence | Workload and emotional demand have increased after a system change. | Workload data, staffing review and prioritisation decision.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| More errors | Interruptions and unclear new procedure. | Procedure fix, coaching and quiet processing time.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Conflict in meetings | People disagree about priorities and feel unsupported. | Facilitated team discussion and manager follow-up.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Supervisor unavailable | Supervisors overloaded by complaints. | Escalation support and protected coaching time.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Worker anxiety | People fear blame for missed targets. | Revised targets and communication on safe escalation.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Review gap | No one knows whether actions worked. | Action owner, due date and repeat data review.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
Close one work-design action
Completed action: evidence — complex cases and queue demand have risen while breaks are missed; worker feedback confirms unclear priorities. The service manager authorises temporary priority limits and competent overflow cover before the next peak shift; review after that shift and again at the agreed date using demand, breaks, overtime/errors and worker feedback together. If resources exceed the owner’s authority, escalate and retain the restriction; check that pressure has not moved to another team.
How do stress prevention and mental health support differ?
Stress prevention controls work causes; mental health support helps the person manage work impact and access competent help where needed.
The two routes often run together. If a worker has anxiety and the team also has excessive workload, the manager should not choose one explanation and ignore the other. The team workload still needs assessment, and the individual may still need private support or adjustments. Sources: HSE work-related stress and mental health; HSE Management Standards overview
The strongest decisions separate the work control from the health-support route. Managers act on demands, support, conflict and change while OH, GP, EAP or human resources (HR) help where health advice, fitness or fair process is needed. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Route | Purpose | Typical evidence |
|---|---|---|
| Work-related stress risk assessment | Identify and reduce work stressors. | Management Standards assessment, action plan and worker consultation.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Mental health support | Help the person manage work impact and access support. | Private conversation, support route, adjustment and review date.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Reasonable adjustment review | Remove workplace barriers where a disability or health condition affects work. | Adjustment plan, OH/HR input and review.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Crisis response | Protect life and immediate safety. | Emergency, first-aid, safeguarding or crisis-route record.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Performance or conduct process | Address work standards fairly when relevant. | Facts, context, support offered and fair process.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
How should a manager start the conversation?
A useful conversation starts with observed work impact and support, not diagnosis.
Good wording is calm and specific: I have noticed you seem under a lot of pressure and have had to work late several times. Is there anything about the workload, support or current change that is making work harder? What would help in the short term while we review it? Sources: HSE work-related stress and mental health; HSE Management Standards overview
Poor wording puts the person on the defensive: Are you depressed? Are you coping? Everyone is busy. You need to be more resilient. That language shifts attention away from work design and may discourage disclosure. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Good wording | Poor wording | Why it matters |
|---|---|---|
| I have noticed the workload has changed and want to understand what is making work harder. | You seem stressed. | Focuses on work factors, not labels.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| What support or change would help you do the work safely? | What is wrong with you? | Keeps the boundary on work impact.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| We can review priorities and agree what can wait. | You need to manage your time better. | Tests whether demands are reasonable.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| I will only share what is needed to arrange support. | I will need to tell the team. | Protects confidentiality.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
Provide an alternative contact
Offer another manager, HR, a recognised representative or a trusted route when the line manager is the alleged source of harm or the worker does not wish to approach them. Keep task/work-design authority, employment process and clinical/OH advice distinct; an EAP signpost is not safety-critical authorisation. Statutory reasonable-adjustment duties depend on the actual GB/NI legal tests.
When should mental health or stress concerns be escalated?
Escalation is needed when there is immediate danger, serious deterioration, safety-critical impact, suspected work-related stress, bullying, violence, repeated absence or unresolved workload pressure.
Escalation does not always mean a formal HR process. It may mean a workload decision, OH referral, EAP signposting, stress risk assessment, safeguarding route, first aid, emergency services or senior resource decision. Sources: HSE work-related stress and mental health; HSE Management Standards overview
Managers should not wait for a formal diagnosis before acting on credible work-related stressors. If work is creating risk, the work should be reviewed. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Trigger | Immediate action | Follow-up |
|---|---|---|
| Immediate self-harm or suicide concern | Use emergency or crisis route and stay with the person if safe. | Record necessary facts and arrange support.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Stressors affect a team | Start Management Standards-style assessment. | Consult workers and track actions.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Safety-critical role affected | Review driving, plant, isolation, lone work or emergency role. | OH/HR input where needed.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Bullying, harassment or violence | Make safe, preserve facts and use policy route. | Review controls and support.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Repeated absence or distress | Hold private work-impact conversation. | Adjustment, OH or HR route.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Manager lacks authority to fix cause | Escalate resource or design issue. | Senior decision and evidence.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
Where does management of mental ill-health and stress fail?
It fails when the organisation treats stress as an individual weakness, ignores work causes, breaches privacy or confuses support with prevention.
The common failure pattern is visible: workload rises, workers report pressure, managers offer awareness materials, absence increases, and the root causes remain. Awareness and support are useful, but they do not control excessive demands, unclear roles, poor change or conflict. Sources: HSE work-related stress and mental health; HSE Management Standards overview
A second failure is intrusive handling of health information. Managers should not collect diagnosis details just because they are concerned. They should record work impact, support, actions, referral route and review date. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Failure or weak practice | How it develops | What good looks like |
|---|---|---|
| Resilience-only response | Stressors remain while workers are told to cope. | Assess demands, control, support, relationships, role and change.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| No worker consultation | Actions miss the real work pressure. | Involve workers and representatives.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Privacy breach | Health details shared informally. | Use data minimisation and need-to-know sharing.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| No owner for actions | Stress action plan becomes a list with no delivery. | Assign owners, due dates and review.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Safety-critical symptoms ignored | Distress or fatigue affects high-risk work. | Pause or review task allocation.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Support route unclear | Managers improvise in crisis. | Define crisis, OH, HR, EAP and emergency routes.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
What evidence shows mental ill-health and work-related stress is being managed?
Good evidence shows that controls are planned, used, checked, corrected and reviewed.
Evidence should be proportionate to risk. A low-risk wellbeing campaign may need simple review records, while higher-risk or safety-critical work needs stronger assessment, supervision, monitoring and escalation evidence. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Evidence item | What it should show | Assurance question |
|---|---|---|
| Stress risk assessment | Assessment covers demands, control, support, relationships, role and change. | Does it reflect work as done?Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Action plan | Actions target work causes, not only individual coping. | Are actions owned, dated and reviewed?Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Worker consultation | Workers and representatives contribute to findings and solutions. | Is there evidence of discussion and feedback?Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Support records | Private conversations, adjustments and referrals are recorded proportionately. | Is health information minimised?Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Risk assessment | Assessment describes the actual task, people affected, credible harm routes, controls and review triggers. | Compare against work as done, not only the written method.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Control standard | The required control is defined in operational terms. | Workers and supervisors can explain what must be in place before work starts.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Competence and briefing | People have suitable instruction, training, supervision and authorisation where needed. | Competence is checked through observed practice, not attendance alone.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Monitoring and defect action | Checks find weak signals, defects and non-compliance early. | Actions are risk-ranked, owned and closed with evidence.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Management review | Leaders review trends, repeat findings, high-risk actions and resource needs. | Decisions and learning are recorded.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
Keep the work record proportionate
Keep operational changes, owner and review date separate from clinical records. The privacy lead must confirm lawful processing, restricted access, retention and worker information; ICO: workers’ health information explains the Article 6 basis and separate Article 9 condition. Agreement to referral is not blanket processing consent. Check small-team reidentification risk before reporting themes.
How should mental ill-health and work-related stress be assured?
Assurance should test whether controls work in practice, not whether the page or procedure exists.
Assurance should include frontline checks, manager review and periodic independent sampling where risk warrants it. The purpose is to find weak signals early, close actions properly and update the risk assessment when work changes. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Assurance level | What to check | What good looks like |
|---|---|---|
| Frontline check | Workers and supervisors understand how mental ill-health and work-related stress is raised, controlled and escalated. | People can speak up early without stigma or unnecessary disclosure.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Manager review | Managers review workload, staffing, work design, incidents, adjustments, absence patterns and unresolved actions. | Actions address work causes and are reviewed.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Competent advice | OH, HR, EAP, GP or specialist input is used where medical, legal or high-risk decisions need it. | Managers do not make clinical judgements informally.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Leadership assurance | Leaders review trend data, worker voice, repeat concerns and resource barriers. | Wellbeing and health controls are connected to operational decisions.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
Confidentiality alongside necessary help
Necessary, proportionate sharing with appropriate emergency/health professionals may be needed to protect life. Consider an emergency contact carefully; this does not permit general team disclosure. Record what was needed, who received it and why without delaying help. ICO: information sharing in mental health emergencies at work.
How could Riverside Leisure Ltd manage this in practice?

Riverside Leisure Ltd would respond to individual concerns supportively while examining and improving the work conditions that may be contributing to stress.
In this leisure business, stress and mental health risks may arise from public aggression, rota pressure, lone opening, safeguarding concerns, emotional labour, seasonal demand and poorly managed change. Sources: HSE work-related stress and mental health; HSE Management Standards overview
| Management element | How the business would manage it | Evidence to review |
|---|---|---|
| Risk assessment | Teams with workload, violence or change pressures are assessed using Management Standards. | Stress assessment and action plan.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Manager support | Managers trained to discuss work impact and privacy. | Manager competence record.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Support route | EAP, OH, HR, first aid and crisis routes are visible. | Referral route map.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Safety-critical review | Lifeguarding, driving, plant rooms and lone work reviewed if fatigue or distress affects safety. | Task review.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
| Assurance | Absence, incidents, complaints and worker voice reviewed. | Leadership review minutes.Sources: HSE work-related stress and mental health; HSE Management Standards overview |
How does this topic align with ISO 45001?
Use these examples to connect the relevant clauses to your own occupational health and safety management system. For each clause, identify the person responsible, the control in use and the evidence that it works.
Scroll across the table to read all four columns.
| ISO 45001 clause | How it applies | What to put in place | How to verify it works |
|---|---|---|---|
| 6.1.2.1 Hazard identification | Hazard identification covers how work is organised. At Riverside’s reception, repeated missed breaks, competing instructions and challenging guest contact help locate problems in the way the shift operates. | Review peak periods and handovers with staff. Examine demand, cover, competing responsibilities, support and how staff can escalate difficult incidents. | The assessment identifies where the problems arise and which shifts are affected. Examples from rosters, handovers and incident reports inform the findings without disclosing individual health information. |
| 5.4 Worker consultation and participation | Workers can explain where planned cover fails and help choose changes that will work in practice. | Offer reception staff across shifts a confidential route to raise work-design issues, and involve staff or representatives in testing rota cover, handover and escalation changes. | Keep an anonymised summary of themes, decisions and actions. Staff feedback after the trial shows whether people can take breaks and obtain help when they need it. |
| 8.1.2 Hierarchy of controls | Changes to the work can reduce exposure to the stressors identified at reception. | Assign break cover by shift, name the person who sets priorities when instructions conflict and agree who takes over difficult guest incidents. Give managers authority to adjust staffing or task allocation when peaks recur. | Review break coverage and escalations during comparable busy periods. Check with staff whether the changes reduced conflicting demands and improved access to support. |
Selected applications of ISO 45001:2018 with Amendment 1:2024. Use the current standard for a full assessment and check the legal duties that apply to the work and location.
ISO 45001:2018 · 2024 climate action amendment · ISO 45002 implementation guidance · ISO technical committee clause FAQ
Which separate GB and NI legal routes apply?
Use the applicable GB or NI law for work-risk duties and equality; the management method supports assessment rather than replacing legislation.
GB general safety/management duties use the1974 Act and1999 Regulations; NI uses the1978 Order and2000 Regulations. Use the actual jurisdiction and work circumstances. The HSE and HSENI management factors guide prevention of work stress. Disability support needs its own applicable test under GB or NI equality legislation.
Voluntary-standard detail on hold
Specific standard editions, clauses and derived management-system detail are withheld until authorised text, rights and competent technical review are complete. Use applicable law and verified site evidence for current decisions.
For general health and safety management, see HSE managing health and safety.
What role-specific competence is needed?
Competence should match the decision: workers report concerns, managers control work, and competent health or emergency services handle clinical care.
Workers need an understandable reporting and immediate-help route. Supervisors practise safe cessation, task cover and escalation. Managers need worker consultation, stress-risk assessment, action ownership and review skills. Support-role training should define limits and referral; it is not authority to diagnose or provide treatment.
For violence or fatigue exposure, train those organising the shift in the actual prevention and response arrangement, and verify it through protected scenarios. Assess competence and availability across shifts rather than merely recording course attendance.
What do the acronyms and key terms mean?
These terms distinguish work, care and jurisdiction decisions.
| Term | Full name | Meaning here |
|---|---|---|
| GB | Great Britain | England, Scotland and Wales for these work-law routes. Health and Safety at Work etc. Act 1974 |
| NI | Northern Ireland | Separate work-safety and equality routes. Health and Safety at Work (NI) Order 1978 |
| HSE | Health and Safety Executive | Great Britain workplace regulator. HSE work-related stress and mental health |
| HSENI | Health and Safety Executive for Northern Ireland | Northern Ireland workplace regulator. HSENI work-related stress Management Standards |
| DDA | Disability Discrimination Act | Northern Ireland disability adjustment route. Disability Discrimination Act 1995 |
| EAP | employee assistance programme | Optional support; cannot replace risk controls. HSE work-related stress and mental health |
| ERICPD | Eliminate, Reduce, Isolate, Control, PPE, Discipline | A control-selection aid; sustain controls through supervision, maintenance and learning. It creates no separate legal duty. |
Unlock another resource
You have used this month’s two free downloads. Publish a post in your own words to unlock one more resource, or choose SHARE Individual for 10 downloads per month.
You decide whether to share. If you do, use the relevant platform disclosure tools and do not make claims you do not genuinely hold.