SHARE Knowledge Hub
Rotator Cuff Tendinopathy
Rotator cuff-related shoulder pain can be caused or aggravated by repeated or forceful overhead work, awkward reach, static loading and poor recovery. Pain does not prove a single tendon diagnosis or that work was the sole cause. Employers should reduce risky shoulder loading, respond early to symptoms, adapt duties and check the redesigned task; a clinician should assess symptoms, especially after injury or with urgent signs.
Understanding Rotator Cuff Tendinopathy
Rotator cuff-related shoulder pain can be caused or aggravated by repeated or forceful overhead work, awkward reach, static loading and poor recovery. Pain does not prove a single tendon diagnosis or that work was the sole cause. Employers should reduce risky shoulder loading, respond early to symptoms, adapt duties and check the redesigned task; a clinician should assess symptoms, especially after injury or with urgent signs.
Why this matters at work
Unsafe shortcut: treating a condition label as the risk assessment or assuming treatment removes the employer's duty. Escalate when a material exposure, worker group, clinical interface or accountable owner is missing. Record the hold point, interim protection, authorised decision-maker and evidence required before work or closure can proceed. Another competent reviewer should be able to reconstruct the task, exposure, worker input, clinical boundary, control choice, verification result and residual uncertainty.
Does the assessment represent real shoulder exposure? Minimum record: Task inventory; representative observation; arm elevation, force, reach, repetition, holding, duration, recovery, tools, environment, organisation, side and whole-shift evidence; worker validation. Escalate when: Peak, cumulative or combined exposure is unknown, the method is out of scope, or symptoms conflict with a reassuring score.
How organisations manage this in practice
Record the assessed tasks, relevant exposures, worker input, assumptions and control changes. Direct observation should show whether elevation, force, static loading or prolonged bouts have reduced and whether recovery is available during normal and peak demand. Verify that tools and supports are maintained, material presentation stays suitable and workers can use the revised method. A purchase record or training attendance may show implementation activity, but not the reduction of the physical demand itself. Combine work evidence with confidential symptom and functional feedback, without assuming a single report proves causation or silence proves success. Track open actions, temporary arrangements and any new risks. Review after symptoms, task or equipment change, increased workload or a failed control. Link assessments to current versions and owners so another supervisor can implement them. Escalate unresolved high demand, recurring symptoms or uncertain function to appropriate ergonomic and health expertise. Do not convert monitoring into compulsory clinical testing or make return conditional on a manager interpreting scans or treatment results.
Unsafe shortcut: using tendinitis, tear or impingement as a certain diagnosis because pain occurs on arm elevation. Escalate when terminology would change referral, treatment, reporting, employment or control decisions. Closure requires evidence that exposure or work changed and that the control remains available, usable and effective at real operating rate.
Is closure effective and durable? Minimum record: Before-and-after exposure; field observation; use and maintenance; worker reports; recurrence and trend review; residual-risk owner; audit; review date and explicit reopening triggers. Escalate when: Purchase, installation, treatment or signed paperwork is being counted as success without proof that work and outcomes improved.
Compare reach, force, hold time and recovery together
An altered painting method can reduce reach yet increase tool weight or leverage. Work-demand assessment is separate from diagnosis and treatment of shoulder symptoms.

Observe the whole task
Consider sustained elevation, force, repetition, tool support and recovery without a safe-angle or safe-minutes rule.
Trial a suitable method
Assess access and balanced tools together, including new work-at-height and handling risks.
Check the actual demand
Ask whether shoulder loading fell or simply moved; review the whole cycle and genuinely different duties.
Respond early
Use worker feedback and appropriate clinical advice for symptoms. A hand or wrist anatomy view does not teach cuff pathology or authorise a shoulder lesion overlay.
Read the complete task-specific control examples
ERICPD is a planning cross-map: Discipline verifies and sustains every control. ESEAP compares effectiveness. A label does not authorise the task; retain the owner, evidence and stop or change decision.
Rotator Cuff Tendinopathy · ERICPD
- Eliminate
- Prefabricate or finish panels at bench height where feasible.
- Reduce
- Use a height-adjustable platform and balanced extension tool to lower arm elevation and force.
- Isolate
- Use a compatible tool-support arm or jig on the approved access platform to take applicator weight and keep the shoulder below prolonged elevation.
- Control
- Set work-rest pattern, rotation and early-report trigger based on observed load.
- PPE
- There is no PPE that removes overhead tendon load.
- Discipline
- Brief the method, train in reporting and verify the controls in the field.
Rotator Cuff Tendinopathy · ESEAP
- Elimination
- Prefabricate or finish panels at bench height where feasible.
- Substitution
- No separate substitute is specified. Compare suitable safer materials, equipment or processes; check new risks before any change.
- Engineering controls
- Use a height-adjustable platform and balanced extension tool to lower arm elevation and force.
- Administrative controls
- Set work-rest pattern, rotation and early-report trigger based on observed load.
- PPE
- There is no PPE that removes overhead tendon load.
What is rotator cuff tendinopathy in a workplace context?
Rotator cuff-related shoulder pain describes several possible painful shoulder conditions, not a diagnosis a manager can make. Repeated or forceful overhead work can aggravate symptoms; assess loading and redesign the task. After a fall with sudden severe pain or inability to move the arm, stop the task and obtain urgent assessment: use urgent GP/NHS 111 advice in England, the local urgent-care route in Scotland or Wales, or the nearest emergency department in Northern Ireland as nidirect advises. Do not delay for routine OH or modified duties; a manager must not diagnose rotator cuff tendinopathy.
Shoulder work demand: what actually needs redesign?


Read the complete visual as text
- OVERHEAD REACH: Raises arm above shoulder height and increases tendon load. Recognise it in: Painting ceilings, fitting ductwork, installing cable tray or stocking high shelves.
- SUSTAINED POSTURE: Keeps the shoulder loaded without recovery. Recognise it in: Holding tools overhead or maintaining awkward reach.
- REPETITION: Repeated movement can irritate tissues over time. Recognise it in: Assembly, scanning, packing, sanding, wiping or food production tasks.
- FORCE: High grip, push, pull or tool pressure increases load. Recognise it in: Drilling, polishing, scraping, pulling cages or moving equipment.
- POOR RECOVERY: Insufficient breaks or rotation increases cumulative load. Recognise it in: Long shifts of the same overhead or repetitive task.
- ENVIRONMENT: Cold, poor lighting or cramped space can worsen posture and force. Recognise it in: Outdoor winter work, plant rooms or roof voids.
- PSYCHOSOCIAL FACTORS: High workload, low control or pressure can worsen reporting and recovery. Recognise it in: Worker hides symptoms to keep up with targets.
A workplace cannot establish a shoulder diagnosis from symptoms or a task assessment. HSE upper-limb guidance supports reviewing force, posture, repetition and recovery in the actual work; individual diagnosis and treatment remain for an appropriate clinician.
Repeated arm elevation, sustained force and insufficient recovery can increase shoulder loading. A report of pain is a reason to review the task and offer suitable support, not proof that work caused a specific tendon condition. If an injury or symptom makes the task unsafe, stop that task and obtain appropriate clinical advice.
The rotator cuff is a group of muscles and tendons that help stabilise and move the shoulder. Tendinopathy can involve pain, weakness, reduced movement or difficulty with overhead tasks. Work may be one contributing factor rather than the only cause, so managers should focus on work impact and task risk rather than diagnosis.
The practical workplace question is not 'what exactly is the medical diagnosis?' but 'what tasks load the shoulder, what can be redesigned, what temporary restrictions are needed, and how can early symptoms be acted on before the condition becomes long-term?'
| Risk factor | How it loads the shoulder | Example |
|---|---|---|
| Overhead reach | Raises arm above shoulder height and increases tendon load. | Painting ceilings, fitting ductwork, installing cable tray or stocking high shelves. |
| Sustained posture | Keeps the shoulder loaded without recovery. | Holding tools overhead or maintaining awkward reach. |
| Repetition | Repeated movement can irritate tissues over time. | Assembly, scanning, packing, sanding, wiping or food production tasks. |
| Force | High grip, push, pull or tool pressure increases load. | Drilling, polishing, scraping, pulling cages or moving equipment. |
| Poor recovery | Insufficient breaks or rotation increases cumulative load. | Long shifts of the same overhead or repetitive task. |
| Environment | Cold, poor lighting or cramped space can worsen posture and force. | Outdoor winter work, plant rooms or roof voids. |
| Psychosocial factors | High workload, low control or pressure can worsen reporting and recovery. | Worker hides symptoms to keep up with targets. |
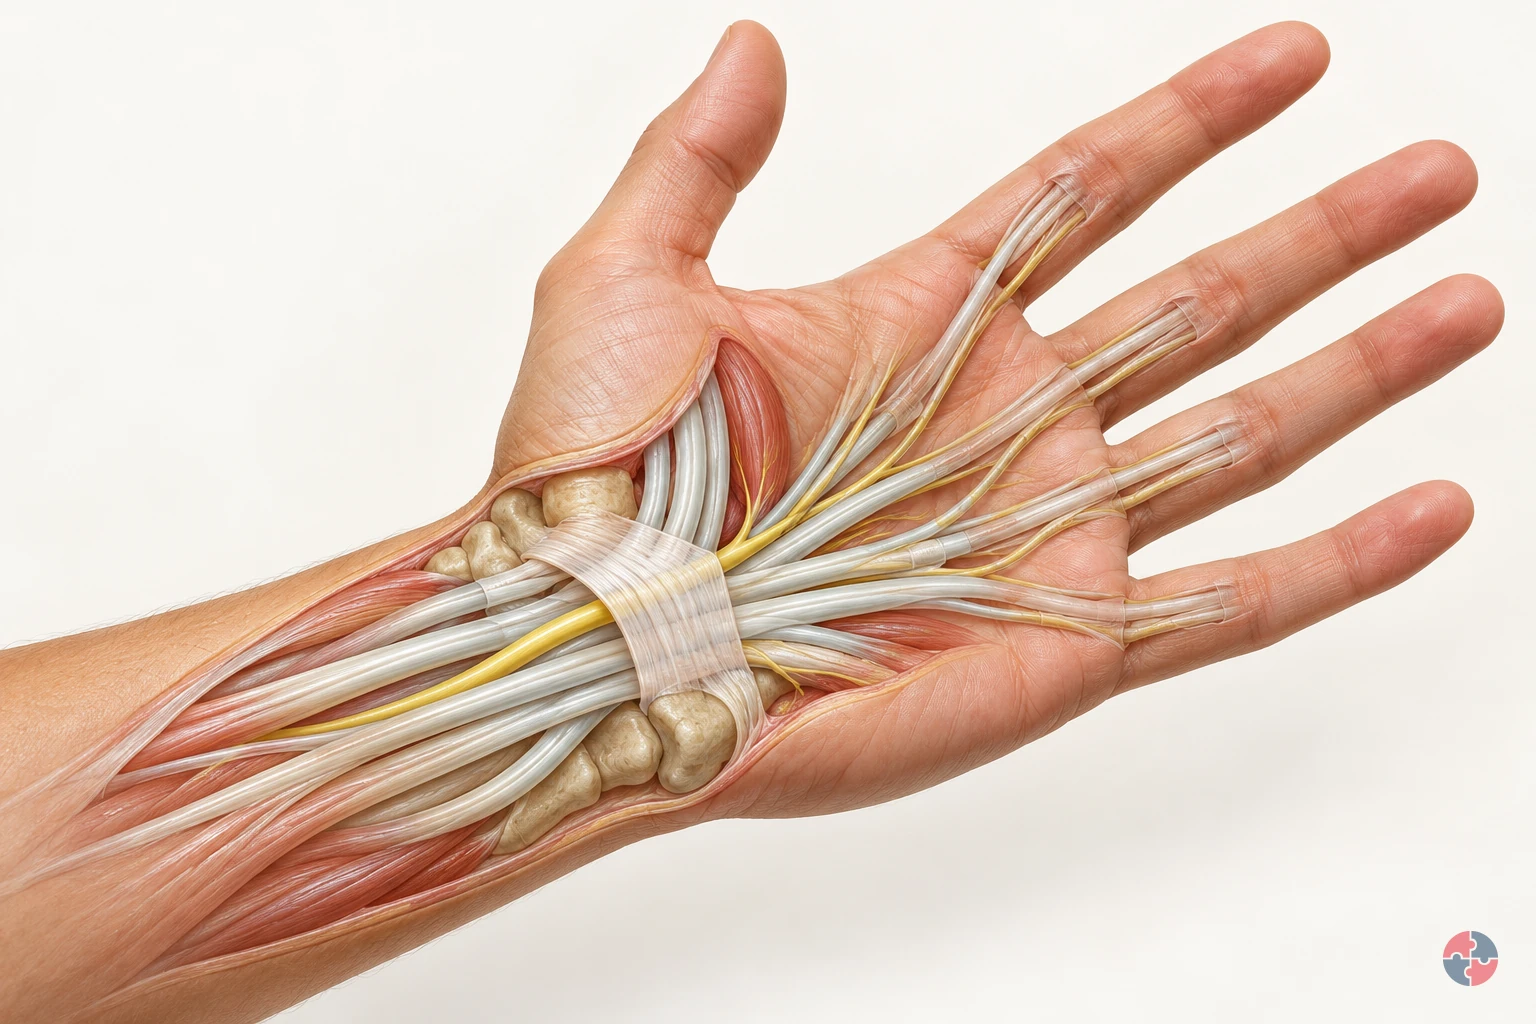

How does a working hand move, and what changes in nerve and tendon problems?
Interactive anatomy · Tendons, nerves and cushioning tissues · Updated 2026-10-23
Read all anatomy and process explanations without the viewer
General anatomy and example mechanisms, not diagnosis, treatment choice or fitness-for-work assessment. These are examples of mechanisms. Similar symptoms can have different causes. Self-provocation or nerve-tapping tests Exercise or stretching prescriptions Automatic symptom classification or a generic RSI lesion Treatment, return-to-work clearance or a task-based diagnosis Unreviewed shoulder, medial-elbow or trigger-finger damage overlays The prepatellar-bursitis route requires the dedicated labelled front-of-knee inset. A wrist/shoulder substitute is not suitable. Prompt-help text remains outside the model and scenarios.
Forearm flexor muscles
These muscles contract and pull through tendons to bend the fingers and thumb. The forearm flexor muscles generate the pull transmitted through tendons into the fingers and thumb. As the illustrated grip closes, follow the muscle region towards those slender connections. Their action bends the finger joints; the tendon transfers the pull rather than generating it. The visible shape change makes this relationship clearer and does not measure muscle effort. Gloucestershire Hospitals NHS Foundation Trust: Flexor Tendon Injuries
Flexor tendons
These tendons carry muscle force into the hand. Flexor tendons connect forearm muscles with bones in the hand. Their glide lets a muscle’s pull bend the finger joints while guided paths keep the tendons near the skeleton. Nine flexor tendons pass through the carpal tunnel. Compare their mechanical role with the nearby median nerve, which carries signals rather than pulling on bone. Gloucestershire Hospitals NHS Foundation Trust: Flexor Tendon Injuries · Whittington Health NHS Trust: Carpal Tunnel Syndrome
Tendon sheath
The sheath surrounds the tendon and supports smooth glide. A tendon sheath surrounds and supports a tendon as it glides. Along the fingers, pulley structures help keep the tendon close to the bones so its pull acts along a guided route. Watch the tendon move relative to its surroundings. A sheath is part of that supporting passage, not another muscle producing the same pull. Gateshead Health NHS Foundation Trust: Trigger Finger/Thumb Release Surgery
Carpal bones
Eight small carpal bones make up the wrist. Their curved arrangement forms the bony side of the carpal tunnel. The transverse carpal ligament closes the tunnel across the palm side. King’s College Hospital NHS Foundation Trust: Carpal tunnel syndrome — patient information · Kent Community Health NHS Foundation Trust: Carpal tunnel syndrome guide for patients
Transverse carpal ligament
This strong ligament spans the palm side of the wrist. It forms the roof above the median nerve and flexor tendons. Separating layers in the model helps reveal these relationships. King’s College Hospital NHS Foundation Trust: Carpal tunnel syndrome — patient information · Whittington Health NHS Trust: Carpal Tunnel Syndrome
Median nerve
The median nerve carries signals for feeling and some thumb movement. The median nerve carries sensory information from the thumb, index and middle fingers and part of the ring finger, and helps control some thumb muscles. Follow its branches beyond the shared wrist passage. The cyan travel cue represents communication; it is not a visible electrical flash, a nerve-speed measurement or a map for diagnosing altered sensation. NHS: Carpal tunnel syndrome · Kent Community Health NHS Foundation Trust: Carpal tunnel syndrome guide for patients · Whittington Health NHS Trust: Carpal Tunnel Syndrome
Thumb tendon: APL
Abductor pollicis longus helps move the thumb away from the hand. APL passes along the thumb side of the wrist through the first dorsal compartment. Follow it towards the base of the thumb. Ashford and St Peter’s Hospitals NHS Foundation Trust: De Quervains · Wrightington, Wigan and Leigh Teaching Hospitals NHS Foundation Trust: De Quervain’s Syndrome
Thumb tendon: EPB
Extensor pollicis brevis helps straighten the thumb. EPB travels beside APL through the first dorsal compartment on the thumb side of the wrist. Ashford and St Peter’s Hospitals NHS Foundation Trust: De Quervains · Wrightington, Wigan and Leigh Teaching Hospitals NHS Foundation Trust: De Quervain’s Syndrome
First dorsal compartment
A small passage on the thumb side of the wrist guides APL and EPB. The tendons normally glide through their sheath here. This is the location of the De Quervain’s example; the carpal tunnel lies on the palm side. Ashford and St Peter’s Hospitals NHS Foundation Trust: De Quervains · Wrightington, Wigan and Leigh Teaching Hospitals NHS Foundation Trust: De Quervain’s Syndrome
Outer elbow tendon attachment
Forearm tendons attach to bone near the outside of the elbow. Forearm extensor tendons attach near the bony point on the outside of the elbow, the lateral epicondyle. These muscles extend and help steady the wrist during gripping. Link the closer attachment view with the tool task to see why an elbow structure matters during hand use. Pain here does not establish a torn or detached tendon. NHS: Tennis elbow · Berkshire Healthcare NHS Foundation Trust: Advice and resources: Lateral elbow tendinopathy · Newcastle Hospitals NHS Foundation Trust: Tennis elbow
Prepatellar bursa
A fluid-containing sac helps reduce friction at the front of the kneecap. The prepatellar bursa lies between the kneecap and the overlying soft tissues, outside the knee joint. Its fluid-containing structure helps cushioning and smooth glide over bone. Compare the closer view with the worker’s knee contact in the floor task. The normal view locates the sac; it does not diagnose inflammation or measure pressure during kneeling. NHS: Bursitis · Leeds Community Healthcare NHS Trust: About pre-patella bursitis
Open the complete process transcript
The process, step by step
Watch muscles pull and tendons glide
The forearm muscles provide much of the pull that closes the fingers around an object. When these muscles contract, their tendons transmit force into the hand and pull on the finger bones, bending the joints. The tendons glide along guided paths rather than pulling away from the fingers like loose cords. Follow the muscle-to-tendon connection as the illustrated grip closes, then follow the return movement as the hand opens. The model enlarges this motion so that you can connect the movement at the fingers with the working structures farther up the forearm. Gloucestershire Hospitals NHS Foundation Trust: Flexor Tendon Injuries · Gateshead Health NHS Foundation Trust: Trigger Finger/Thumb Release Surgery
What to watch: Look from the forearm muscle bellies towards the slender flexor tendons, then follow their paths into the fingers around the handle.
Why it matters: Tendons transfer a muscle’s mechanical pull to bone, allowing joints to move. Guided tendon paths help direct that pull through the hand; the nerve has a different role in signalling.
Explore this step: Pause during the grip and trace one tendon from its forearm muscle towards the finger.
Watch tendon glide through the wrist
The carpal tunnel is a passage at the wrist, with a bony boundary formed by the carpal bones and a strong ligament spanning the palm side. Nine flexor tendons and the median nerve pass through this shared space. The tendons transmit the pull that helps bend the fingers and thumb; the nerve carries signals. Follow the tendon movement beneath the ligament roof and compare it with the nerve’s position. The cutaway separates the layers for learning, but these structures normally remain close together within a connected wrist. King’s College Hospital NHS Foundation Trust: Carpal tunnel syndrome — patient information · Kent Community Health NHS Foundation Trust: Carpal tunnel syndrome guide for patients · Whittington Health NHS Trust: Carpal Tunnel Syndrome
What to watch: Find the carpal bones and ligament roof, then compare the flexor tendons with the median nerve passing through the same wrist passage.
Why it matters: The tunnel brings several structures through a compact part of the wrist. Understanding their different functions explains why tendon glide and nerve signalling must be explored separately even though they occupy nearby space.
Explore this step: Use the labels to identify the tunnel boundary, a tendon and the nerve without changing to an injury example.
Follow the nerve signal
The median nerve links part of the hand with the nervous system. It carries sensory information from the thumb, index finger, middle finger and part of the ring finger, and helps control some muscles at the base of the thumb. Follow the cyan travelling cue along the nerve and into its branches. This colour illustrates signalling; a real nerve does not visibly light up. Compare that pathway with the tendons beside it: tendons transfer mechanical pull, whereas the nerve carries information. The simplified branches are a teaching map, not a test of a person’s sensation. Kent Community Health NHS Foundation Trust: Carpal tunnel syndrome guide for patients · Whittington Health NHS Trust: Carpal Tunnel Syndrome
What to watch: Follow the cyan cue along the median nerve through the wrist into the palm, keeping the adjacent tendons in view.
Why it matters: Sensation helps the nervous system receive information from the hand, while motor signals contribute to thumb control. Distinguishing information from mechanical pull makes the coordinated hand function easier to understand.
Explore this step: Compare the nerve cue with tendon glide and explain which one represents information and which represents force transfer.
Follow the thumb tendons
Two tendons run along the thumb side of the wrist through the first dorsal compartment. They connect forearm muscles to the thumb and glide as the thumb changes position. Abductor pollicis longus, labelled APL, helps move the thumb away from the hand. Extensor pollicis brevis, labelled EPB, helps straighten it. Follow the two labelled paths rather than assuming they pass through the palm-side carpal tunnel. The model brings their movement and location into view so that the separate actions and their shared guiding passage can be understood together. Ashford and St Peter’s Hospitals NHS Foundation Trust: De Quervains · Wrightington, Wigan and Leigh Teaching Hospitals NHS Foundation Trust: De Quervain’s Syndrome
What to watch: Find APL and EPB beside the thumb side of the wrist, then follow both labelled paths through the first dorsal compartment.
Why it matters: Different tendon actions contribute to positioning the thumb for hand use. Their shared passage guides glide, but the two tendons retain different attachments and functions; they are not interchangeable parts.
Explore this step: Select each tendon in turn and connect its name with the thumb movement described in the explanation.
Follow the elbow during a tool task
A tool task involves more than the muscles that visibly close the fingers. Forearm extensor muscles also help hold the wrist steady while the hand grips. Follow these muscles back towards their tendon attachment near the bony point on the outside of the elbow, called the lateral epicondyle. Watch the technician’s illustrated grip and tool turn, then use the closer elbow view to connect the activity with this attachment. A moving tool does not demonstrate a damaged tendon: the normal task and the separate tissue example explain different things. NHS: Tennis elbow · Newcastle Hospitals NHS Foundation Trust: Tennis elbow
What to watch: Watch the hand grip the screwdriver, then follow the working forearm towards the tendon attachment on the outside of the elbow.
Why it matters: Wrist stability helps the hand grip and use an object, so a tendon attachment near the elbow can be involved in a hand task. Movement alone does not show injury or quantify the demand.
Explore this step: Switch between Work activity and Elbow cutaway and describe how the two views relate to the same task.
Locate the bursa in front of the kneecap
The prepatellar bursa is a small fluid-containing sac in front of the kneecap. It helps the overlying soft tissues move across the bone with less friction. First locate the front of the knee in the floor-laying task, then follow the linked closer view to the thin sac outside the knee joint. This shows where contact during kneeling relates to the anatomy; the bursa is not a cushion inside the joint. The normal location lesson remains separate from the example of bursal irritation, and the short model sequence does not predict when symptoms would occur. Leeds Community Healthcare NHS Trust: About pre-patella bursitis · NHS Musculoskeletal Matters Dorset: Prepatellar bursitis
What to watch: Locate the kneeling worker’s front-of-knee contact, then find the thin bursa between the kneecap and the overlying soft tissues in the close view.
Why it matters: Glide between soft tissue and bone is a different function from movement inside the knee joint. Locating the bursa makes the relevant contact area clear without inferring tissue damage from posture alone.
Explore this step: Compare Floor-laying task with Knee cutaway and identify which side of the kneecap contains the bursa.
Read the practice situations and all answer explanations
Sources and how the model is made
The opening images are AI-generated anatomical illustrations. The interactive 3D models and labelled SVG diagrams use original procedural artwork. These teaching images are not medical scans or diagnostic tools. Source references support the learner explanations and do not grant artwork rights.
- Health and Safety Executive: Upper limb disorders — Multiple work factors, task redesign, force/repetition/posture/duration, worker involvement and early reporting. Risk scores are not diagnosis.
- NHS: Carpal tunnel syndrome — Median-nerve pressure, potential sensory and functional effects, varied contributors and clinical assessment. No treatment or self-test generated.
- King’s College Hospital NHS Foundation Trust: Carpal tunnel syndrome — patient information — Bony tunnel boundary and transverse carpal-ligament roof. Text only, no third-party credited artwork copied. Printed review date September 2026 requires recheck at clinical sign-off; corroborates NHS anatomy.
- Ashford and St Peter’s Hospitals NHS Foundation Trust: De Quervains — APL and EPB actions and thumb-side first dorsal compartment. Indexed primary-page text rechecked, updated 28 April 2026; corroborated by directly retrieved UL8. No treatment recommendations or artwork copied.
- NHS: Tennis elbow — Outer-elbow location, tendon attachment and possible repeated gripping/twisting context. More precise tendinopathy wording corroborated by UL12/UL14; no blanket inflammation claim.
- NHS: Bursitis — Fluid-sac cushioning, inflammation and pressure-reduction context. Printed next-review date 30 October 2026 should be rechecked at sign-off.
- NHS: Tendonitis — General tendon role and urgent professional advice for severe pain or suspected rupture. Printed next-review date June 2026 is overdue: recheck before clinical approval. No treatment/exercise regimen reused.
- Wrightington, Wigan and Leigh Teaching Hospitals NHS Foundation Trust: De Quervain’s Syndrome — Directly retrieved January 2026 leaflet, expiry January 2028: APL/EPB, thumb-side first dorsal compartment and constrained sheath glide. Anatomy/mechanism only; no exercises or artwork copied.
- Gloucestershire Hospitals NHS Foundation Trust: Flexor Tendon Injuries — Directly retrieved: flexor tendons connect forearm muscles to finger bones and transmit their pull. Used for normal function only; no injury prognosis, treatment instructions or artwork reused.
- Gateshead Health NHS Foundation Trust: Trigger Finger/Thumb Release Surgery — Directly retrieved normal tendon/sheath distinction and guiding finger pulleys only. Printed review date September 2026 remains overdue; no trigger-finger overlay, surgical advice or exercise regimen reused.
- Ashford and St Peter’s Hospitals NHS Foundation Trust: Carpal Tunnel — Median-nerve sensory/motor role and flexor tendons within the tunnel. Indexed primary text verified, updated 28 April 2026; direct retrieval failed. Recheck live source at clinical sign-off.
- Berkshire Healthcare NHS Foundation Trust: Advice and resources: Lateral elbow tendinopathy — Painful forearm tendon attachment near the outside of the elbow and possible repetitive work demands. No treatment regimen, recovery prediction or artwork copied.
- Leeds Community Healthcare NHS Trust: About pre-patella bursitis — Dedicated bursa in front of kneecap, cushioning/glide, kneeling/direct injury/infection and urgent GP assessment for fever or feeling unwell. No treatment selection.
- NHS MyHealth Devon: Golfers & Tennis Elbow — Forearm tendon attachments and tendinopathy wording: not equated with simple inflammation. No rehabilitation or prognosis claims reused.
- NHS Musculoskeletal Matters Dorset: Prepatellar bursitis — Front-of-knee friction-reducing sac; prolonged kneeling, direct injury and infection as distinct possible causes. No medicine or cooling regimen reused.
- Kent Community Health NHS Foundation Trust: Carpal tunnel syndrome guide for patients — Directly retrieved, last edited 9 July 2025: eight carpal bones, ligament boundary, median-nerve sensory/motor role and tendon passage. Anatomy facts paraphrased only; no clinical regimen or artwork copied.
- Whittington Health NHS Trust: Carpal Tunnel Syndrome — Directly retrieved, updated 7 August 2025: nine tendons and median nerve in the carpal tunnel, nerve function and cautious attribution of work contribution. Normal anatomy corroborated by Sherwood Forest Hospitals NHS leaflet PIL202409-06-CTS; that leaflet has a September 2026 review date. No treatment recommendations or artwork reused.
- Newcastle Hospitals NHS Foundation Trust: Tennis elbow — Directly retrieved, last updated 3 November 2025: forearm tendons attach at the lateral epicondyle; these muscles extend the wrist and take part in gripping. Used for extensor anatomy and task explanation only; no treatment regimen, work-clearance advice or artwork copied.
- Health and Safety Executive: Lower limb disorders — Directly retrieved, updated 27 March 2025: repeated kneeling and knee bursitis; review working methods, mechanical aids, task variation, breaks, seating where possible, and suitable knee pads or matting. Used for prevention principles only; no numerical kneeling threshold, diagnosis or guarantee of protection.
How can the hierarchy of controls reduce forceful and overhead work linked to shoulder injury?
Observe actual arm height, force, repetition, static hold, duration and recovery, including non-routine work. A DSE training record cannot control unchanged overhead force and reach: redesign the task through layout or lifting aids before relying on breaks or training, assign an owner and verify the changed work with workers.
The task factors and early response follow HSE upper-limb guidance and HSENI upper-limb guidance. The HSE five-level hierarchy explains why source removal and engineering outrank training and PPE.
For the sports-hall ceiling example, use ERICPD (Eliminate, Reduce including substitution, Isolate, Control, Personal Protective Equipment, Discipline) as a teaching prompt, not a statutory checklist. The facilities manager owns the task design; the competent assessor observes the task; the supervisor checks the live setup with workers. Check whether the arm spends less time above shoulder height, tools need less force and symptoms are reported early. Stop overhead work for a worker whose pain or weakness makes the task unsafe, or when the planned platform/tool control is unavailable; arrange a safer task and appropriate clinical advice.
How can the ERICPD hierarchy of controls reduce forceful and overhead work linked to shoulder injury?

| Level | Five-level match and feasibility | Control in the ceiling job | How it interrupts harm | Field evidence or failure signal |
|---|---|---|---|---|
| Eliminate | Elimination. Prefabricated panels remove some, not all, overhead painting; site edges and repairs still need access. | Prefabricate or finish panels at bench height where feasible. | Removes overhead arm loading for that work. | Facilities manager checks planned overhead minutes before and after prefabrication; stop and redesign if the same ceiling load remains. |
| Reduce | Substitution plus engineering. Specify lighter, balanced applicators and adjustable access after trial; verify they do not introduce reach or fall risk. | Use a height-adjustable platform and balanced extension tool to lower arm elevation and force. | Cuts dose of awkward posture and force. | Ergonomic assessor trials arm height, tool force and duration with workers; stop if reach or a new fall/tool hazard remains uncontrolled. |
| Isolate | Engineering controls. A supported tool and access setup physically reduces arm elevation; scheduling alone is administrative, not isolation. | Use a compatible tool-support arm or jig on the approved access platform to take applicator weight and keep the shoulder below prolonged elevation. | An engineered support reduces the force and static hold; a work window alone is an administrative control. | Facilities engineering selects and commissions the support; supervisor checks fit, stability and use before work. Stop if the support cannot be mounted securely. |
| Control | Administrative controls. Rotation and breaks limit residual exposure only after source redesign; test actual load and missed breaks. | Set work-rest pattern, rotation and early-report trigger based on observed load. | Limits sustained exposure while redesign is completed. | Supervisor checks actual task logs and worker feedback; stop overhead work if breaks fail or pain reports repeat. |
| PPE | PPE. No shoulder brace or glove is established here as preventing tendon overload. Select task PPE for separate chemical/fall risks under its own assessment; never count it as shoulder control. | There is no PPE that removes overhead tendon load. Use separate task-specific PPE only for distinct hazards under their own assessment. | Do not credit a shoulder strap, glove or generic PPE as preventing overload; keep the source redesign and work restriction. | Check actual shoulder exposure and separate PPE fit/condition if required for other hazards; stop if the overhead load remains unsafe. |
| Discipline | Administrative assurance. Brief, supervise, maintain and learn from reports; discipline sustains stronger controls and is not blame. | Brief the method, train in reporting and verify the controls in the field. | Keeps the higher-order controls in use; instruction alone cannot remove the load. | Supervisor observation and action close-out; failure if training is the only change. |
How can the ISO 45001 hierarchy of controls reduce forceful and overhead work linked to shoulder injury?

| Level | Five-level match and feasibility | Control in the ceiling job | How it interrupts harm | Field evidence or failure signal |
|---|---|---|---|---|
| Eliminate | Elimination. Prefabricated panels remove some, not all, overhead painting; site edges and repairs still need access. | Prefabricate or finish panels at bench height where feasible. | Removes overhead arm loading for that work. | Facilities manager checks planned overhead minutes before and after prefabrication; stop and redesign if the same ceiling load remains. |
| Reduce | Substitution plus engineering. Specify lighter, balanced applicators and adjustable access after trial; verify they do not introduce reach or fall risk. | Use a height-adjustable platform and balanced extension tool to lower arm elevation and force. | Cuts dose of awkward posture and force. | Ergonomic assessor trials arm height, tool force and duration with workers; stop if reach or a new fall/tool hazard remains uncontrolled. |
| Isolate | Engineering controls. A supported tool and access setup physically reduces arm elevation; scheduling alone is administrative, not isolation. | Use a compatible tool-support arm or jig on the approved access platform to take applicator weight and keep the shoulder below prolonged elevation. | An engineered support reduces the force and static hold; a work window alone is an administrative control. | Facilities engineering selects and commissions the support; supervisor checks fit, stability and use before work. Stop if the support cannot be mounted securely. |
| Control | Administrative controls. Rotation and breaks limit residual exposure only after source redesign; test actual load and missed breaks. | Set work-rest pattern, rotation and early-report trigger based on observed load. | Limits sustained exposure while redesign is completed. | Supervisor checks actual task logs and worker feedback; stop overhead work if breaks fail or pain reports repeat. |
| PPE | PPE. No shoulder brace or glove is established here as preventing tendon overload. Select task PPE for separate chemical/fall risks under its own assessment; never count it as shoulder control. | There is no PPE that removes overhead tendon load. Use separate task-specific PPE only for distinct hazards under their own assessment. | Do not credit a shoulder strap, glove or generic PPE as preventing overload; keep the source redesign and work restriction. | Check actual shoulder exposure and separate PPE fit/condition if required for other hazards; stop if the overhead load remains unsafe. |
| Discipline | Administrative assurance. Brief, supervise, maintain and learn from reports; discipline sustains stronger controls and is not blame. | Brief the method, train in reporting and verify the controls in the field. | Keeps the higher-order controls in use; instruction alone cannot remove the load. | Supervisor observation and action close-out; failure if training is the only change. |
HSE upper-limb guidance highlights repetition, awkward posture, excessive force, duration without rest and hand-held tool use as key risk factors. For shoulder problems, overhead work and sustained arm elevation need particular attention.
Use a staged approach: screen tasks, observe work, ask workers what causes discomfort, use ART or other MSD tools where appropriate, redesign the task, agree modified duties if symptoms appear and review whether controls work.
| Assessment factor | What to examine | Control direction |
|---|---|---|
| Posture | Arm elevation, reach distance, twisting and working height. | Lower work, raise platform, reposition task or use adjustable equipment. |
| Force | Tool pressure, load weight, push/pull demand and grip force. | Reduce force, use powered aids, improve handles or change method. |
| Repetition | Cycle time, same movement, task pace and production target. | Rotate tasks, automate, redesign workflow or add recovery. |
| Duration | How long the shoulder is loaded without change. | Limit exposure time and schedule breaks. |
| Recovery | Rest, micro-breaks and variation. | Build changes of posture and muscle group into work. |
| Tools | Weight, vibration, balance, trigger force and handle design. | Select lighter, balanced, low-vibration tools and supports. |
| Worker factors | Existing symptoms, recovery, restrictions or work ability. | Private work-impact conversation and OH advice where needed. |
Choose the assessment for the shoulder task
ART supports assessment of repetitive upper-limb tasks; it is not a DSE assessment and does not by itself cover every individual factor or complete the risk assessment. Use DSE assessment for screen work, the relevant handling assessment for lifting and a wider ergonomic review for static holds and other exposures. For the ceiling-work trial record arm elevation, supported/unsupported load, actual duration and worker feedback over a realistic task. Stop on worsening symptoms or an unsafe access/support condition; no universal safe-minute limit is established.
HSENI ULD guidance; NHS shoulder pain urgent-help advice; nidirect shoulder pain immediate advice; HSE ART assessment scope.
How would this appear in real work?
A worked example shows why rotator cuff prevention is mainly about work design, not telling people to stretch.
Sports-hall painting: reduce the overhead demand


Read the complete visual as text
- 1. RECOGNISE THE DEMAND: A facilities team paints the ceiling and upper walls. Light paint and an experienced workforce do not remove repeated arm elevation, sustained hold and recovery demands.
- 2. CHANGE ACCESS AND REACH: Supervisor and competent assessor select suitable access that brings the task into a comfortable reach. Do not rely on ladder stretching or on a platform that leaves the same prolonged arm elevation.
- 3. SELECT BALANCED TOOLS: Trial lighter, balanced tools and suitable extension handles for the actual work. Tool weight, leverage, grip and force matter as well as reaching the surface.
- 4. VARY THE EXPOSURE: Plan genuinely different tasks and recovery rather than leaving one worker overhead all day or rotating everyone through the same shoulder load.
- 5. RESPOND TO SYMPTOMS: Encourage early reporting and adjust duties promptly. Stop the high-load method if the aid fails or prolonged painful overhead work cannot be avoided; seek appropriate health advice without workplace diagnosis.
- 6. OBSERVE AND REVIEW: The supervisor checks the redesigned method during realistic task duration and production pace, asks about pain, fatigue and tool fit, and verifies that controls reduce the load before fuller duties.
A facilities team is repainting a sports hall ceiling and upper walls. The weak plan assumes the work is low risk because the paint is light and workers are experienced. After two days, one worker reports shoulder pain but keeps working overhead to stay on programme.
The stronger plan identifies overhead exposure before the job starts. It uses mobile access equipment at the right height, extension tools selected for balance, task rotation, limits on continuous overhead work, early reporting prompts, supervisor checks, and temporary modified duties if symptoms appear.
| Work issue | Weak handling | Stronger control |
|---|---|---|
| Planning | Treat as ordinary painting. | Identify overhead arm elevation and duration as risk factors. |
| Access | Use ladder and stretch to reach. | Use suitable platform or MEWP to keep work near comfortable height. |
| Tools | Use any available roller or drill mixer. | Select balanced, lighter tools and extension handles. |
| Exposure time | Same worker paints overhead all day. | Rotate tasks and limit continuous overhead work. |
| Symptoms | Worker carries on until pain worsens. | Encourage early reporting and adjust duties promptly. |
| Review | No check unless absence occurs. | Supervisor checks discomfort reports and task design daily. |
Ceiling installation with repeated overhead reach
Task, material and setting: Installers repeatedly hold tools above shoulder height while fixing ceiling panels.
People and prerequisites: Supervisor and ergonomic assessor observe height, force, duration and recovery; workers identify the hardest steps.
Before: Prefabricate at bench height, use a lifting aid and suitable platform, rotate genuinely different tasks and reduce sustained hold.
During: Check use at production pace and ask about pain, fatigue and tool fit.
Hold or stop: Stop the high-load method if lifting aid fails or workers cannot avoid prolonged painful overhead work.
Completion and hand back: Verify the redesigned method and review reported symptoms without diagnosing the cause.
Evidence: Keep task observation, design decision, training, symptom response and effectiveness check.
A worker returns with shoulder pain
Task, material and setting: A stock worker reports shoulder pain after a fall and cannot lift to high shelving comfortably.
People and prerequisites: Manager asks about work impact privately and refers to clinical care, especially if concerning symptoms needing clinical assessment apply.
Before: Assign lower-height tasks and lifting assistance while reviewing the shelf layout and load.
During: Supervisor checks actual reach and whether colleagues gain unsafe extra work.
Hold or stop: Hold high shelving if strength or pain makes safe handling uncertain; do not certify fitness from attendance.
Completion and hand back: Review work modification with competent advice and verify risk control before full duties.
Evidence: Keep work-risk review, confidential advice scope, adjustment owner and follow-up.
Which jobs and sectors commonly create shoulder risk?
Shoulder risk appears in construction, maintenance, cleaning, manufacturing, warehousing, care, vehicle repair and DSE work.
Rotator cuff risk is not restricted to heavy manual work. Light but repeated or sustained shoulder loading can matter, especially if there is poor recovery or awkward reach.
Examples make the controls easier to see: change the work height, bring the work closer, reduce force, change tools, rotate tasks and intervene early.
For ceiling maintenance, lower the work where feasible, use a platform that puts the hands below shoulder height and check the reach during the longest task period. For warehouse picking, move frequent heavy items into the easy-reach zone or change the handling method; rotating staff around identical high-reach tasks merely shares exposure. A supervisor should observe the revised task and ask whether symptoms or compensating movements remain. HSE upper-limb guidance supports redesign before reliance on instruction.
| Sector or task | Shoulder-risk pattern | Control focus |
|---|---|---|
| Construction finishing | Plastering, boarding, painting or fixing overhead. | Access height, sequencing, mechanical aids, rotation and exposure limits. |
| Vehicle repair | Sanding, polishing, drilling and reaching around panels. | Tool weight, vibration, grip force, task variation and trigger-time review. |
| Warehousing | Repeated high-level picking or shrink-wrap cutting. | Slotting, lift tables, reach limits and job rotation. |
| Cleaning | Mopping, wiping high surfaces, machine use and repetitive arm movement. | Tool length, force reduction, work planning and recovery. |
| Care work | Patient handling and reaching in awkward spaces. | Hoists, staffing, handling plans and training in real tasks. |
| Manufacturing | Assembly, packing, inspection or line work at poor height. | Workstation design, pace, automation and micro-breaks. |
| DSE and office work | Mouse/keyboard reach, unsupported arm or poor desk setup. | DSE review, arm support, input device position and breaks. |
What should happen when early symptoms are reported?
Early symptoms should trigger work review and support before pain becomes chronic or disabling.
This page is not medical advice. However, workplaces should encourage early reporting of pain, weakness, tingling, reduced movement or difficulty with overhead work. Early action is usually easier than managing long-term absence.
Managers should discuss work impact, not demand diagnosis detail. Occupational health, GP, physiotherapy or other medical advice may be needed where symptoms persist, restrictions are unclear or safety-critical work is affected.
A report of shoulder pain should start a work-risk conversation, not a workplace diagnosis. Ask which movement, load or duration aggravates the task; arrange a safer method and appropriate clinical or occupational-health advice where needed. Record the work adjustment and review point, while health details stay in the appropriate confidential channel. HSE upper-limb guidance supports early reporting and task redesign.
| Signal | Manager response | Risk-control action |
|---|---|---|
| Pain during overhead task | Private check-in and stop or vary aggravating task. | Review work height, duration and rotation. |
| Weakness or reduced movement | Avoid forcing full duties. | Seek OH/medical advice and agree modified duties. |
| Symptoms improve away from work | Consider work-related contribution. | Observe task and update assessment. |
| Repeated reports in same team | Treat as a work-design signal. | Review workload, workstation, tools and supervision. |
| Medication or fatigue affects task | Discuss work impact privately. | Review safety-critical tasks and temporary restrictions. |
| Long absence or return plan | Use phased return and review dates. | Link to return-to-work and OH guidance. |
Why is training not enough for rotator cuff risk?
Training helps, but it cannot fix poor height, excessive force, repetition, duration or lack of recovery.
A common failure is to brief workers on posture while leaving the task unchanged. If the work requires arms above shoulder height for hours, or repeated forceful reaching, the risk remains.
A higher-standard approach changes the task first: design, layout, tools, access, mechanical aids, pace, staffing and recovery. Training then supports the redesigned control.
For a ceiling fitting task, lowering the assembly or choosing equipment that brings the work into a comfortable reach changes the shoulder load itself. A platform can help only if its height and stability let the worker avoid prolonged arm elevation; the supervisor should observe the longest realistic task, not a brief demonstration. Breaks and instruction may support the new method, but persistent forceful overhead work is a reason to redesign again. HSE upper-limb guidance supports task-level assessment.
| Risk factor | Weak response | Better redesign |
|---|---|---|
| High reach | Tell worker not to overreach. | Bring work within comfortable reach or change access. |
| Overhead work | Tell worker to stretch before shift. | Use platform height, extension supports and exposure limits. |
| High force | Tell worker to use correct technique. | Reduce load, friction, tool pressure or use mechanical aid. |
| Repetition | Tell worker to pace themselves. | Change workflow, rotate tasks or automate repetitive elements. |
| Poor recovery | Tell worker to take breaks when possible. | Build planned recovery into the job. |
| Tool design | Tell worker to grip more carefully. | Select lighter, balanced and lower-vibration tools. |
What practical prompts help assess shoulder-loading tasks?
A supervisor should screen arm height, reach, force, repetition, static hold and recovery in real work, then eliminate or reduce the load with layout changes or lifting aids. Hold the task when painful high-load work cannot be controlled, and verify the redesign with workers.
This screen is deliberately practical. It can be used during a pre-task briefing, site walkaround, workstation review or return-to-work discussion. It does not diagnose rotator cuff tendinopathy; it identifies work conditions that may load the shoulder and need redesign.
Where the screen shows repeated or significant risk factors, the next step may be a more formal MSD/ULD assessment such as ART, ergonomic review, occupational health input for restrictions, or redesign by a competent person.
| Prompt | What to look for | Better control |
|---|---|---|
| Force | High push, pull, grip, tool pressure or load handling. | Reduce force, change method, use powered aid or improve grip/tool design. |
| Posture | Arm above shoulder height, long reach, twisting or unsupported arm. | Change height, bring work closer, improve access or support the arm/tool. |
| Repetition | Same shoulder movement repeated for much of the shift. | Rotate to genuinely different tasks, adjust pace or automate where practicable. |
| Duration | Continuous shoulder loading without task variation. | Set exposure limits and plan task changes before fatigue develops. |
| Recovery | Breaks depend on informal opportunity or worker choice under pressure. | Build micro-breaks, recovery and supervisor checks into the job plan. |
| Tool weight and balance | Heavy, nose-heavy, vibrating or awkward tools used above shoulder height. | Select lighter/balanced tools, supports, low-vibration options and maintained equipment. |
| Reach and work height | Worker stretches from ladder, platform, vehicle bay or workstation. | Raise/lower the work, adjust platform height, use jigs, lift tables or better access. |
| Early symptoms | Worker reports pain, weakness or reduced movement but carries on. | Stop aggravating exposure, review task, agree modified duties and set review date. |
How do rotator cuff risks show up in common roles?
Role examples help managers see that the control is usually better work design, not telling people to push through discomfort.
Rotator cuff risk often hides inside normal work. The task may not look heavy, but the combination of reach, repetition, tool pressure and poor recovery can accumulate over a shift or project.
Use these examples when briefing supervisors. Ask whether the work could be brought closer, lowered, raised, supported, rotated, paced differently or redesigned before relying on training.
| Role | Real-world risk pattern | Operational control |
|---|---|---|
| Painter or decorator | Ceilings and high walls create prolonged arm elevation. | Use correct access height, extension tools, exposure limits and task rotation. |
| Electrician | Cable tray, containment, drilling and fixing overhead. | Prefabricate where possible, use platforms, rotate tasks and choose lighter tools. |
| Warehouse picker | Repeated high-level picking or awkward shelf reach. | Improve slotting, use lift aids, lower high-frequency items and monitor discomfort. |
| Cleaner | High wiping, mopping force, machine use and repetitive movement. | Adjust tool length, reduce force, vary tasks and plan recovery. |
| Vehicle repair technician | Sanding, polishing and drilling around panels with sustained arm load. | Use tool supports, balance tools, rotate tasks and review vibration/force exposure. |
| Care worker | Manual handling, reaching around beds or awkward support tasks. | Use handling aids, staffing, care plans and stop if task differs from plan. |
| Office/DSE worker | Mouse reach, unsupported arm or workstation layout. | DSE review, input device position, arm support and movement variation. |
When should rotator cuff concerns be escalated?
Escalate when symptoms persist, work is aggravating the shoulder, safety-critical tasks are affected or multiple workers report similar issues.
Escalation should be practical and supportive. The first step is often to review the task and modify duties. Where symptoms persist, the worker needs medical or occupational health signposting and managers need functional advice about work restrictions.
Do not wait for formal diagnosis before improving the work. If the task has obvious risk factors, redesign can begin while individual support is arranged.
| Trigger | Escalation route | Immediate work response |
|---|---|---|
| Pain during or after shoulder-loaded task | Supervisor and H&S review. | Reduce overhead/forceful exposure and observe task. |
| Symptoms persist or restrict movement | Occupational health or GP/medical advice. | Temporary modified duties and review date. |
| Safety-critical work affected | Manager, OH and H&S adviser. | Review fitness for specific tasks without diagnosing. |
| Multiple reports in one task/team | H&S/ergonomics review. | Assess task design, pace and recovery. |
| Return after absence | Return-to-work process and OH if needed. | Phased return and work restrictions. |
| Tool vibration or force involved | HAVS/MSD competent review. | Review tools, trigger time, force and exposure. |
Urgent help is a separate decision
After injury, sudden severe shoulder pain or inability to move the arm needs urgent assessment rather than routine occupational-health or modified-duty review. In England, follow NHS advice to seek an urgent GP appointment or NHS 111 assessment; in Northern Ireland, nidirect directs these signs to the nearest emergency department. In Scotland or Wales use the local urgent-care route; do not assume one UK-wide service arrangement. Stop the aggravating task and obtain urgent help without asking a manager to diagnose the cause.
HSENI ULD guidance; NHS shoulder pain urgent-help advice; nidirect shoulder pain immediate advice; HSE ART assessment scope.
Where do rotator cuff controls commonly fail?
They fail when shoulder risk is treated as personal weakness instead of task design, recovery and early reporting.
Shoulder control failures: support early reports and change the task


Read the complete visual as text
- POSTURE ADVICE ONLY: Failure: Task still requires overhead or forceful work. Manager/assessor response: Redesign height, reach, tool and task duration.
- LATE REPORTING: Failure: Worker waits until pain becomes disabling. Manager/assessor response: Encourage early, blame-free reporting.
- POOR ROTATION: Failure: Worker rotates to a task using the same shoulder load. Manager/assessor response: Rotate by muscle group and exposure pattern.
- NO RECOVERY: Failure: Breaks depend on informal opportunity. Manager/assessor response: Plan recovery and variation.
- TOOL MISMATCH: Failure: Heavy or poorly balanced tools increase load. Manager/assessor response: Select tools for weight, balance, grip and vibration.
- PRIVACY DRIFT: Failure: Manager asks for diagnosis details. Manager/assessor response: Discuss work impact and restrictions only.
Rotator cuff and other upper-limb issues can be made worse when workers feel they must push through pain. A good workplace culture treats early reporting as useful risk information, not as complaining.
Managers should also avoid collecting unnecessary medical detail. They need to understand work impact, restrictions and controls, while medical interpretation stays with competent health professionals.
| Failure or weak practice | How it develops | What good looks like |
|---|---|---|
| Posture advice only | Task still requires overhead or forceful work. | Redesign height, reach, tool and task duration. |
| Late reporting | Worker waits until pain becomes disabling. | Encourage early, blame-free reporting. |
| Poor rotation | Worker rotates to a task using the same shoulder load. | Rotate by muscle group and exposure pattern. |
| No recovery | Breaks depend on informal opportunity. | Plan recovery and variation. |
| Tool mismatch | Heavy or poorly balanced tools increase load. | Select tools for weight, balance, grip and vibration. |
| Privacy drift | Manager asks for diagnosis details. | Discuss work impact and restrictions only. |
What evidence should rotator cuff risk management hold?
Evidence should show task risk factors, redesign decisions, early reporting, support and control verification.
The evidence should demonstrate that the organisation considered force, posture, repetition, duration and recovery before relying on training. This is particularly important where work is repeated across sites or shifts.
Individual health records should be limited and confidential. Keep local management records focused on work restrictions, adjustments and review dates.
| Evidence item | What it should show | Assurance question |
|---|---|---|
| Risk assessment or technical assessment | Scope, hazards, affected people, controls, residual risk, owners and review triggers. | Does it match the work as done? |
| Action tracker | Actions, owners, dates, priority, temporary controls and close-out evidence. | Are high-risk actions verified, not merely marked complete? |
| Training and briefing records | Who was briefed, on what, when and how understanding was checked. | Can workers explain the controls in practice? |
| Inspection and monitoring records | Planned checks, defects, findings, trends and corrective action. | Are checks sampling critical controls? |
| Incident and near-miss learning | Events, weak signals, investigations and improvement actions. | Are repeated signals driving system change? |
| Management review | Trend, assurance confidence, resources and decisions. | Are leaders seeing the right risk picture? |
| Task observation | Actual posture, reach, force, pace and recovery. | Does the assessment match real work? |
| MSD/ULD assessment | ART or suitable assessment where risk is significant. | Are risk factors scored and prioritised? |
| Adjustment record | Modified duties, restrictions and review dates. | Is medical detail minimised and confidential? |
How should rotator cuff controls be assured?
Assurance should check whether high-risk tasks have been redesigned, symptoms are reported early and controls are actually reducing shoulder load.
Assurance should include task observation and worker feedback. A spreadsheet saying task rotation exists is weak if each rotated task still loads the same shoulder in the same way.
Where multiple workers report symptoms, the issue should be treated as a work-design problem requiring management review.
| Assurance check | What good looks like | Escalate if |
|---|---|---|
| Task design | Work height, reach and force are controlled. | People work overhead or at full reach for long periods. |
| Exposure duration | Continuous shoulder loading is limited. | Same task dominates long shifts. |
| Tool selection | Tools are suitable, balanced and maintained. | Workers adapt around heavy or awkward tools. |
| Worker feedback | Symptoms and discomfort are reported early. | People hide pain or fear consequences. |
| Modified duties | Restrictions are practical and reviewed. | Worker returns to aggravating task too soon. |
| Trend review | Repeat symptoms trigger task review. | Cases treated as isolated personal issues. |
Which Great Britain and Northern Ireland duties apply?
Great Britain uses the Management of Health and Safety at Work Regulations 1999 and HSE ULD guidance; Northern Ireland uses the separate Management of Health and Safety at Work Regulations (Northern Ireland) 2000 and HSENI ULD guidance. Both require assessment and control of shoulder-loading work; GB and NI disability-adjustment routes differ when applicable.
Select the legal route for where the work takes place. Regulator guidance explains practice but does not replace legislation or competent advice.
| Issue | Primary route | Decision and evidence |
|---|---|---|
| Great Britain: shoulder-loading work | GB Management Regulations 1999; HSE ULD guidance | Assess reach, force, repetition, duration and recovery; redesign task and respond to symptoms. |
| Northern Ireland: shoulder-loading work | NI Management Regulations 2000; HSENI ULD guidance | Use NI legal and regulator route; above-shoulder work and static hold need attention. |
| Employment adjustments and clinical boundary | GB employment rights; NI employment rights; HSE upper-limb disorders | Use the correct adjustment route when applicable and refer diagnosis or urgent symptoms to health professionals. |
How should the work be managed and checked?
Use an accountable plan, practical controls, worker input and checks that show whether the controls work in real tasks.
HSE’s Plan, Do, Check, Act approach connects the risk decision to implementation, monitoring and improvement. For this topic, the duty holder should name a control owner, define the evidence that the control is effective, and change the work if that evidence fails. A management-system label or certificate is not proof that an individual exposure or task is safe. HSE managing health and safety
| Official guidance | Practical decision | Boundary |
|---|---|---|
| HSE Plan, Do, Check, Act | Assign the risk owner, implement the chosen control and review field evidence after change or failure. | This guidance does not replace the applicable GB or NI law, task assessment or named specialist decision. |
What training and competence are needed?
Match practice and assessment to the person’s decision: workers recognise concerns; managers act on controls; specialists advise within their discipline; leaders verify outcomes.
Use observed scenarios, identify the assessor and record what was demonstrated. Reassess after a changed task, failure or new legal or technical information; do not invent a universal certificate expiry.
On a narrow screen, scroll this table sideways to see every source, decision and evidence column.
Ask the worker to show an early symptom report and safe stop route; ask the supervisor to identify high reach, force and recovery limits on the actual task; ask the designer or manager to demonstrate a redesigned access method and its effectiveness check. A competent health adviser deals with clinical boundaries, not the line manager. Record observed practice and the changed task, then reassess after a new product, work height or persistent symptom pattern.
| Role | Practice and assessment | Assessor | Demonstrated evidence and record | Reassessment trigger |
|---|---|---|---|---|
| Worker | Describe painful tasks and early symptoms, use the reporting route and avoid unsafe self-diagnosis. | Supervisor or trained task assessor | Worker shows how to report symptoms and identify high-reaching or forceful steps without diagnosing themself. Record the assessor, observed task, report route and feedback; keep health details private. | Reassess after a new task, symptom report or changed work arrangement. |
| Supervisor | Observe height, reach, force and duration; act promptly and check modified duties. | Ergonomic assessor or competent safety adviser | Supervisor observes arm height, force, repetition, duration and recovery, then chooses an immediate task change. Record the assessor, task observation, chosen control, worker input and follow-up date. | Reassess if symptoms persist, the task changes or the control is not used. |
| Ergonomic assessor | Demonstrate task measurement, redesign options and post-change effectiveness. | Competent ergonomics lead | Assessor measures the task, compares source controls and verifies reduced shoulder loading in real work. Retain the assessor, before/after observations, worker feedback and effectiveness judgement. | Reassess after equipment or process change or a recurrence cluster. |
| Occupational health or clinician | Assess personal symptoms and work capability within clinical competence. | Clinical service lead | Clinician explains the boundary between workplace exposure review and individual diagnosis, red flags and capability advice. Record professional competence and work-capability advice through the confidential clinical route; share only necessary restrictions. | Reassess on changing symptoms, new clinical advice or failed modified duties. |
| Leader and auditor | Resource equipment and sample whether high-risk shoulder tasks were redesigned. | Senior leader or audit lead | Leader samples whether overhead tasks were redesigned and verifies that reports led to action. Record assessor, sampled task, decisions, owner and field effectiveness evidence. | Reassess after repeat reports, overdue redesign or ineffective controls. |
How could Riverside Leisure Ltd manage this in practice?

Riverside would manage shoulder risk in maintenance, cleaning, gym setup, sports hall work, lifeguard tasks and office/DSE roles through task redesign and early reporting.
A leisure business may have painting, cleaning, pool plant maintenance, moving equipment, setting up classes and DSE work. Riverside would treat shoulder discomfort as work-design data and act early.
| Management element | How the business would manage it | Evidence to review |
|---|---|---|
| Identify | List overhead, repetitive and forceful shoulder tasks. | MSD risk inventory. |
| Assess | Observe posture, force, repetition and recovery. | Task assessment. |
| Control | Change height, tools, staffing, rotation and access. | Control plan. |
| Support | Use private work-impact conversations and OH where needed. | Adjustment record. |
| Review | Trend symptoms and verify redesign. | MSD dashboard. |
What do the acronyms and key terms mean?
Use these terms to explain a work decision, not as proof that a control is effective.
| Term | Expansion | Meaning for this topic |
|---|---|---|
| Rotator cuff | Four-muscle tendon group around the shoulder | A clinician diagnoses the cause of pain. |
| RCRSP | Rotator cuff-related shoulder pain | Broad clinical term covering different shoulder conditions. |
| ULD | Upper limb disorder | Includes shoulder, arm, wrist, hand and neck problems. |
| OH | Occupational health | Professional advice on health and work impact. |
| Work modification | Temporary or lasting change in load or task | Needs owner and effectiveness review. |
| ERICPD | Eliminate, Reduce, Isolate, Control, Personal Protective Equipment, Discipline | Compare source removal and substitution with engineered separation before work rules or PPE; Discipline means checking that stronger controls keep working. |
Unlock another resource
You have used this month’s two free downloads. Publish a post in your own words to unlock one more resource, or choose SHARE Individual for 10 downloads per month.
You decide whether to share. If you do, use the relevant platform disclosure tools and do not make claims you do not genuinely hold.